Related Experiment Video
Updated: Feb 16, 2026


Assays for the Specific Growth Rate and Cell-binding Ability of Rotavirus
Published on: January 28, 2019
Distributional cost-effectiveness analysis in low- and middle-income countries: illustrative example of rotavirus
Bryony R Dawkins1, Andrew J Mirelman2, Miqdad Asaria2
1Academic Unit of Health Economics, Leeds Institute of Health Sciences, Worsley Building, Clarendon Way, Leeds LS2 9NL, UK.

Abstract:
Reducing health inequality is a major policy concern for low- and middle-income countries (LMICs) on the path to universal health coverage. However, health inequality impacts are rarely quantified in cost-effectiveness analyses of health programmes. Distributional cost-effectiveness analysis (DCEA) is a method developed to analyse the expected social distributions of costs and health benefits, and the potential trade-offs that may exist between maximising total health and reducing health inequality. This is the first paper to show how DCEA can be applied in LMICs. Using the introduction of rotavirus vaccination in Ethiopia as an illustrative example, we analyse a hypothetical re-designed vaccination programme, which invests additional resources into vaccine delivery in rural areas, and compare this with the standard programme currently implemented in Ethiopia. We show that the re-designed programme has an incremental cost-effectiveness ratio of US$69 per health-adjusted life year (HALY) compared with the standard programme. This is potentially cost-ineffective when compared with current estimates of health opportunity cost in Ethiopia. However, rural populations are typically less wealthy than urban populations and experience poorer lifetime health. Prioritising such populations can thus be seen as being equitable. We analyse the trade-off between cost-effectiveness and equity using the Atkinson inequality aversion parameter, ε, representing the decision maker's strength of concern for reducing health inequality. We find that the more equitable programme would be considered worthwhile by a decision maker whose inequality concern is greater than ε = 5.66, which at current levels of health inequality in Ethiopia implies that health gains are weighted at least 3.86 times more highly in the poorest compared with the richest wealth quintile group. We explore the sensitivity of this conclusion to a range of assumptions and cost-per-HALY threshold values, to illustrate how DCEA can inform the thinking of decision makers and stakeholders about health equity trade-offs.


Related Concept Videos
 01:51
Vaccinations
 01:30
Cancer Vaccines
Cancer vaccines come in two categories: preventive (prophylactic) and treatment (active). Preventive vaccines, such as the Human Papillomavirus (HPV) vaccine, protect against viruses that cause certain...
 02:19
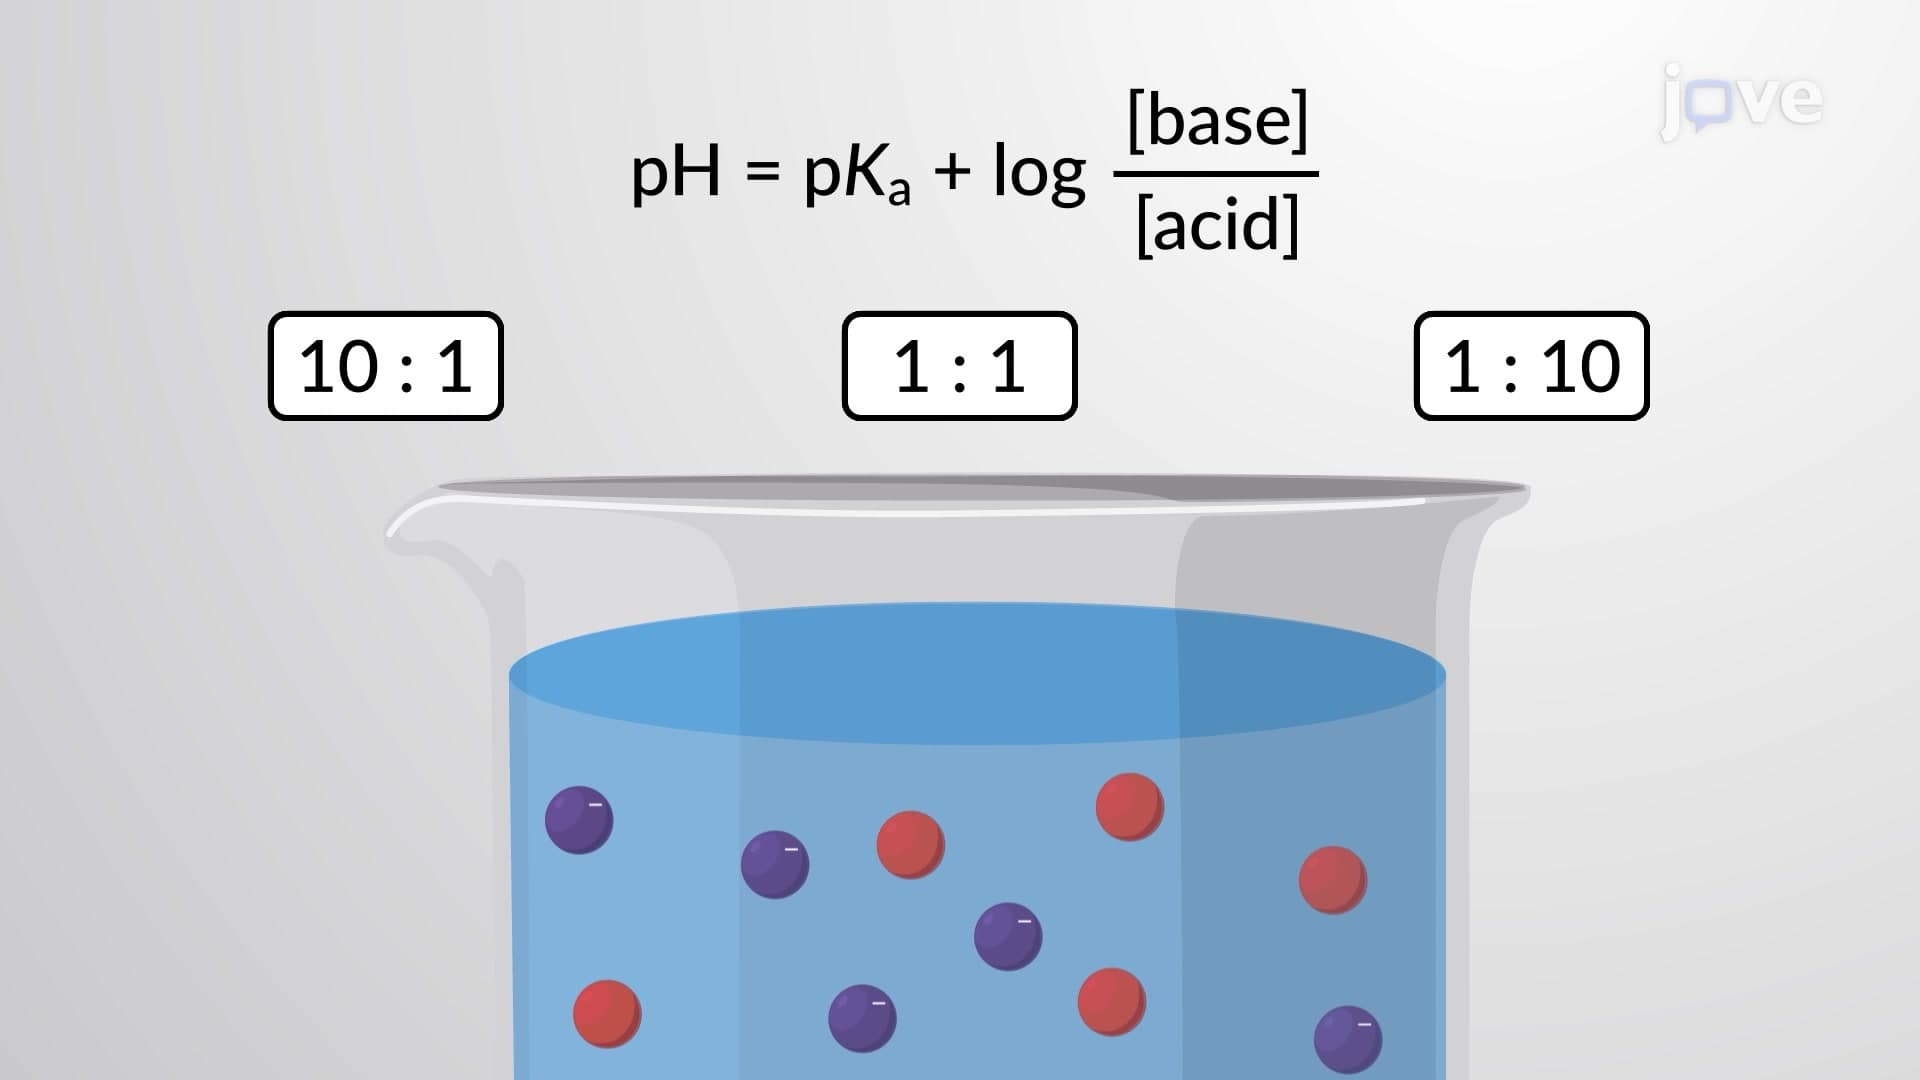
Buffer Effectiveness
The buffer capacity is the amount of acid or base that can be added to a given volume...
 01:25
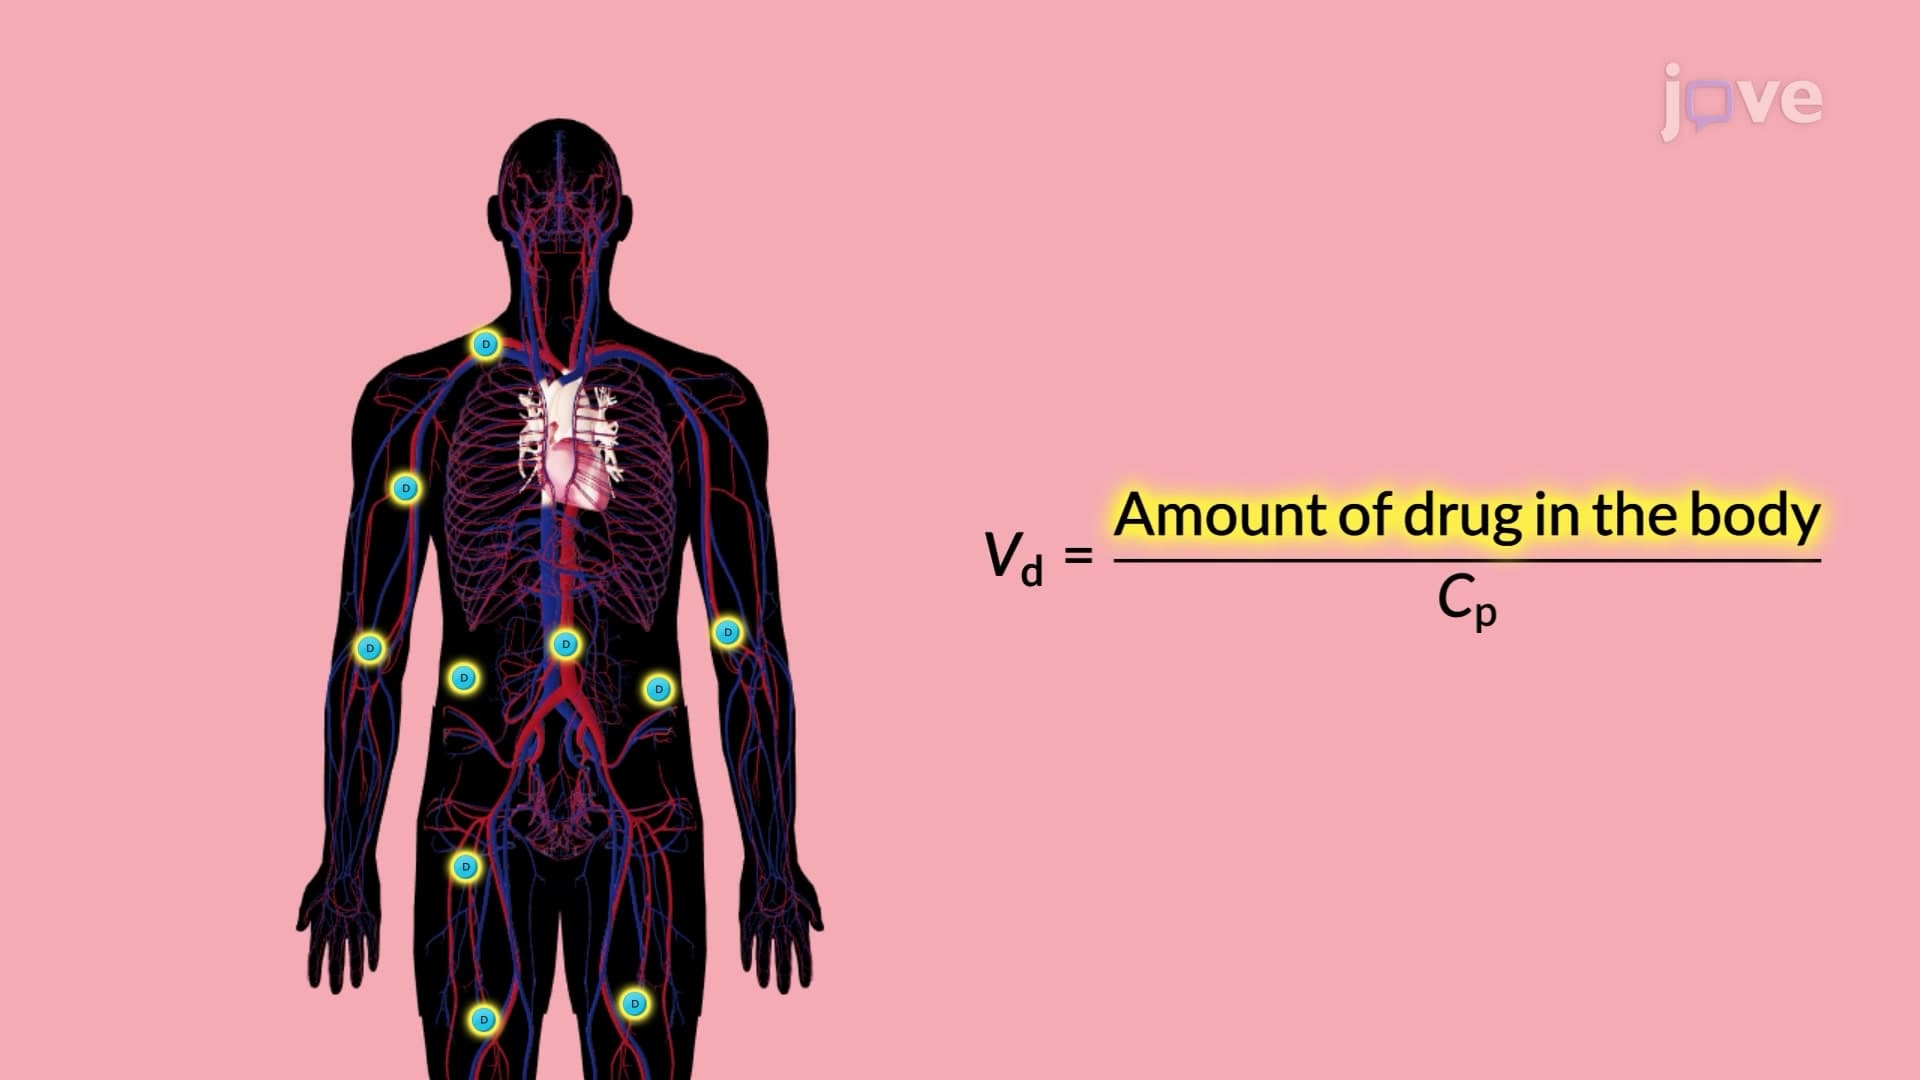
Drug Distribution: Volume of Distribution
 01:19
F Distribution
 03:26
Framing Effects