Related Experiment Video
Updated: Feb 15, 2026
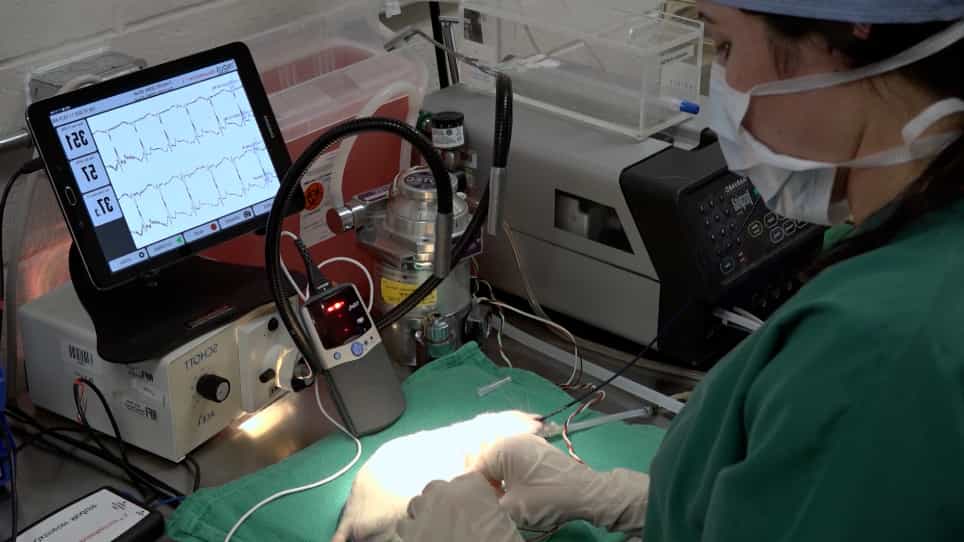

An Image Guided Transapical Mitral Valve Leaflet Puncture Model of Controlled Volume Overload from Mitral Regurgitation in the Rat
Published on: May 19, 2020
Exercise Hemodynamic and Functional Capacity After Mitral Valve Replacement in Patients With Ischemic Mitral
Carlo Fino1, Attilio Iacovoni1, Philippe Pibarot2
1>From the Cardiovascular Department, Ospedale Papa Giovanni XXIII, Bergamo, Italy (C.F., A.I., P.F., M.M., L.G., P.F., D.C., M.S.); Hypertrofic Cardiomyopathy Centre, Policlinico di Monza, Monza, Italy (P.F.); Québec Heart & Lung Institute, Department of Medicine, Laval University, Quebec City, QC, Canada (P.P.); Department of Cardiothoracic Surgery, Royal Brompton and Harefield Hospital, London, United Kingdom (J.R.P.); Bristol Royal Infirmary, University of Bristol, United Kingdom (M.C.); Surgical Skills Centre, Manchester Science Park, United Kingdom (C.A.); Division of Cardiovascular Diseases, Mediterranean Institute for Transplantation and Advanced Specialized Therapies (ISMETT), Palermo, Italy (D.B.); and CHU Limoges, Hôpital Dupuytren, Service Cardiologie, France (J.M.).

Background:
In patients with ischemic mitral regurgitation requiring mitral valve replacement (MVR), the choice of the prosthesis type is crucial. The exercise hemodynamic and functional capacity performance in patients with contemporary prostheses have never been investigated. To compare exercise hemodynamic and functional capacity between biological (MVRb) and mechanical (MVRm) prostheses.
Methods And Results:
We analyzed 86 consecutive patients with ischemic mitral regurgitation who underwent MVRb (n=41) or MVRm (n=45) and coronary artery bypass grafting. All patients underwent preoperative resting echocardiography and 6-minute walking test. At follow-up, exercise stress echocardiography was performed, and the 6-minute walking test was repeated. Resting and exercise indexed effective orifice areas of MVRm were larger when compared with MVRb (resting: 1.30±0.2 versus 1.19±0.3 cm2/m2; P=0.03; exercise: 1.57±0.2 versus 1.18±0.3 cm2/m2; P=0.0001). The MVRm had lower exercise systolic pulmonary arterial pressure at follow-up compared with MVRb (41±5 versus 59±7 mm Hg; P=0.0001). Six-minute walking test distance was improved in the MVRm (pre-operative: 242±43, post-operative: 290±50 m; P=0.001), whereas it remained similar in the MVRb (pre-operative: 250±40, post-operative: 220±44 m; P=0.13). In multivariable analysis, type of prosthesis, exercise indexed effective orifice area, and systolic pulmonary arterial pressure were joint predictors of change in 6-minute walking test (ie, difference between baseline and follow-up).
Conclusions:
In patients with ischemic mitral regurgitation, bioprostheses are associated with worse hemodynamic performance and reduced functional capacity, when compared with MVRm. Randomized studies with longer follow-up including quality of life and survival data are required to confirm these results.


Related Concept Videos
 01:20
Mitral Regurgitation I: Introduction
 01:27
Mitral Valve Prolapse I: Introduction
 01:25
Mitral Regurgitation III: Medical Management
 01:28
Mitral Regurgitation IV: Nursing Management
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests