Related Experiment Video
Updated: Feb 15, 2026


High Throughput Sequential ELISA for Validation of Biomarkers of Acute Graft-Versus-Host Disease
Published on: October 31, 2012
Validation of the AAST EGS acute cholecystitis grade and comparison with the Tokyo guidelines
Matthew Hernandez1, Brittany Murphy1, Johnathan M Aho1
1Division of Trauma, Critical Care and General Surgery, Mayo Clinic, Rochester, MN, USA.

Background:
Acute cholecystitis presents with heterogeneous severity. The Tokyo Guidelines 2013 is a validated method to assess cholecystitis severity, but the variables are multifactorial. The American Association for the Surgery of Trauma (AAST) developed an anatomically based severity grading system for surgical diseases, including cholecystitis. Because the Tokyo Guidelines represent the gold standard to estimate acute cholecystitis severity, we wished to validate the AAST emergency general surgery scoring system and compare the performance of both systems for several patient outcomes.
Methods:
Adults (≥18 years) with acute cholecystitis during 2013-2016 were identified. Baseline demographic characteristics, comorbidity severity as defined by Charlson Comorbidity Index score, procedure types, and AAST and Tokyo Guidelines 2013 grades were abstracted. Outcomes included duration of stay, 30-day mortality, and complications. Comparison of the Tokyo Guidelines and AAST grading system was performed using receiver operating characteristic (AUROC) curve C statistics.
Results:
There were 443 patients, with a mean (±standard deviation) age of 64.8 (±18) years, 59% male. The median (interquartile ratio) Charlson Comorbidity score was 3 (0-6). Management included laparoscopic (n = 307, 69.3%), open (n = 26, 6%), laparoscopy converted to laparotomy (n = 53, 12%), and cholecystostomy (n = 57, 12.7%). Comparison of AAST with Tokyo Guidelines AUROC C statistics indicated (P < .05) mortality (0.86 vs 0.73), complication (0.76 vs 0.63), and cholecystostomy tube utilization (0.80 vs 0.68).
Conclusion:
Emergency general surgery grading systems improve disease severity assessment, may improve documentation, and guide management. Discrimination of disease severity using the AAST grading system outperforms the Tokyo Guidelines for key clinical outcomes. The AAST grading system requires prospective validation and further comparison.


Related Concept Videos
 01:29
Reliability and Validity
 01:19
Graded Potential
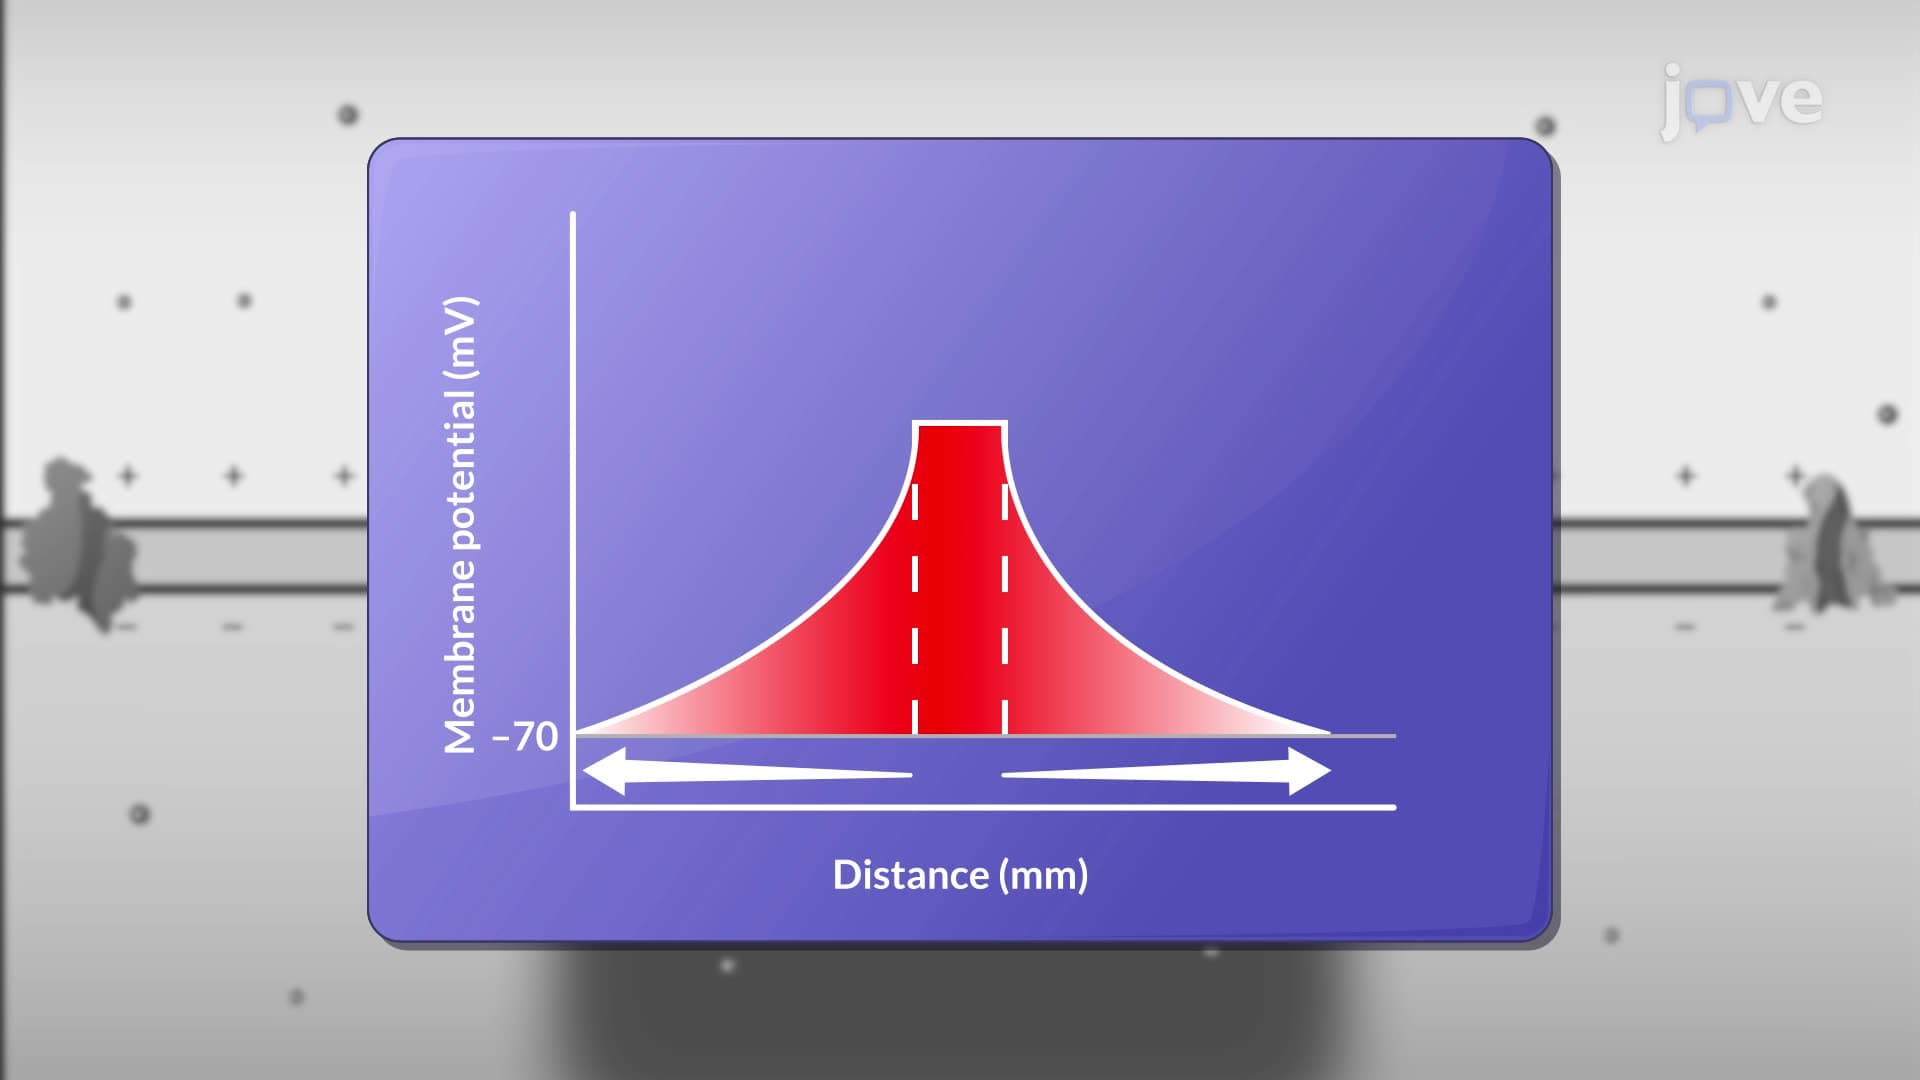
Graded potentials fall into two categories: depolarizing and hyperpolarizing. Depolarizing graded potentials typically occur when sodium (Na+) or...
 01:23
Guidelines for Sketching a Curve
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...
 01:30
Guidelines for Nursing Documentation I
Factual:
The following points emphasize the significance of upholding accurate and unbiased documentation in healthcare.
 02:57
The Sense of Self: Reflected Self-Appraisal and Social Comparison