

The "hidden" concealed left-sided accessory pathway: An uncommon cause of SVT in young people
Robert H Pass1, Leonardo Liberman2, Eric S Silver2
1The Children's Hospital at Montefiore, Albert Einstein College of Medicine, Yeshiva University, Bronx, NY, USA.

Background:
Concealed left-sided accessory pathways (CLAP) are a cause of supraventricular tachycardia (SVT) in the young. Most are mapped with right ventricular (RV) apical/outflow pacing. Rarely, alternative means of mapping are required. We review our experience from three pediatric electrophysiology (EP) centers with a rare form of "hidden" CLAP.
Methods:
All patients <21 years undergoing EP study from 2008 to 2014 with a "hidden" CLAP (defined as an accessory pathway [AP] for which RV pacing at cycle lengths [CL] stable for mapping did not demonstrate eccentric retrograde conduction) were included.
Exclusion Criteria:
preexcitation. Demographic, procedural, and follow-up data were collected.
Results:
A total of 23 patients met the criteria (median age, 14.3 years [range 7-21], weight, 51 kg [31-99]). 21 (96%) had SVT and one AFIB (4%). APs were adenosine sensitive in 7/20 patients (35%) and VA conduction was decremental in six (26%). CLAP conduction was demonstrable with orthodromic reentrant tachycardia in all patients, with RV extrastimulus testing in seven (30%) and with rapid RV pacing (
Conclusions:
Some CLAPs are only demonstrable with LV pacing, entrained ORT, or rapid RV pacing. LV pacing facilitated preferential AP conduction, allowing for mapping while maintaining stable hemodynamics.
More Related Videos


Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:25
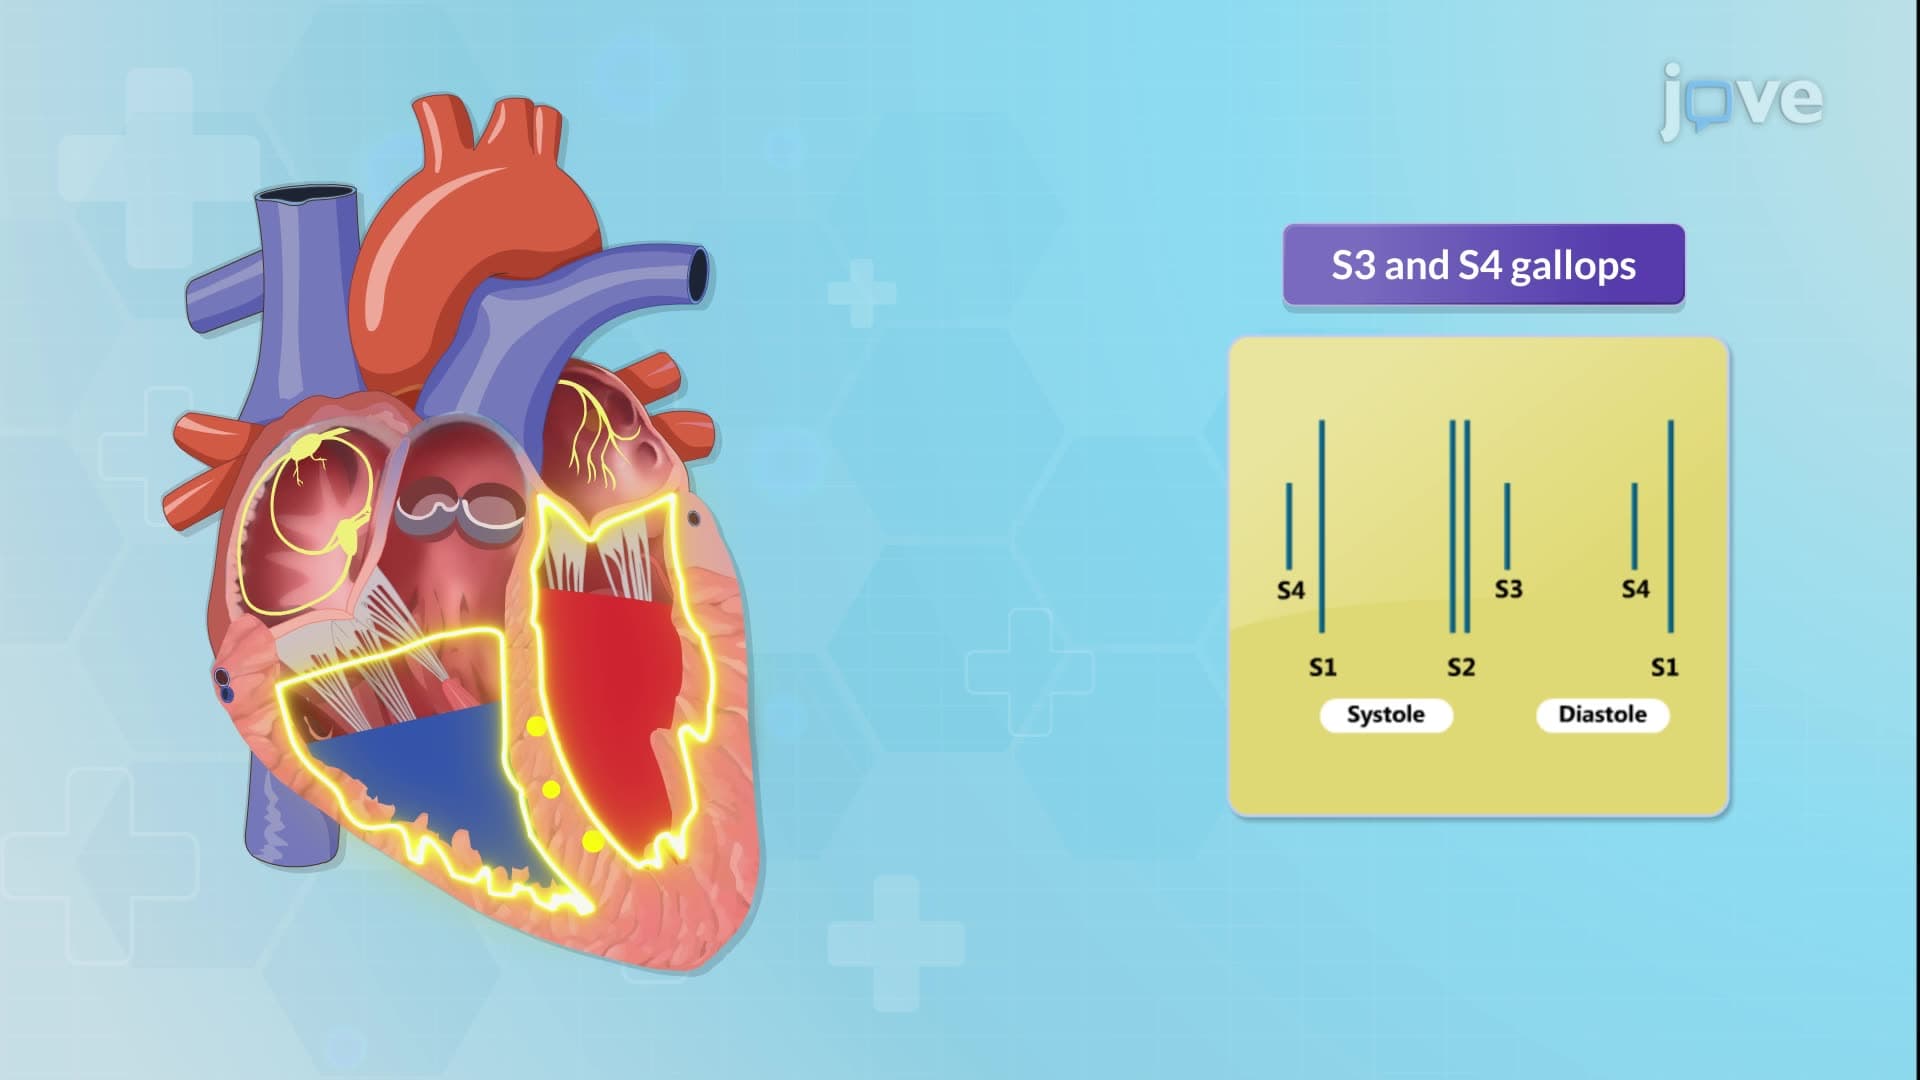
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:22
Mitral Stenosis I: Introduction
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias