Related Experiment Video
Updated: Feb 15, 2026

A Data Integration Workflow to Identify Drug Combinations Targeting Synthetic Lethal Interactions
Published on: May 27, 2021
Abatacept used in combination with non-methotrexate disease-modifying antirheumatic drugs: a descriptive analysis of
Rieke Alten1, Harald Burkhardt2, Eugen Feist3
1Department of Internal Medicine, Rheumatology, Clinical Immunology and Osteology, Schlosspark-Klinik University Medicine Berlin, Heubnerweg 2, 14059, Berlin, Germany. rieke.alten@schlosspark-klinik.de.

Background:
Methotrexate (MTX) remains the anchor drug in rheumatoid arthritis (RA) treatment, but is poorly tolerated or contraindicated in some patients. There is a wealth of data supporting the use of abatacept in combination with MTX, but data on alternative conventional synthetic disease-modifying antirheumatic drug (csDMARD) combinations with abatacept are scarce.
Methods:
In this post-hoc exploratory analysis, efficacy and safety data were extracted from abatacept RA studies in which combination with csDMARDs other than MTX was permitted: three interventional trials (ATTAIN, ASSURE, and ARRIVE) and one real-world study (ACTION). Patients with moderate-to-severe RA received abatacept in combination with MTX, hydroxychloroquine, sulfasalazine, azathioprine, or leflunomide for 6 months to 2 years according to the study design. Change from baseline in physical function (Health Assessment Questionnaire-Disability Index (HAQ-DI); all studies) and 28-joint Disease Activity Score (C-reactive protein) (DAS28 (CRP); ATTAIN, ARRIVE, and ACTION), American College of Rheumatology response rates (ATTAIN), and safety were assessed for individual and pooled csDMARD combinations for each trial. A meta-analysis was also performed on pooled data for HAQ-DI and DAS28 (CRP) across interventional trials.
Results:
Across all four studies, 731 patients received abatacept plus one non-MTX csDMARD (hydroxychloroquine n = 152; sulfasalazine n = 123; azathioprine n = 59; and leflunomide n = 397) and 2382 patients received abatacept plus MTX. Mean changes from baseline in HAQ-DI scores for abatacept plus MTX (all csDMARDs pooled) vs abatacept plus a non-MTX csDMARD were -0.54 vs -0.44 (ATTAIN), -0.43 vs -0.43 (ASSURE), and -0.39 vs -0.36 (ARRIVE). Mean changes from baseline in DAS28 (CRP) and ACR response rates were also similar with abatacept plus MTX or non-MTX csDMARDs. Data for individual non-MTX csDMARDs (pooled across studies) and real-world data were consistent with these findings. Rates of treatment-related adverse events and serious adverse events, respectively, for abatacept plus one non-MTX csDMARD vs abatacept plus MTX were 35.7% vs 41.7% and 2.4% vs 2.3% (ATTAIN), 58.0% vs 55.9% and 4.2% vs 1.7% (ASSURE), and 38.1% vs 44.3% and 0.6% vs 2.9% (ARRIVE).
Conclusions:
Abatacept in combination with non-MTX csDMARDs is clinically effective and well tolerated in patients with moderate-to-severe RA, providing similar benefits to those seen with abatacept plus MTX.
Trial Registration:
ClinicalTrials.gov NCT00048581 . Registered 2 November 2002. ClinicalTrials.gov NCT00048932 . Registered 11 November 2002. ClinicalTrials.gov NCT00124982 . Registered 30 June 2005. ClinicalTrials.gov NCT02109666 . Registered 8 April 2014.

Related Concept Videos
 01:12
Statistical Software for Data Analysis and Clinical Trials
 01:09
Design Example: Setting a Curve Using Design Data
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:27
Combined Effects of Drugs: Synergism
Such synergistic combinations...
 01:30
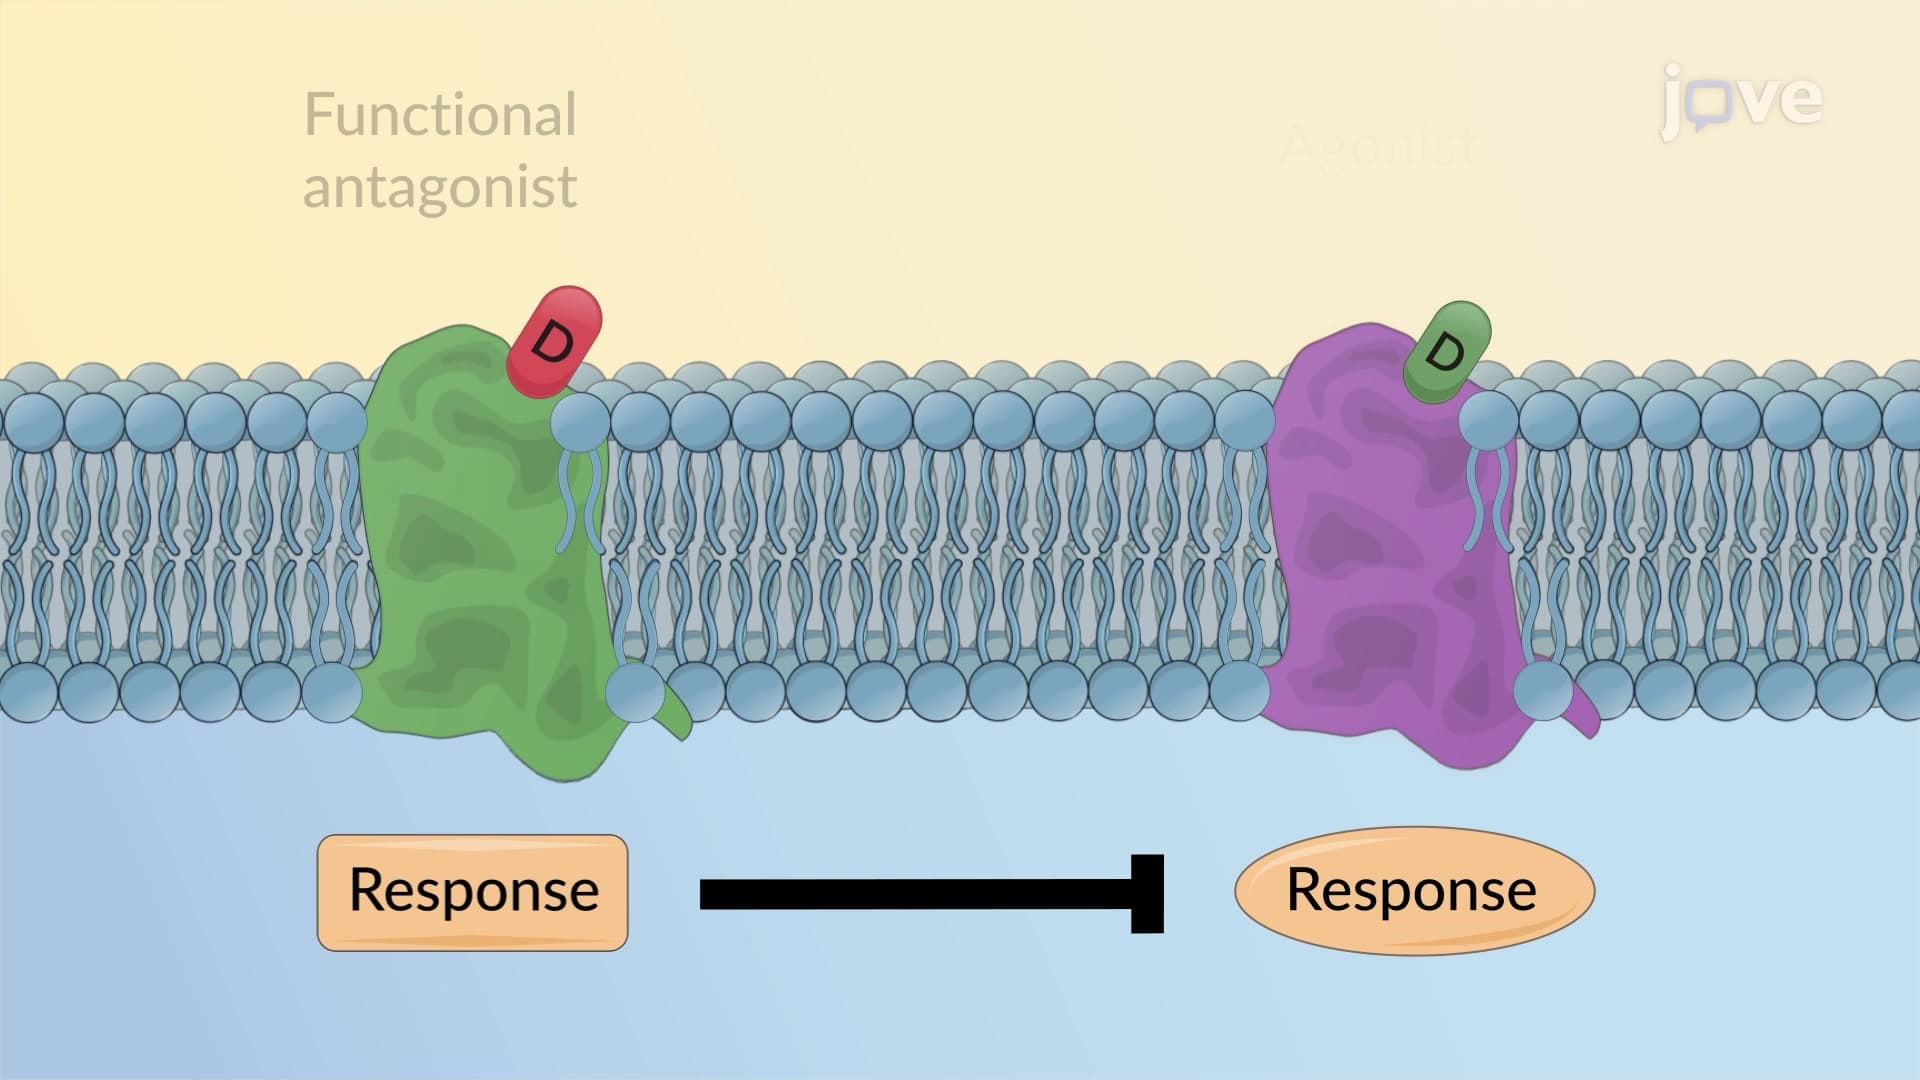
Combined Effects of Drugs: Antagonism
The most common type is receptor antagonism, where one drug acts as an antagonist to block the effects of another drug by...
 01:12
Analysis of Population Pharmacokinetic Data