Related Experiment Video
Updated: Feb 15, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Comparisons of Rigid Proctoscopy, Flexible Colonoscopy, and Digital Rectal Examination for Determining the
Akira Tanaka1, Sotaro Sadahiro, Toshiyuki Suzuki
1Department of Surgery, Tokai University School of Medicine, Isehara, Kanagawa, Japan.

Background:
Rigid proctoscopy is considered essential for rectal tumor localization, although the current gold standard for detection of colorectal cancers is colonoscopy. The European Society for Medical Oncology Guidelines indicate that rigid and flexible endoscopies afford essentially identical results, although little evidence is yet available to support this.
Objective:
The purpose of this study was to determine the accuracy of colonoscopy in identifying the location of rectal cancer and to compare the results with those of rigid proctoscopy and digital rectal examination.
Design:
This was a retrospective analysis of a prospective database.
Settings:
The study was conducted at a single tertiary colorectal surgery referral center.
Patients:
A total of 173 patients scheduled for curative surgery for histologically verified rectal adenocarcinoma between December 2009 and February 2015 were entered into the study, after having given informed consent.
Main Outcome Measures:
The main study measure was the mean difference and limits of agreement in assessment of the height of the distal edge of rectal cancer from the anal verge, using the Bland and Altman method.
Results:
The mean difference between rigid proctoscopy and flexible colonoscopy was -0.2 cm (95% CI, -2.0 to 1.6 cm). The mean difference between rigid proctoscopy and digital rectal examination was 0.3 cm (95% CI, 1.9 to 2.4 cm). Intermethod variability larger than the 95% CI between rigid and flexible endoscopes was correlated to the tumor height (OR, 4.27 (95% CI, 1.84-3.10); p = 0.021).
Limitations:
This study was conducted in a single center.
Conclusions:
The limits of agreement (-2.0 and 1.6 cm) in identifying the height of rectal cancers from the anal verge are sufficiently small to support the view that flexible colonoscopy provides similar tumor locations to those measured by rigid proctoscopy, although the discrepancy occasionally exceeded 2 cm for tumors >5 cm above the anal verge. See Video Abstract at http://links.lww.com/DCR/A405.
More Related Videos
 15:49
Flexible Colonoscopy in Mice to Evaluate the Severity of Colitis and Colorectal Tumors Using a Validated Endoscopic Scoring System
Published on: October 16, 2013
 05:32
Povidone Iodine Rectal Preparation at Time of Prostate Needle Biopsy is a Simple and Reproducible Means to Reduce Risk of Procedural Infection
Published on: September 21, 2015
Related Concept Videos
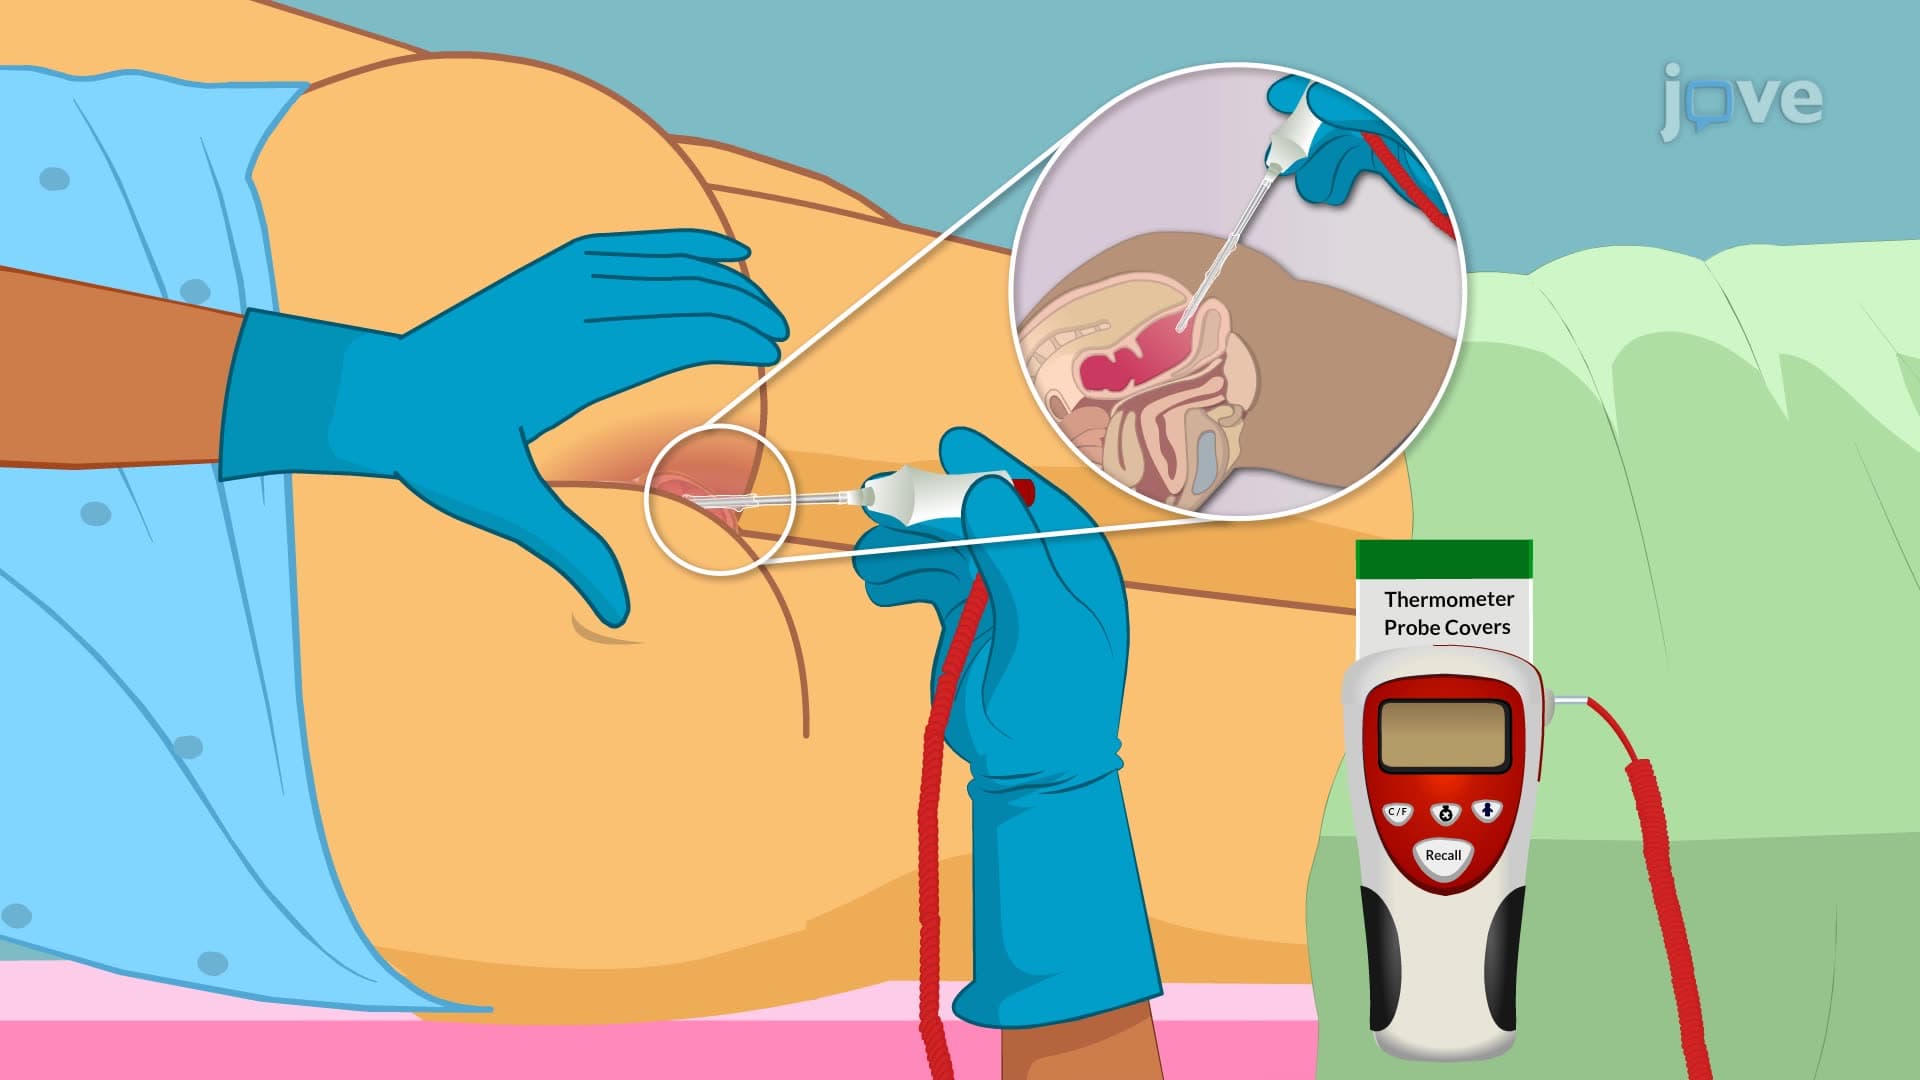 01:27
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:25
Endoscopic Procedures II: Colonoscopy
 02:57
The Sense of Self: Reflected Self-Appraisal and Social Comparison
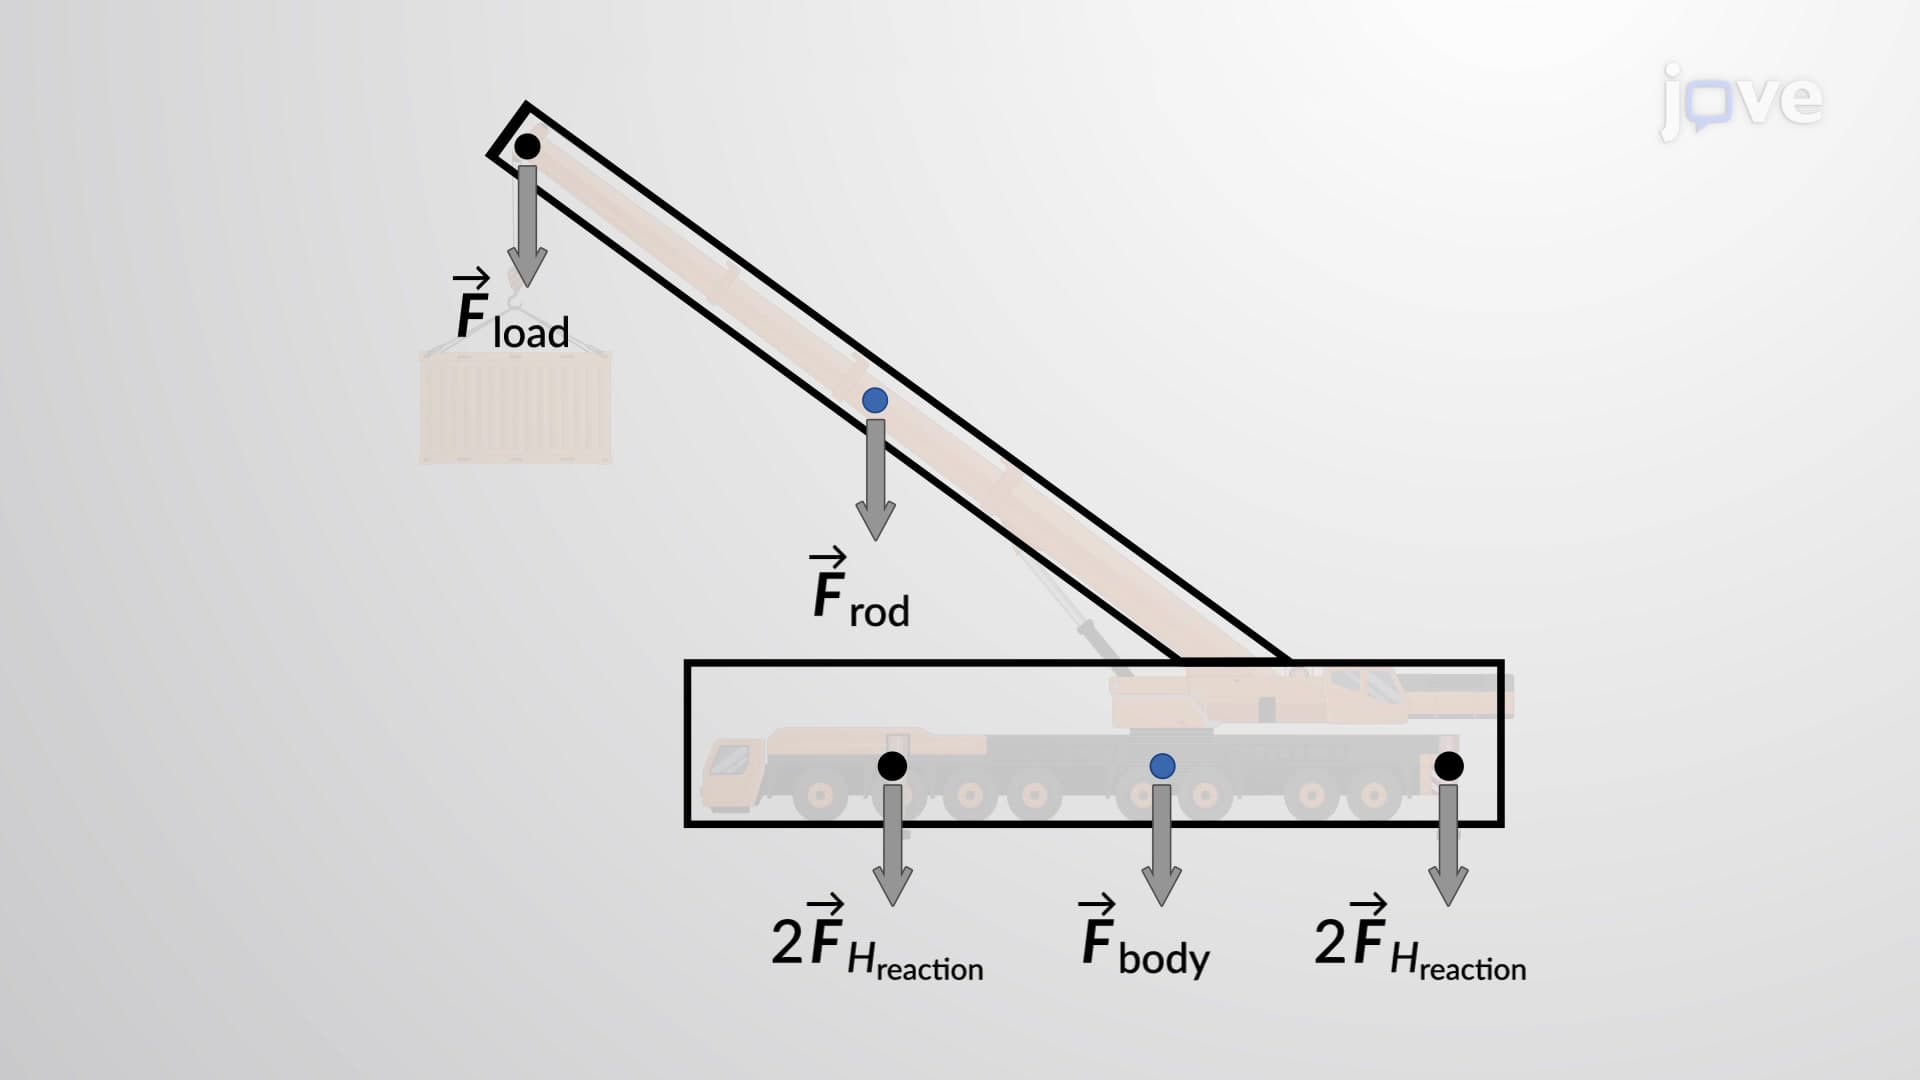 00:49
Rigid Body Equilibrium Problems - I
 01:21
Rigid Body Equilibrium Problems - II
Consider two children sitting on a seesaw, which has negligible mass. The first child has a mass (m1) of 26 kg and sits at point A, which is 1.6 meters (r1) from the pivot point B; the second child has a mass (m2) of 32 kg and sits at point C. How far from the pivot point B should the second child sit (r2) to balance the seesaw?
 01:11
Angular Momentum: Rigid Body
This calculation can get complicated when tiny particles within the rigid body are not rotating in the same plane but have...