Related Experiment Video
Updated: Feb 15, 2026
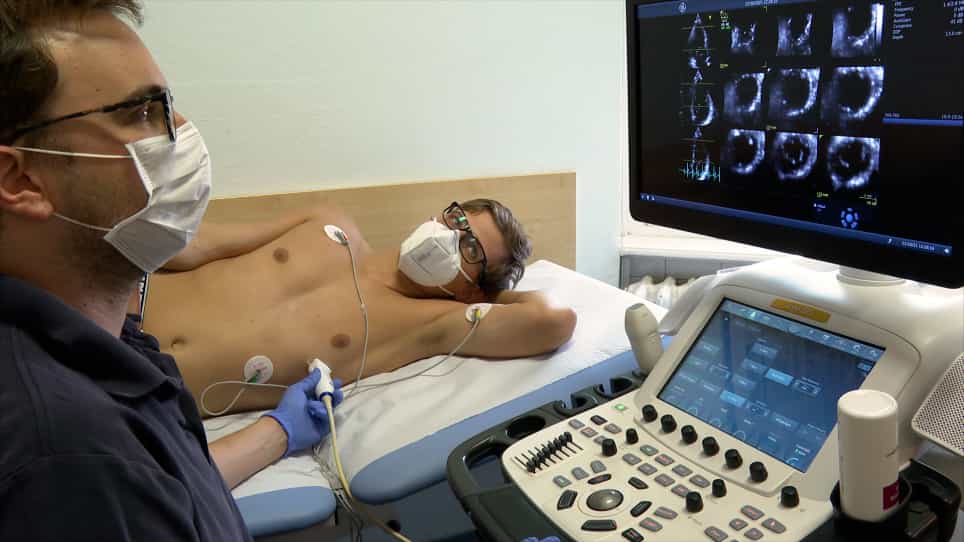

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Impaired Recovery of Left Ventricular Function in Patients With Cardiomyopathy and Left Bundle Branch Block
Edward Sze1, Zainab Samad1, Allison Dunning2
1Division of Cardiology, Department of Medicine, Duke University, Durham, North Carolina.

Insights
Patients with left bundle branch block (LBBB) show less left ventricular ejection fraction (LVEF) improvement with guideline-directed medical therapy (GDMT) compared to other QRS morphologies. Early cardiac resynchronization therapy (CRT) may benefit some LBBB patients.
Area of Science:
- Cardiology
- Electrophysiology
- Heart Failure Management
Background:
- Patients with left bundle branch block (LBBB) often improve left ventricular ejection fraction (LVEF) with cardiac resynchronization therapy (CRT).
- Guideline-directed medical therapy (GDMT) is the first-line treatment for reduced LVEF in LBBB patients, but data on GDMT response is limited.
- Understanding LVEF response to GDMT in LBBB is crucial for optimizing heart failure treatment.
Purpose of the Study:
- To assess LVEF improvement rates in patients with cardiomyopathy and LBBB compared to other QRS morphologies.
- To evaluate the impact of GDMT on LVEF changes in patients with LBBB.
- To inform treatment guidelines for heart failure patients with LBBB.
Main Methods:
- Retrospective analysis of 659 patients with LVEF ≤35% from the Duke Echocardiography Laboratory Database.
- Patients were categorized by QRS morphology: LBBB, wide QRS (≥120 ms, not LBBB), and narrow QRS (<120 ms).
- LVEF changes were analyzed over 3-6 months, adjusting for comorbidities, GDMT, revascularization, and myocardial infarction.
Main Results:
- LBBB patients showed a significantly smaller adjusted mean LVEF increase (2.03%) compared to narrow QRS (8.00%) and wide QRS (5.28%) groups (p < 0.0001).
- No significant difference in LVEF improvement was observed between LBBB patients on GDMT versus those not on GDMT (3.50% vs. 3.44%).
- Patients with LBBB had the highest combined endpoint of heart failure hospitalization or mortality.
Conclusions:
- Left bundle branch block is associated with a lesser degree of LVEF improvement with GDMT compared to other QRS morphologies.
- Current GDMT may be less effective in improving LVEF for LBBB patients.
- Consideration for earlier CRT in select LBBB patients may be warranted, deviating from current guideline recommendations.
Background:
Patients with left bundle branch block (LBBB) often respond to cardiac resynchronization therapy (CRT) with left ventricular ejection fraction (LVEF) improvement. Guideline-directed medical therapy (GDMT), not CRT, is first-line therapy for patients with reduced LVEF with LBBB. However, there are little data on how patients with reduced LVEF and LBBB respond to GDMT.
Objectives:
This study examined patients with cardiomyopathy and sought to assess rates of LVEF improvement for patients with LBBB compared to other QRS morphologies.
Methods:
Using data from the Duke Echocardiography Laboratory Database, the study identified patients with baseline electrocardiography and LVEF ≤35% who had a follow-up LVEF 3 to 6 months later. The study excluded patients with severe valve disease, a cardiac device, left ventricular assist device, or heart transplant. QRS morphology was classified as LBBB, QRS duration <120 ms (narrow QRS duration), or a wide QRS duration ≥120 ms but not LBBB. Analysis of variance testing compared mean change in LVEF among the 3 groups with adjustment for significant comorbidities and GDMT.
Results:
There were 659 patients that met the criteria: 111 LBBB (17%), 59 wide QRS duration ≥120 ms but not LBBB (9%), and 489 narrow QRS duration (74%). Adjusted mean increase in LVEF over 3 to 6 months in the 3 groups was 2.03%, 5.28%, and 8.00%, respectively (p < 0.0001). Results were similar when adjusted for interim revascularization and myocardial infarction. Comparison of mean LVEF improvement between patients with LBBB on GDMT and those not on GDMT showed virtually no difference (3.50% vs. 3.44%). The combined endpoint of heart failure hospitalization or mortality was highest for patients with LBBB.
Conclusions:
LBBB is associated with a smaller degree of LVEF improvement compared with other QRS morphologies, even with GDMT. Some patients with LBBB may benefit from CRT earlier than guidelines currently recommend.
More Related Videos
 12:45
Benefits of Cardiac Resynchronization Therapy in an Asynchronous Heart Failure Model Induced by Left Bundle Branch Ablation and Rapid Pacing
Published on: December 11, 2017
 07:24
Reduction in Left Ventricular Wall Stress and Improvement in Function in Failing Hearts using Algisyl-LVR
Published on: April 8, 2013
Related Concept Videos
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:25
Cardiomyopathy I: Introduction and Classification