Related Experiment Video
Updated: Feb 15, 2026
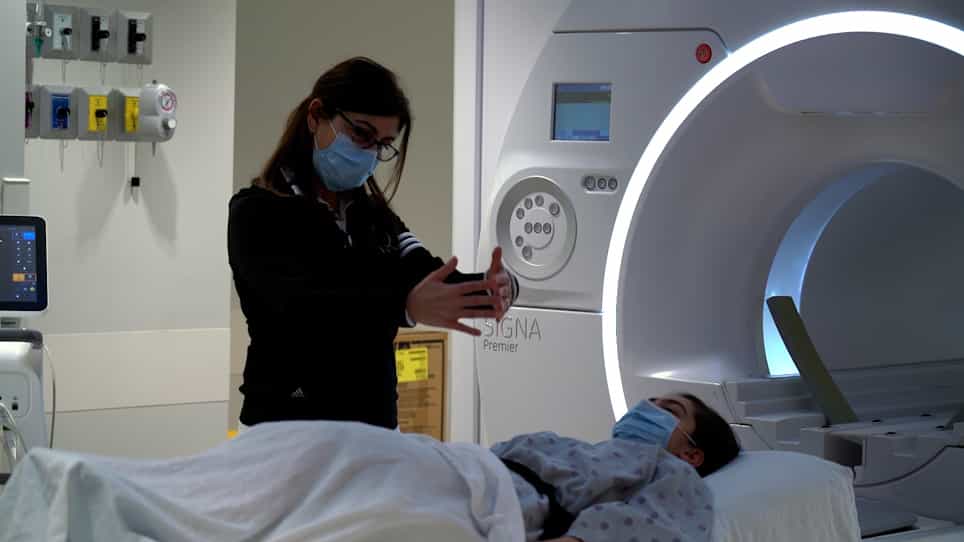

Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Coronary microvascular dysfunction may be related to IGF-1 in acromegalic patients and can be restored by therapy
Sara Tellatin1, Pietro Maffei2, Elena Osto3
1Department of Cardiac, Thoracic and Vascular Sciences, University of Padova, Padova, Italy.

Insights
Asymptomatic acromegaly patients show coronary microvascular dysfunction, linked to elevated insulin-like growth factor 1 (IGF-1). Therapy with somatostatin analogues may restore coronary flow reserve (CFR) in active disease.
Area of Science:
- Endocrinology
- Cardiology
- Medical Diagnostics
Background:
- Acromegaly is associated with increased cardiovascular mortality.
- Data on cardiovascular risk in asymptomatic acromegaly, particularly coronary microvascular abnormalities, are limited.
Purpose of the Study:
- To assess coronary flow reserve (CFR) as a marker of coronary microvascular function in asymptomatic acromegaly patients.
- To investigate the relationship between CFR and biochemical markers like insulin-like growth factor 1 (IGF-1).
Main Methods:
- Transthoracic Doppler echocardiography was used to measure coronary flow velocity in 40 asymptomatic acromegaly patients and 40 controls.
- Coronary flow reserve (CFR) was calculated as the ratio of hyperemic to resting diastolic flow velocity during adenosine infusion.
Main Results:
- Acromegaly patients exhibited significantly lower CFR compared to controls (2.9 vs. 3.7, p<0.0001).
- Abnormal CFR (≤2.5) was observed in 32.5% of patients versus 0% of controls (p<0.0001).
- CFR was inversely correlated with IGF-1 levels (r=-0.5, p<0.004), and IGF-1 independently predicted impaired CFR.
Conclusions:
- Asymptomatic acromegaly patients demonstrate coronary microvascular dysfunction.
- Elevated IGF-1 is independently associated with coronary microvascular impairment in acromegaly.
- Therapy with somatostatin analogues showed potential to restore CFR in patients with active disease.
Background And Aims:
Acromegaly increases the risk of cardiovascular mortality. Data on the cardiovascular risk in asymptomatic acromegaly are limited. In particular, data on coronary microvascular abnormalities are lacking. We assessed coronary flow reserve (CFR) as a marker of coronary microvascular function in asymptomatic acromegaly.
Methods:
We studied 40 acromegalic patients (23 male, age 52 ± 11 years) without clinical evidence of cardiovascular disease, and 40 control subjects matched for age and sex. Coronary flow velocity in the left anterior descending coronary artery was detected by transthoracic Doppler echocardiography, at rest, and during adenosine infusion. CFR was the ratio of hyperaemic to resting diastolic flow velocity.
Results:
CFR was lower in patients than in controls (2.9 ± 0.8 vs. 3.7 ± 0.6, p < 0.0001) and was abnormal (≤2.5) in 13 patients (32.5%) compared with any control subjects (0%) (p < 0.0001). CFR was inversely related to insulin-like growth factor 1 (IGF-1) levels (r = -0.5, p < 0.004). In patients with CFR≤2.5, IGF-1 was higher (756 [381-898] μg/l versus 246 [186-484] μg/l, p < 0.007) whereas growth hormone (GH) levels were similar (6.3 [2.8-13.7] μg/l versus 5 [2.8-8.9] μg/l, p = 0.8). In multivariable linear regression analysis, IGF-1 was independently associated with CFR (p < 0.0001). In multiple logistic regression analysis, IGF-1 independently increased the probability of CFR≤2.5 (p = 0.009). In four patients with active disease (all with CFR<2.5), treatment with somatostatin analogues normalized CFR. However the other four patients with active disease were not responder.
Conclusions:
Acromegalic patients have coronary microvascular dysfunction that may be restored by therapy with somatostatin analogues. IGF-1 independently correlates with the coronary microvascular impairment, suggesting the pivotal role of this hormone in explaining the increased cardiovascular risk in acromegaly.
Related Concept Videos
 01:19
Restorative Care
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 00:59
Gene Therapy
 01:26
Group Therapy
 01:30
Coronary Artery Disease I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology