Related Experiment Video
Updated: Feb 15, 2026

Carotid Artery Infusions for Pharmacokinetic and Pharmacodynamic Analysis of Taxanes in Mice
Published on: October 27, 2014
Amikacin Pharmacokinetic-Pharmacodynamic Analysis in Pediatric Cancer Patients
Ali A Alhadab1, Mariam A Ahmed2, Richard C Brundage1
1Department of Experimental and Clinical Pharmacology, University of Minnesota, Minneapolis, Minnesota, USA.

Abstract:
We performed pharmacokinetic-pharmacodynamic (PK-PD) and simulation analyses to evaluate a standard amikacin dose of 15 mg/kg once daily in children with cancer and to determine an optimal dosing strategy. A population pharmacokinetic model was developed from clinical data collected in 34 pediatric patients and used in a simulation study to predict the population probability of various dosing regimens to achieve accepted safety (steady-state unbound trough plasma concentration [fCmin] of <10 mg/liter)- and efficacy (free, unbound plasma concentration-to-MIC ratio [fCmax/MIC] of ≥8)-linked targets. In addition, an adaptive resistance PD (ARPD) model of Pseudomonas aeruginosa was built based on literature time-kill curve data and linked to the PK model to perform PK-ARPD simulations and compare results with those of the probability approach. Using the probability approach, an amikacin dose of 60 mg/kg administered once daily is expected to achieve the target fCmax/MIC in 80% of pediatric patients weighing 8 to 70 kg with a 97.5% probability, and almost all patients were predicted to have fCmin of <10 mg/liter. However, PK-ARPD simulation predicted that 60 mg/kg/day is unlikely to suppress bacterial resistance with repeated dosing. Furthermore, PK-ARPD simulation suggested that amikacin at 90 mg/kg, given in two divided doses (45 mg/kg twice a day), is expected to hit safety and efficacy targets and is associated with a lower rate of bacterial resistance. The disagreement between the two methods is due to the inability of the probability approach to predict development of drug resistance with repeated dosing. This originates from the use of PK-PD indices based on the MIC that neglects measurement errors, ignores the time course dynamic nature of bacterial growth and killing, and incorrectly assumes the MIC to be constant during treatment.
More Related Videos
 10:02
Whole-body PET/MRI of Pediatric Patients: The Details That Matter
Published on: December 19, 2017
 06:14
Optimized LC-MS/MS Method for the High-throughput Analysis of Clinical Samples of Ivacaftor, Its Major Metabolites, and Lumacaftor in Biological Fluids of Cystic Fibrosis Patients
Published on: October 15, 2017
Related Concept Videos
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:24
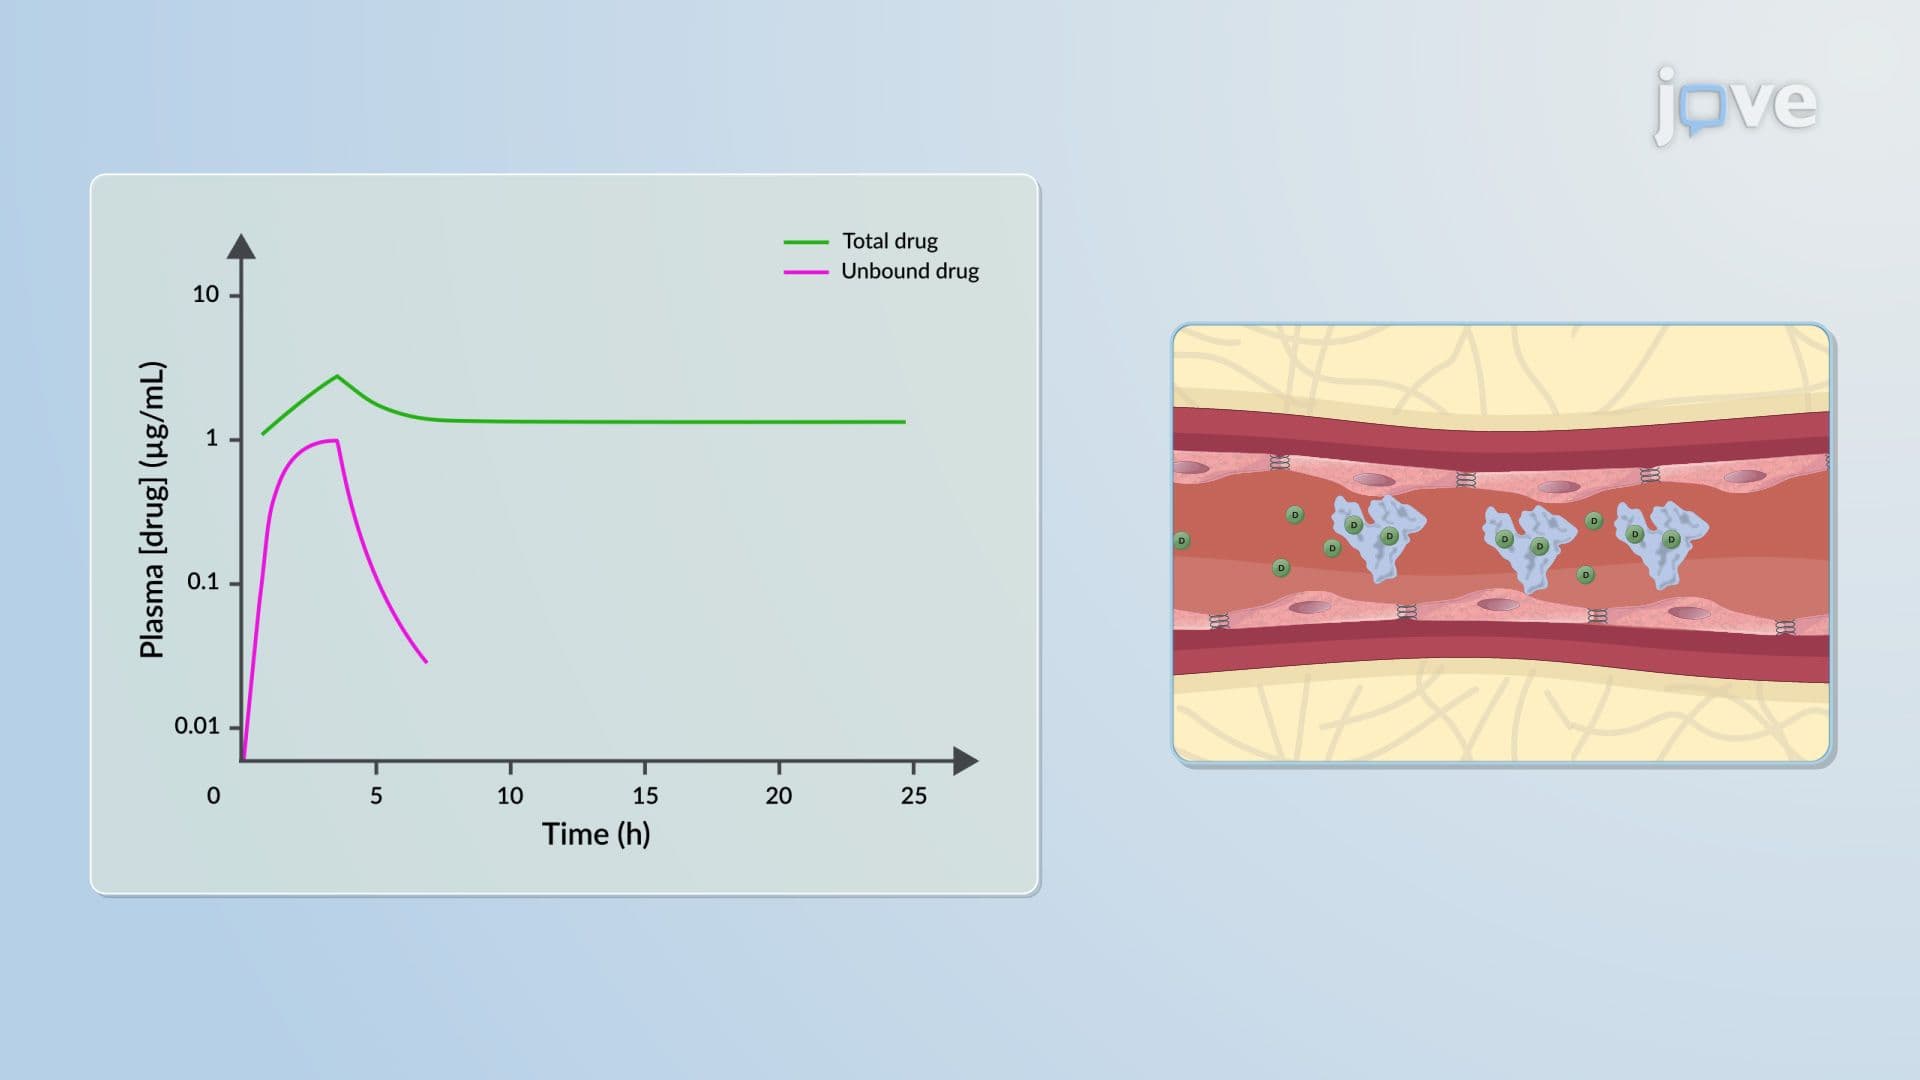
Pharmacokinetic–Pharmacodynamic Relationship: Problems
 01:28
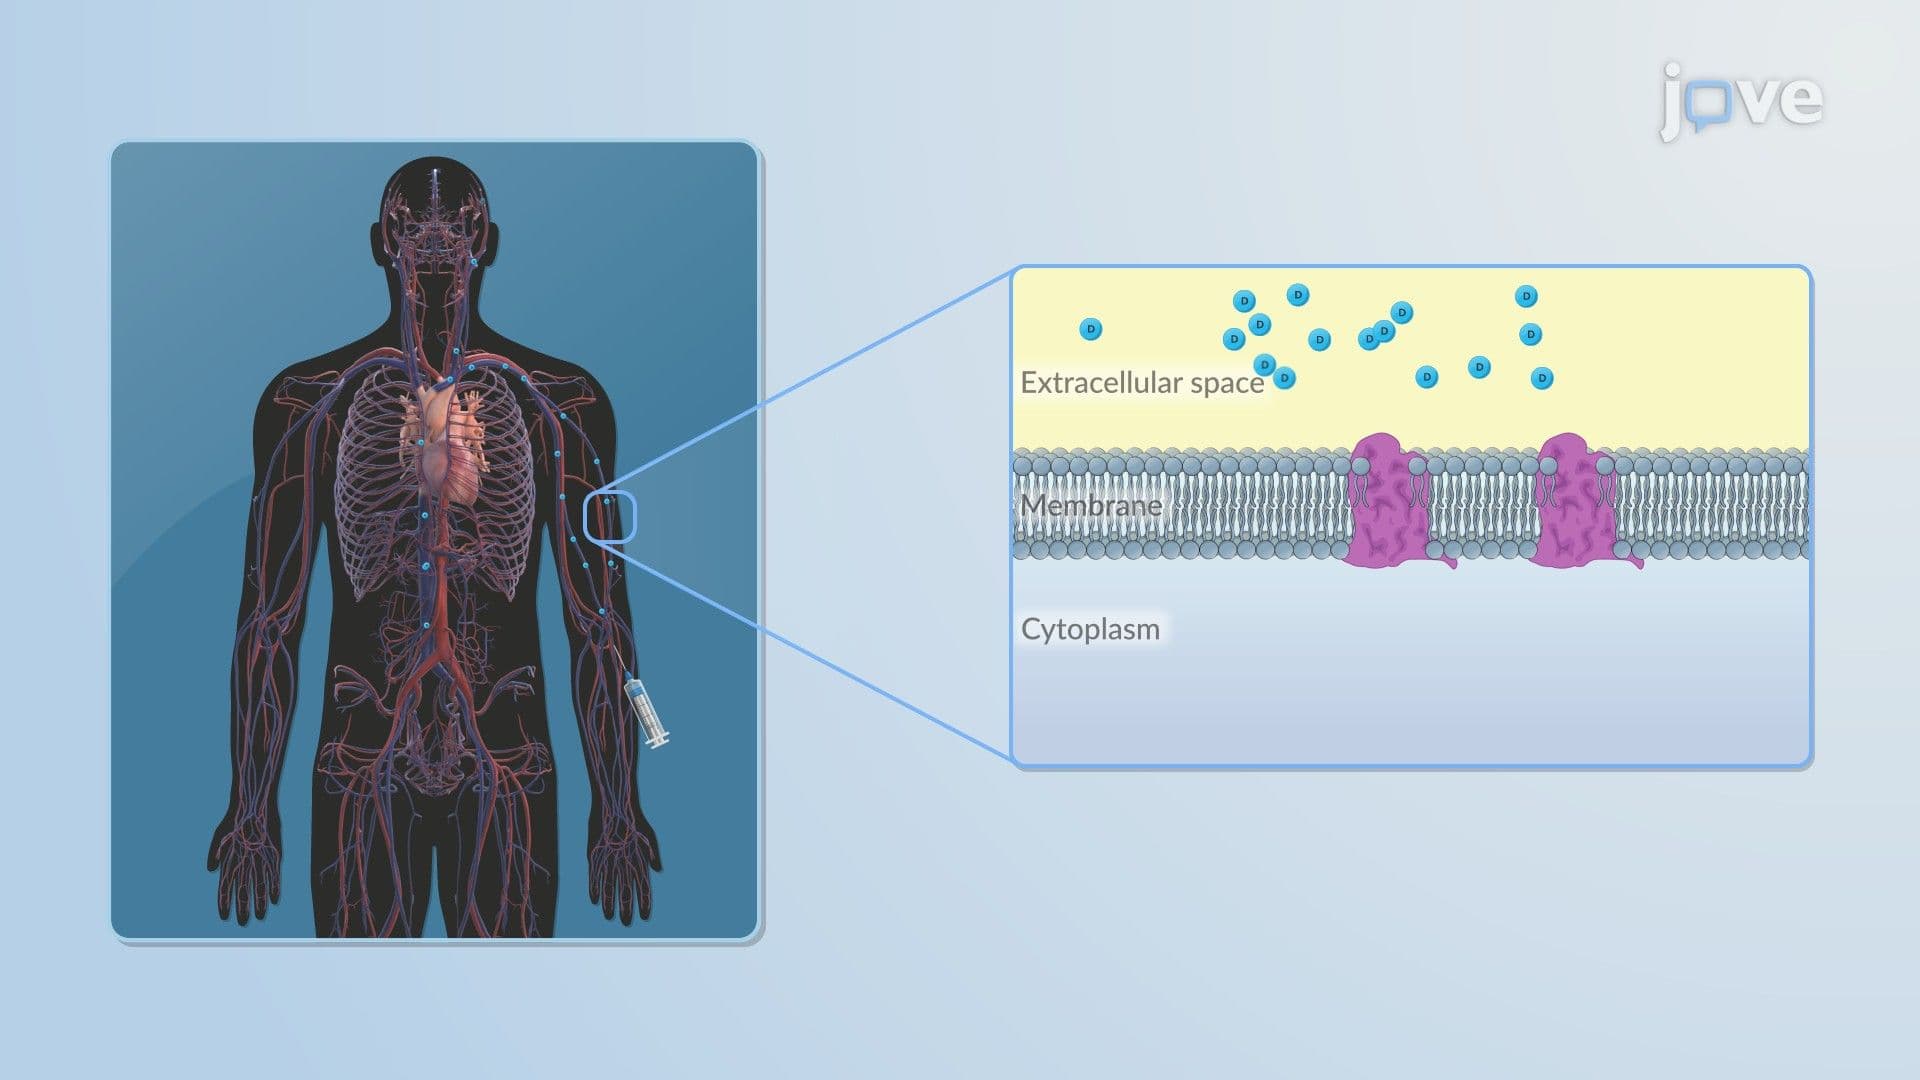
Pharmacokinetic–Pharmacodynamic Relationship: Dose to Pharmacological Effect