Related Experiment Video
Updated: Feb 15, 2026
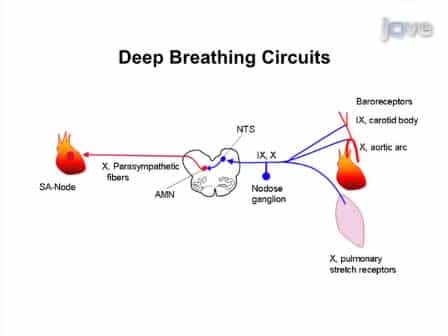

Quantitative Autonomic Testing
Published on: July 19, 2011
Cardiac autonomic neuropathy: Risk factors, diagnosis and treatment
Victoria A Serhiyenko1, Alexandr A Serhiyenko2
1Department of Endocrinology, Lviv National Medical University Named by Danylo Halitsky, Lviv 79010, Ukraine. serhiyenko@inbox.ru.

Abstract:
Cardiac autonomic neuropathy (CAN) is a serious complication of diabetes mellitus (DM) that is strongly associated with approximately five-fold increased risk of cardiovascular mortality. CAN manifests in a spectrum of things, ranging from resting tachycardia and fixed heart rate (HR) to development of "silent" myocardial infarction. Clinical correlates or risk markers for CAN are age, DM duration, glycemic control, hypertension, and dyslipidemia (DLP), development of other microvascular complications. Established risk factors for CAN are poor glycemic control in type 1 DM and a combination of hypertension, DLP, obesity, and unsatisfactory glycemic control in type 2 DM. Symptomatic manifestations of CAN include sinus tachycardia, exercise intolerance, orthostatic hypotension (OH), abnormal blood pressure (BP) regulation, dizziness, presyncope and syncope, intraoperative cardiovascular instability, asymptomatic myocardial ischemia and infarction. Methods of CAN assessment in clinical practice include assessment of symptoms and signs, cardiovascular reflex tests based on HR and BP, short-term electrocardiography (ECG), QT interval prolongation, HR variability (24 h, classic 24 h Holter ECG), ambulatory BP monitoring, HR turbulence, baroreflex sensitivity, muscle sympathetic nerve activity, catecholamine assessment and cardiovascular sympathetic tests, heart sympathetic imaging. Although it is common complication, the significance of CAN has not been fully appreciated and there are no unified treatment algorithms for today. Treatment is based on early diagnosis, life style changes, optimization of glycemic control and management of cardiovascular risk factors. Pathogenetic treatment of CAN includes: Balanced diet and physical activity; optimization of glycemic control; treatment of DLP; antioxidants, first of all α-lipoic acid (ALA), aldose reductase inhibitors, acetyl-L-carnitine; vitamins, first of all fat-soluble vitamin B1; correction of vascular endothelial dysfunction; prevention and treatment of thrombosis; in severe cases-treatment of OH. The promising methods include prescription of prostacyclin analogues, thromboxane A2 blockers and drugs that contribute into strengthening and/or normalization of Na+, K+-ATPase (phosphodiesterase inhibitor), ALA, dihomo-γ-linolenic acid (DGLA), ω-3 polyunsaturated fatty acids (ω-3 PUFAs), and the simultaneous prescription of ALA, ω-3 PUFAs and DGLA, but the future investigations are needed. Development of OH is associated with severe or advanced CAN and prescription of nonpharmacological and pharmacological, in the foreground midodrine and fludrocortisone acetate, treatment methods are necessary.


Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:24
Drug Toxicity: Risk factors
 01:22
Autonomic Nervous System
The ANS comprises two main divisions: the sympathetic and parasympathetic divisions. These divisions function antagonistically to maintain a dynamic...
 01:12
Relative Risk
 01:26
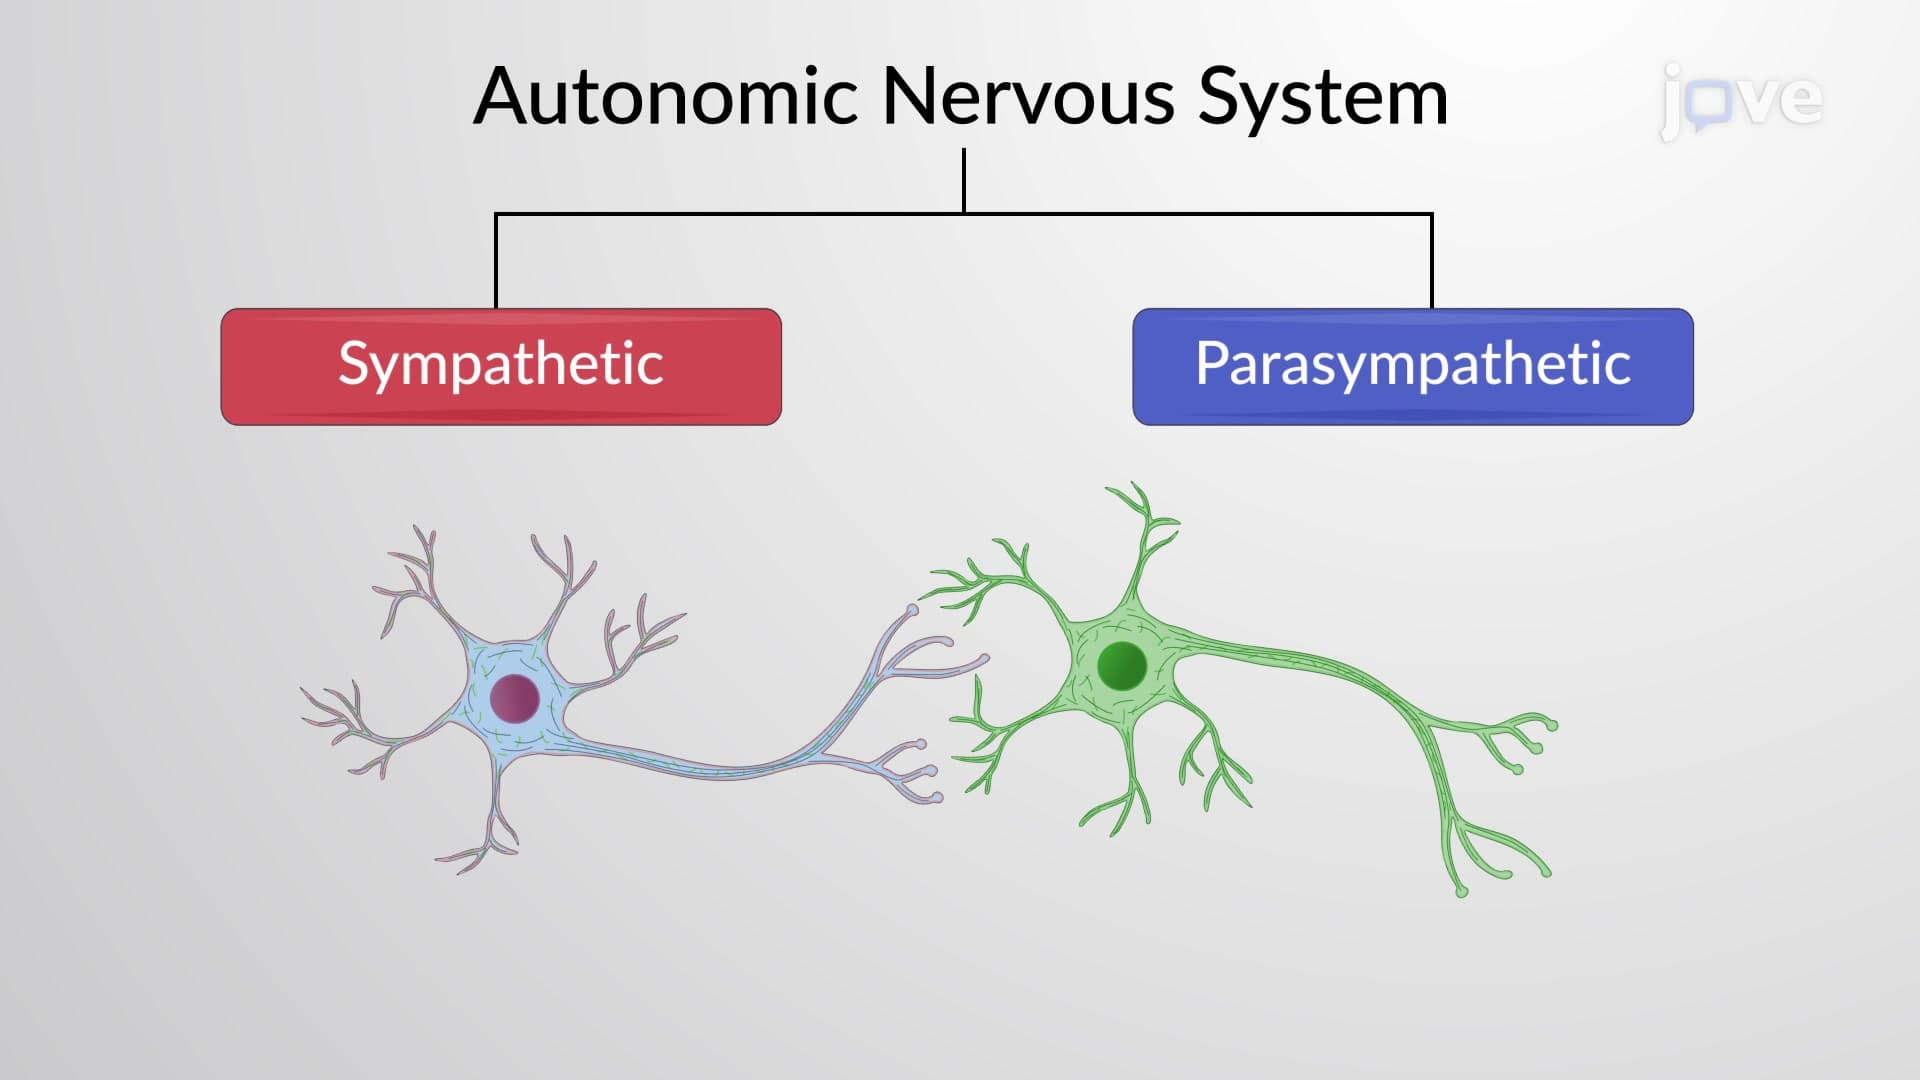
Autonomic Nervous System: Overview
 01:18
Disorders of the Autonomic Nervous System
Raynaud's disease, also known as Raynaud's...