Related Experiment Video
Updated: Feb 15, 2026

Veno-Venous Extracorporeal Membrane Oxygenation in a Mouse
Published on: October 24, 2018
Extracorporeal membrane oxygenation as a direct bridge to heart transplantation in adults
Shinichi Fukuhara1, Koji Takeda1, Paul A Kurlansky1
1Division of Cardiac, Thoracic, and Vascular Surgery, Columbia University Medical Center, New York, NY.

Objectives:
Venoarterial extracorporeal membrane oxygenation (ECMO) use as a bridge to transplant is extremely infrequent in adults. We investigated patient outcomes of the use of ECMO as bridge to transplant.
Methods:
United Network of Organ Sharing provided de-identified patient-level data. Between 2003 and 2016, 25,168 adult recipients were identified. Of these, 107 (0.4%) were bridged with ECMO and 6148 (24.4%) were bridged with a continuous-flow left ventricular assist device.
Results:
Patients in ECMO group were younger, more likely to have severely disabled functional status, shorter waitlist time, and were more frequently mechanically ventilated than were patients in the continuous-flow left ventricular assist device group. Kaplan-Meier analysis demonstrated estimated posttransplant survival of 73.1% versus 93.1% at 90 days (P < .001) and 67.4% versus 82.4% at 3 years (P < .001) in ECMO and continuous-flow left ventricular assist device groups, respectively. Analysis of a propensity-matched cohort still demonstrated a lower survival in ECMO group at 90 days (74.8% vs 88.8%; P = .025) and 3 years (69.3% vs 82.2%; P = .054). Among the ECMO patients, multivariable logistic and Cox regression analyses showed model for end-stage liver disease excluding international normalized ratio (MELD-XI) score to be the sole contributor to both 90-day (odds ratio, 1.94; 95% confidence interval, 1.00-3.76; P = .050) and 3-year mortality (hazard ratio, 1.47; 95% confidence interval, 1.16-1.88; P = .002). ECMO-supported patients with a high MELD-XI score (>17) were associated with poor posttransplant survival compared with those with a low MELD-XI score (<13) (90 day, 54.4% vs 85.0% [P < .001] and 3 year, 49.5% vs 73.5% [P < .001]).
Conclusions:
Bridge to transplant with ECMO was associated with increased early/mid-term mortality, especially in patients with a high MELD-XI score who demonstrated > 50% 3-year mortality. These findings may help to inform future organ allocation policies.

Related Concept Videos
 01:15
Design Example: Strain Gauge Bridge or Wheatstone Bridge
 01:29
Wheatstone Bridge
Thus, for accurate resistance measurements, a...
 01:24
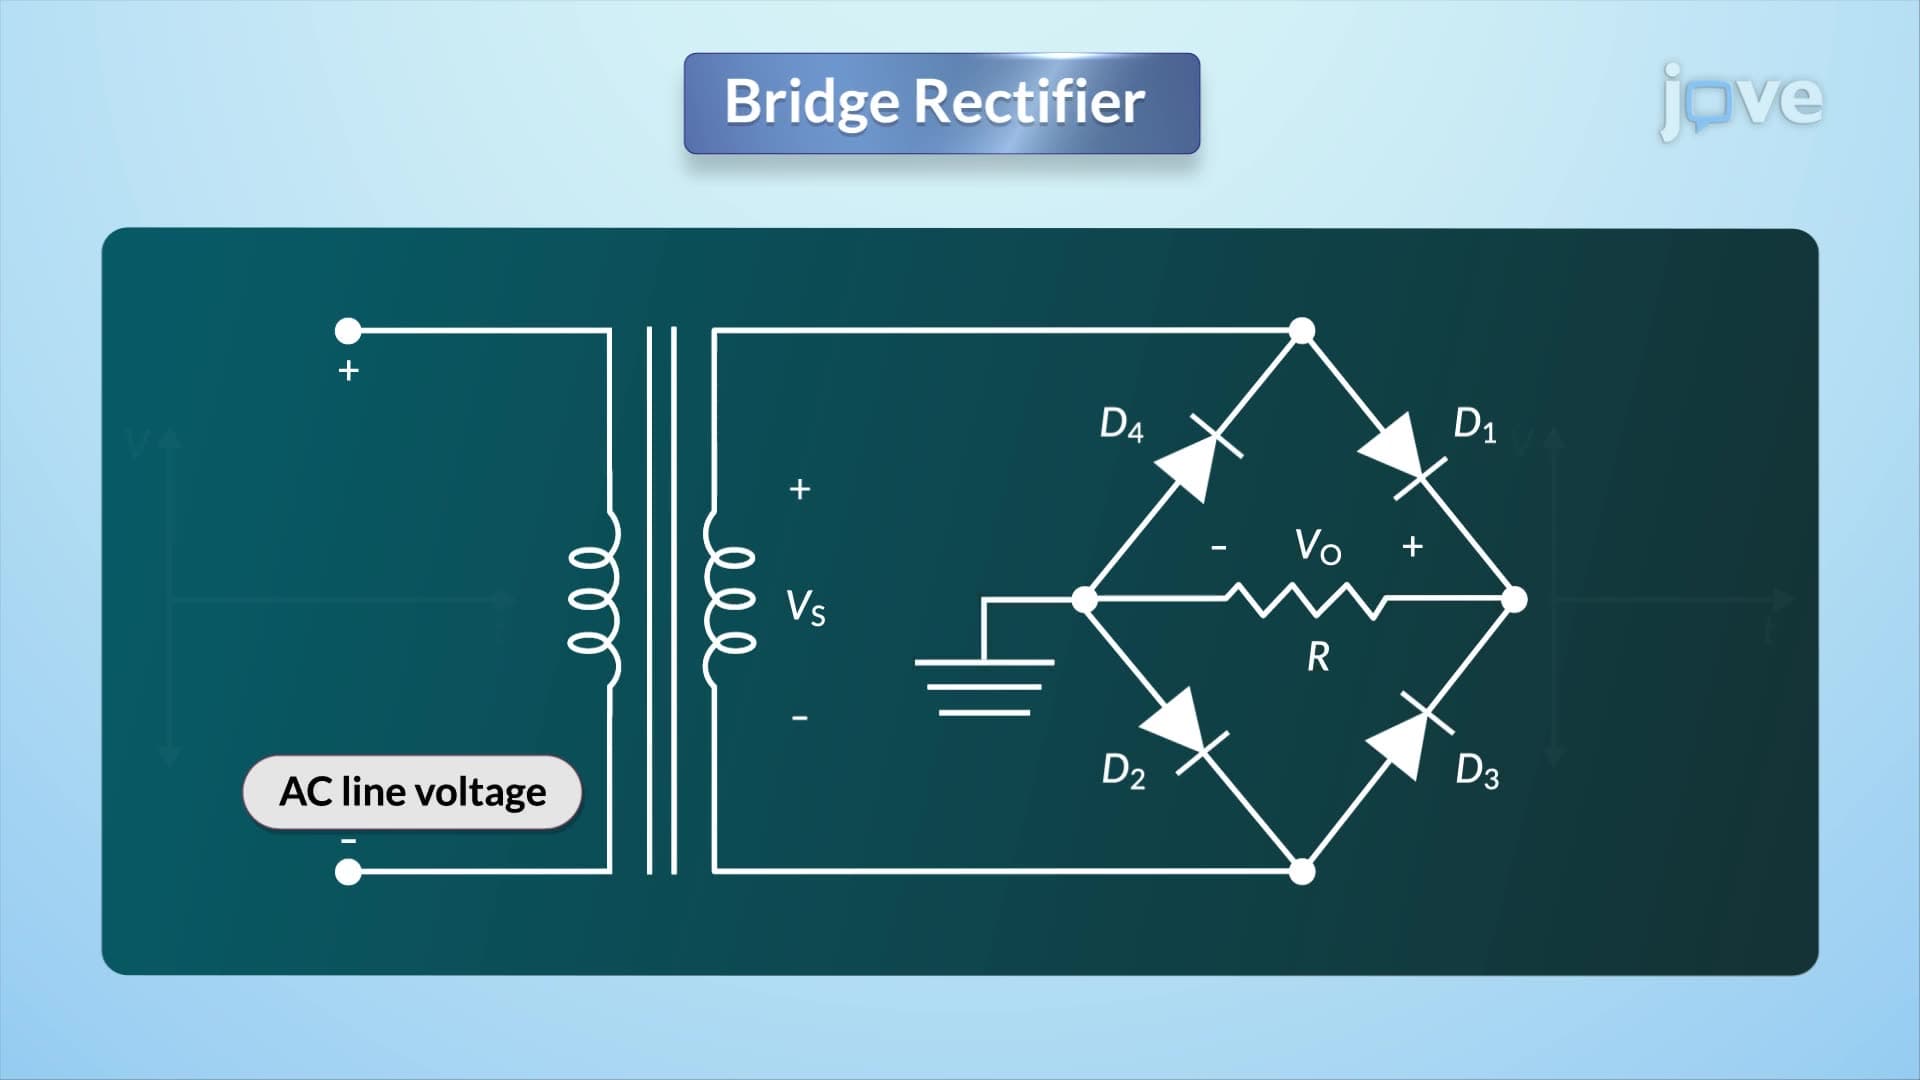
Bridge rectifier
Operationally, the bridge rectifier allows current flow through two of its diodes during each...
 01:27
Anatomy of the Heart
 01:26
Cross-bridge Cycle
 01:25
Extracorporeal Removal of Drugs: Hemoperfusion and Hemofiltration