Related Experiment Video
Updated: Feb 15, 2026
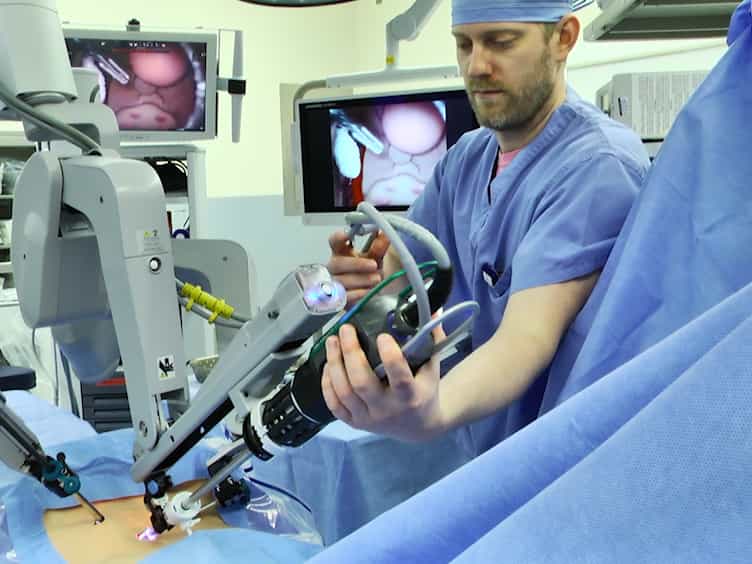

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Analysis of postdischarge costs following emergent general surgery in elderly patients
Gilgamesh J Eamer1, Fiona Clement1, Jenelle L Pederson1
1From the Department of Surgery, Faculty of Medicine and Dentistry, University of Alberta, Edmonton, Alta. (Eamer, Pederson, Churchill, Khadaroo); the Department of Community Health Sciences, O'Brien Institute for Public Health, University of Calgary, Calgary, Alta. (Clement); the School of Public Health, University of Alberta, Edmonton, Alta. (Gilgamesh); and the Department of Surgery, University of Alberta, Edmonton, Alta. (Khadaroo).

Background:
As populations age, more elderly patients will undergo surgery. Frailty and complications are considered to increase in-hospital cost in older adults, but little is known on costs following discharge, particularly those borne by the patient. We examined risk factors for increased cost and the type of costs accrued following discharge in elderly surgical patients.
Methods:
Acute abdominal surgery patients aged 65 years and older were prospectively enrolled. We assessed baseline clinical characteristics, including Clinical Frailty Scale (CFS) scores. We calculated 6-month cost (in Canadian dollars) from patient-reported use following discharge according to the validated Health Resource Utilization Inventory. Primary outcomes were 6-month overall cost and cost for health care services, medical products and lost productive hours. Outcomes were log-transformed and assessed in multivariable generalized linear and zero-inflated negative binomial regressions and can be interpreted as adjusted ratios (AR). Complications were assessed according to Clavien-Dindo classification.
Results:
We included 150 patients (mean age 75.5 ± 7.6 yr; 54.1% men) in our analysis; 10.8% had major and 43.2% had minor complications postoperatively. The median 6-month overall cost was $496 (interquartile range $140-$1948). Disaggregated by cost type, frailty independently predicted increasing costs of health care services (AR 1.76, 95% confidence interval [CI] 1.43-2.18, p < 0.001) and medical products (AR 1.61, 95% CI 1.15-2.25, p = 0.005), but decreasing costs in lost productive hours (AR 0.39, p = 0.002). Complications did not predict increased cost.
Conclusion:
Frail patients accrued higher health care services and product costs, but lower costs from lost productive hours. Interventions in elderly surgical patients should consider patient-borne cost in older adults and lost productivity in less frail patients.
Trial Registration:
NCT02233153 (clinicaltrials.gov).
More Related Videos
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
 04:05
Author Spotlight: Unveiling Prognostic Indicators in Heart Failure - The Role of Phase Angle and Bioelectrical Impedance Analysis
Published on: June 30, 2023
Related Concept Videos
 01:27
Emerging Adulthood
 01:30
Introduction Cardiac Emergencies
 01:29
Applications of GIS: Disaster Management and Emergency Response
 01:13
Patient-centered Care
 01:15
Drug Dosing: Geriatric Patients
 01:21
Drug Dosing: Obese Patients