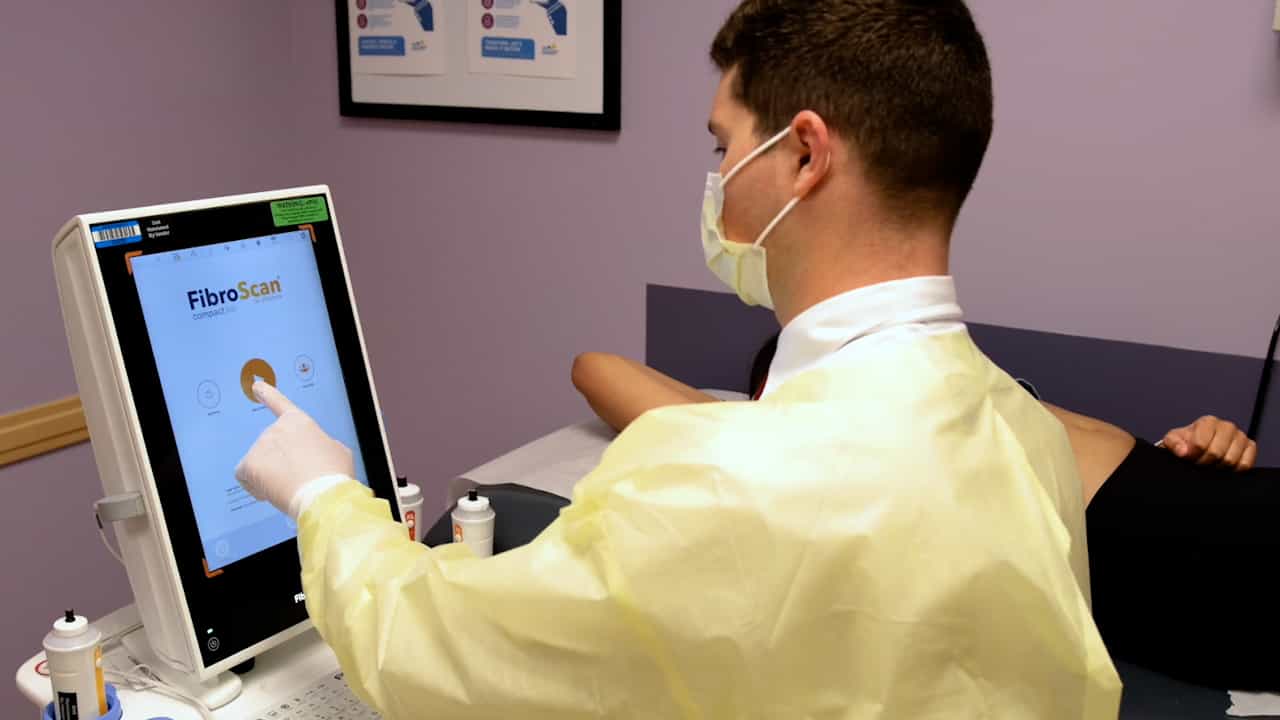
Transient elastography for non-invasive evaluation of post-transplant liver graft fibrosis in children
Tiziana Vinciguerra1, Andrea Brunati2, Ezio David3
1Gastroenterologia e Epatologia Pediatrica, Department of Pediatrics, Azienda Ospedaliera-Universitaria Citta`della Salute e della Scienza, Turin, Italy.

Insights
Transient elastography (TE) is a reliable, non-invasive method for assessing liver graft fibrosis in children post-liver transplant (LT). This technique can help reduce the need for protocol liver biopsies by accurately identifying significant fibrosis.
Area of Science:
- Hepatology
- Pediatric Gastroenterology
- Transplant Surgery
Background:
- Progressive fibrosis impacts graft survival in pediatric liver transplant (LT) recipients.
- Protocol liver biopsies are standard but invasive, with increasing intervals post-transplant.
- Non-invasive methods are needed to monitor fibrosis in asymptomatic children.
Purpose of the Study:
- To evaluate the reliability of transient elastography (TE) for assessing liver graft fibrosis in pediatric LT recipients.
- To compare TE and APRI index results against histological fibrosis scores.
- To determine if TE can reduce the need for protocol liver biopsies.
Main Methods:
- 36 pediatric LT recipients underwent TE and liver biopsy within a year.
- Fibrosis was staged using the METAVIR histological scoring system.
- TE stiffness values and APRI index were correlated with METAVIR scores.
Main Results:
- TE showed a statistically significant correlation with METAVIR fibrosis scores (P=.005).
- TE demonstrated good diagnostic performance for significant fibrosis (AUROC=0.865), outperforming APRI (AUROC=0.592).
- A TE cutoff of 5.6 kPa accurately predicted significant fibrosis (METAVIR F≥2) with high sensitivity and specificity.
Conclusions:
- TE is a reliable, non-invasive tool for monitoring liver graft fibrosis in pediatric LT patients.
- TE can help identify children needing liver biopsy, potentially reducing protocol biopsies.
- This method aids in managing long-term graft health in pediatric liver transplant recipients.
Abstract:
As graft survival in pediatric LT is often affected by progressive fibrosis, numerous centers carry out protocol liver biopsies. Follow-up biopsy protocols differ from center to center, but all biopsies are progressively spaced out, as time from transplant increases. Therefore, there is a need for non-invasive techniques to evaluate graft fibrosis progression in those children who have no clinical or serological signs of liver damage. Indirect markers, such as the APRI, should be relied on with caution because their sensitivity in predicting fibrosis can be strongly influenced by the etiology of liver disease, severity of fibrosis, and patient age. A valid alternative could be TE, a non-invasive technique already validated in adults, which estimates the stiffness of the cylindrical volume of liver tissue, 100-fold the size of a standard needle biopsy sample. The aims of this study were to evaluate the reliability of TE in children after LT and to compare both the TE and the APRI index results with the histological scores of fibrosis on liver biopsies. A total of 36 pediatric LT recipients were studied. All patients underwent both TE and biopsy within a year (median interval -0.012 months) at an interval from LT of 0.36 to 19.47 years (median 3.02 years). Fibrosis was assessed on the biopsy specimens at histology and staged according to METAVIR. There was a statistically significant correlation between TE stiffness values and METAVIR scores (P = .005). The diagnostic accuracy of TE for the diagnosis of significant fibrosis (F ≥ 2) was measured as the area under the curve (AUROC = 0.865), and it demonstrated that the method had a good diagnostic performance. APRI was not so accurate in assessing graft fibrosis when compared to METAVIR (AUROC = 0.592). A liver stiffness cutoff value of 5.6 kPa at TE was identified as the best predictor for a significant graft fibrosis (METAVIR F ≥ 2) on liver biopsy, with a 75% sensitivity, a 95.8% specificity, a 90% positive predictive value, and an 88.5% negative predictive value. These data suggest that TE may represent a non-invasive, reliable tool for the assessment of graft fibrosis in the follow-up of LT children, alerting the clinicians to the indication for a liver biopsy, with the aim of reducing the number of protocol liver biopsies.
Related Concept Videos
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation,...
 01:22
Series R—L Circuit Transients
Using Kirchhoff's Voltage Law (KVL) to analyze this circuit helps determine the total asymmetrical fault current, which consists...
 01:24
Cystic Fibrosis: Management
Sinus disease and chronic...
 01:24
Transient and Steady-state Response
These test signals are integral in designing control systems to exhibit two key performance aspects: transient response and steady-state...
 01:29
Drug Dosing: Infants and Children
 01:27
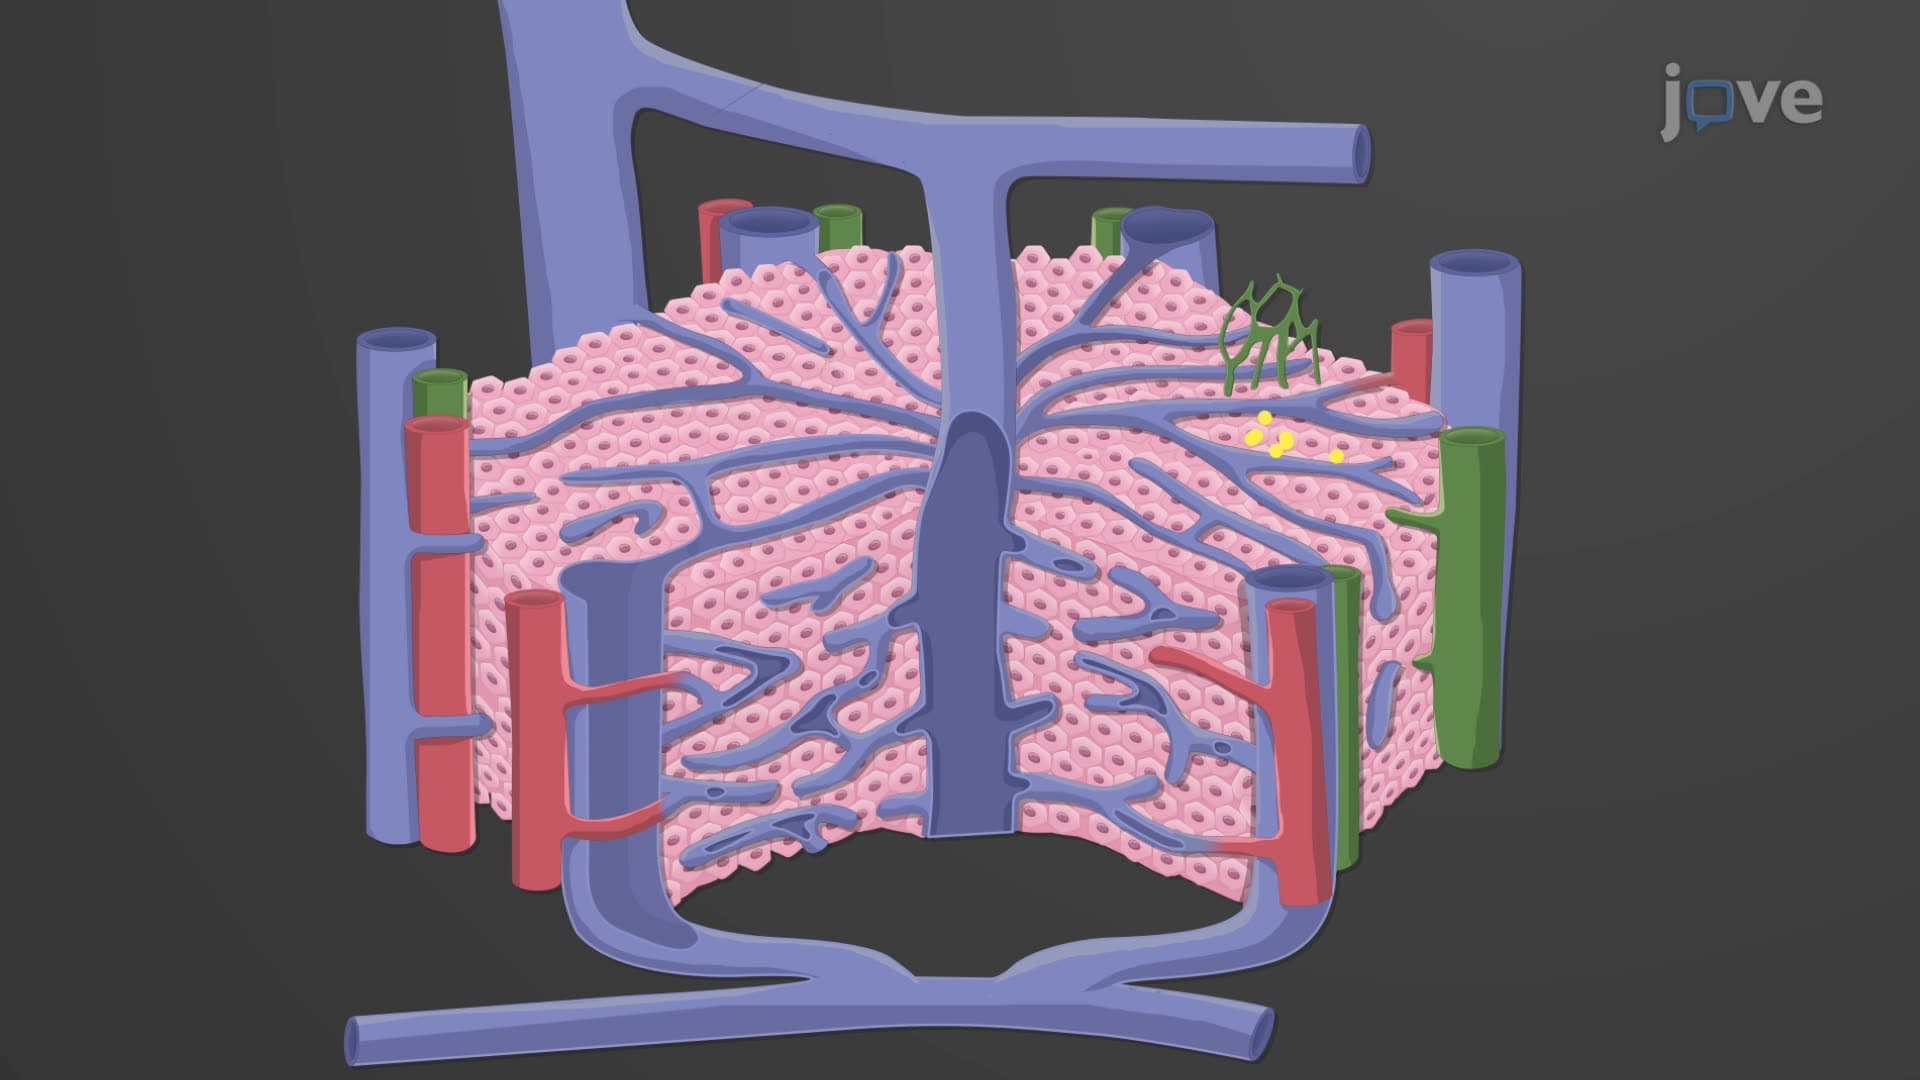
Liver Histology
Hepatocytes perform a variety of essential functions. They secrete...