Related Experiment Video
Updated: Feb 15, 2026

Detection of miRNA Targets in High-throughput Using the 3'LIFE Assay
Published on: May 25, 2015
Calculating census tract-based life expectancy in New York state: a generalizable approach
Thomas O Talbot1, Douglas H Done2, Gwen D Babcock3
1Department of Epidemiology and Biostatistics, University of Albany School of Public Health, Rensselaer, NY, USA. thmstalbot@gmail.com.

Background:
Life expectancy at birth (LE) has been calculated for states and counties. LE estimates at these levels mask health disparities in local communities. There are no nationwide estimates at the sub-county level. We present a stepwise approach for calculating LE using census tracts in New York state to identify health disparities.
Methods:
Our study included 2751 census tracts in New York state, but excluded New York City. We used population data from the 2010 United States Census and 2008-2010 mortality data from the state health department. Tracts were assigned to 99.97% of the deaths. We removed tracts which had a majority of people living in group quarters. Deaths in these tracts are often recorded elsewhere. Of the remaining 2679 tracts, 6.6% of the tracts had standard errors ≥ 2 years. A geographic aggregation tool was used to aggregate tracts with fewer than 60 deaths, and then aggregate areas that had standard errors of ≥ 2 years.
Results:
Aggregation resulted in a 9.9% reduction in the number of areas. Tracts with < 2% of population living below the poverty level had a LE of 82.8 years, while tracts with a poverty level ≥ 25% had a LE of 75.5. We observed differences in LE in border areas, of up to 10.4 years, when excluding or including deaths of study area residents that occurred outside the study area. The range and standard deviation at the county level (77.5-82.8, SD = 1.2 years) were smaller than our final sub-county areas (64.7-92.0, SD = 3.3 years). The correlation between LE and poverty were similar and statistically significant (p < 0.0001) at the county (r = - 0.58) and sub-county level (r = - 0.58). The correlations between LE and percent African-American at the county level were (r = 0.11, p = 0.43) and at the sub-county level (r = - 0.25, p < 0.0001).
Conclusion:
The proposed approach for geocoding and aggregation of mortality and population data provides a solution for health departments to produce stable empirically-derived LE estimates using data coded to the tract. Reliable estimates within sub-county areas are needed to aid public health officials in focusing preventive health programs in areas where health disparities would be masked by county level estimates.
Related Concept Videos
 01:15
Expected Value
 03:55
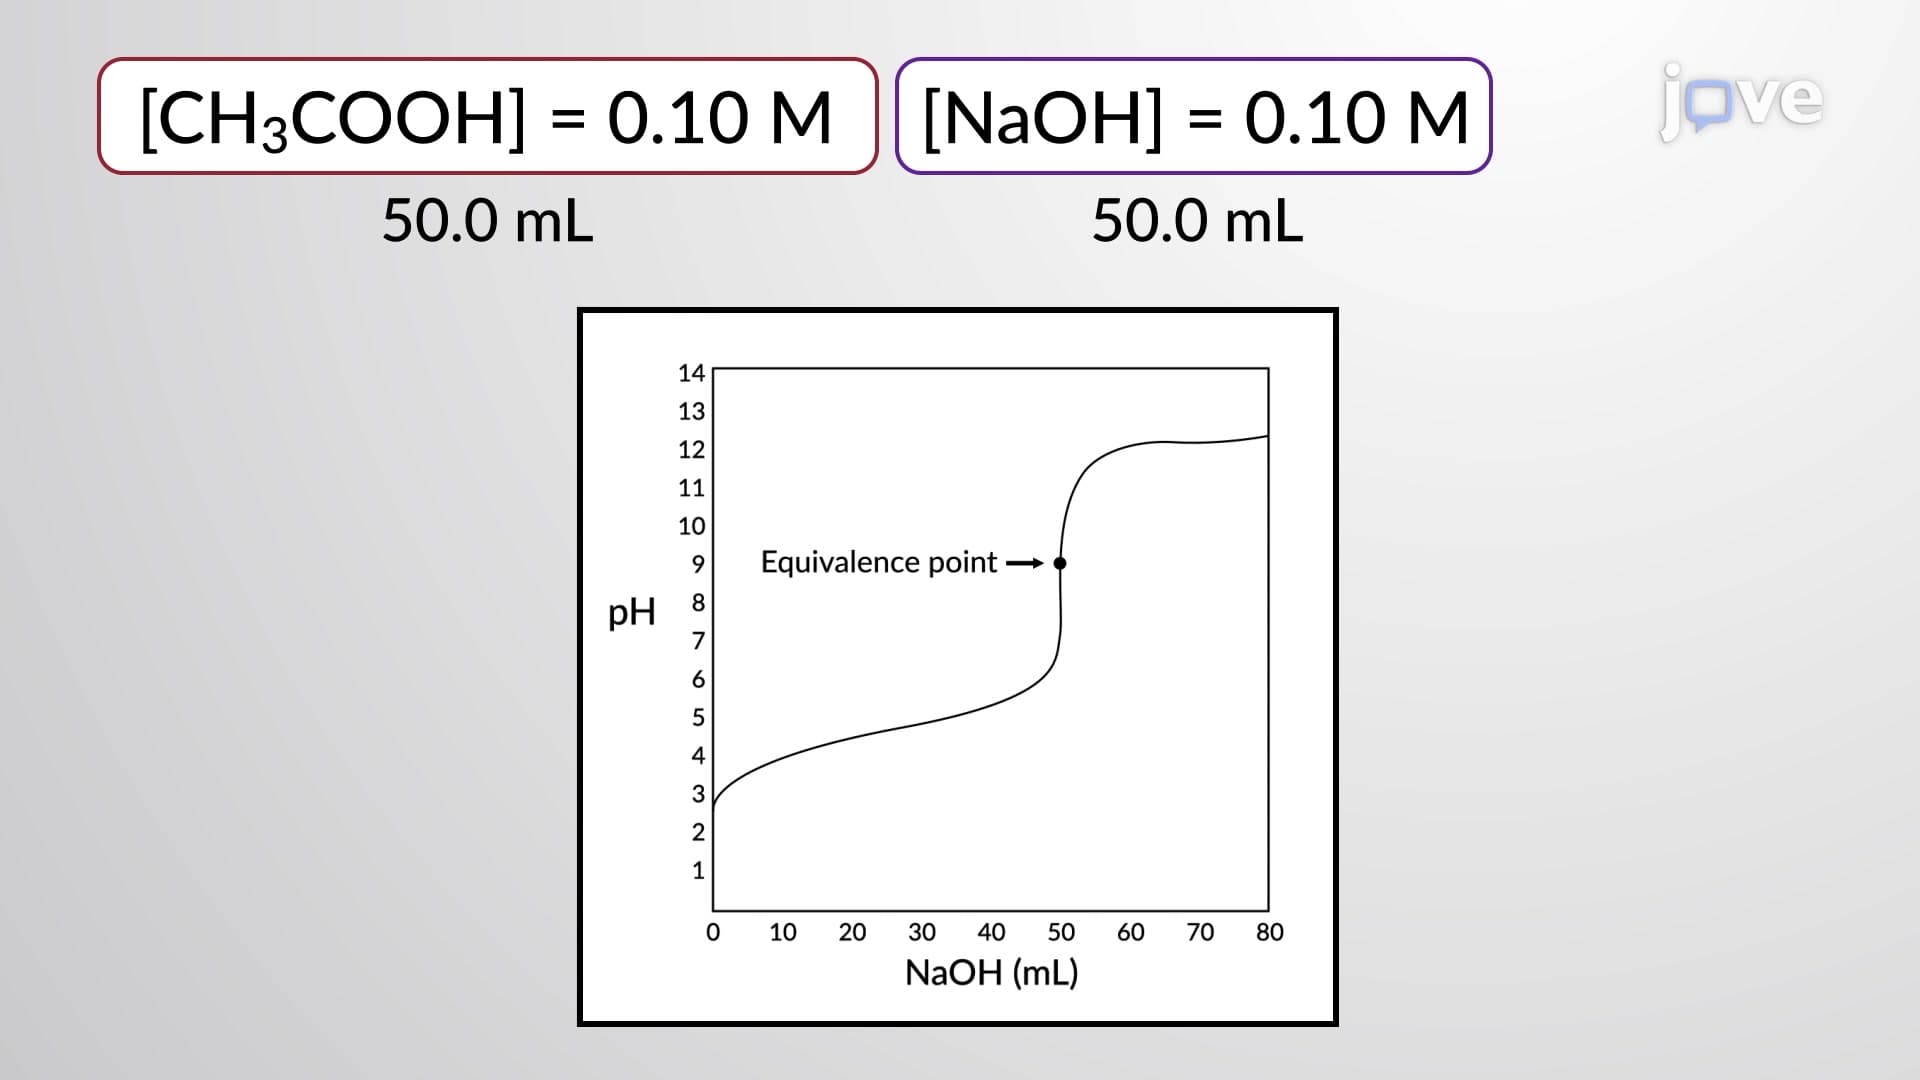
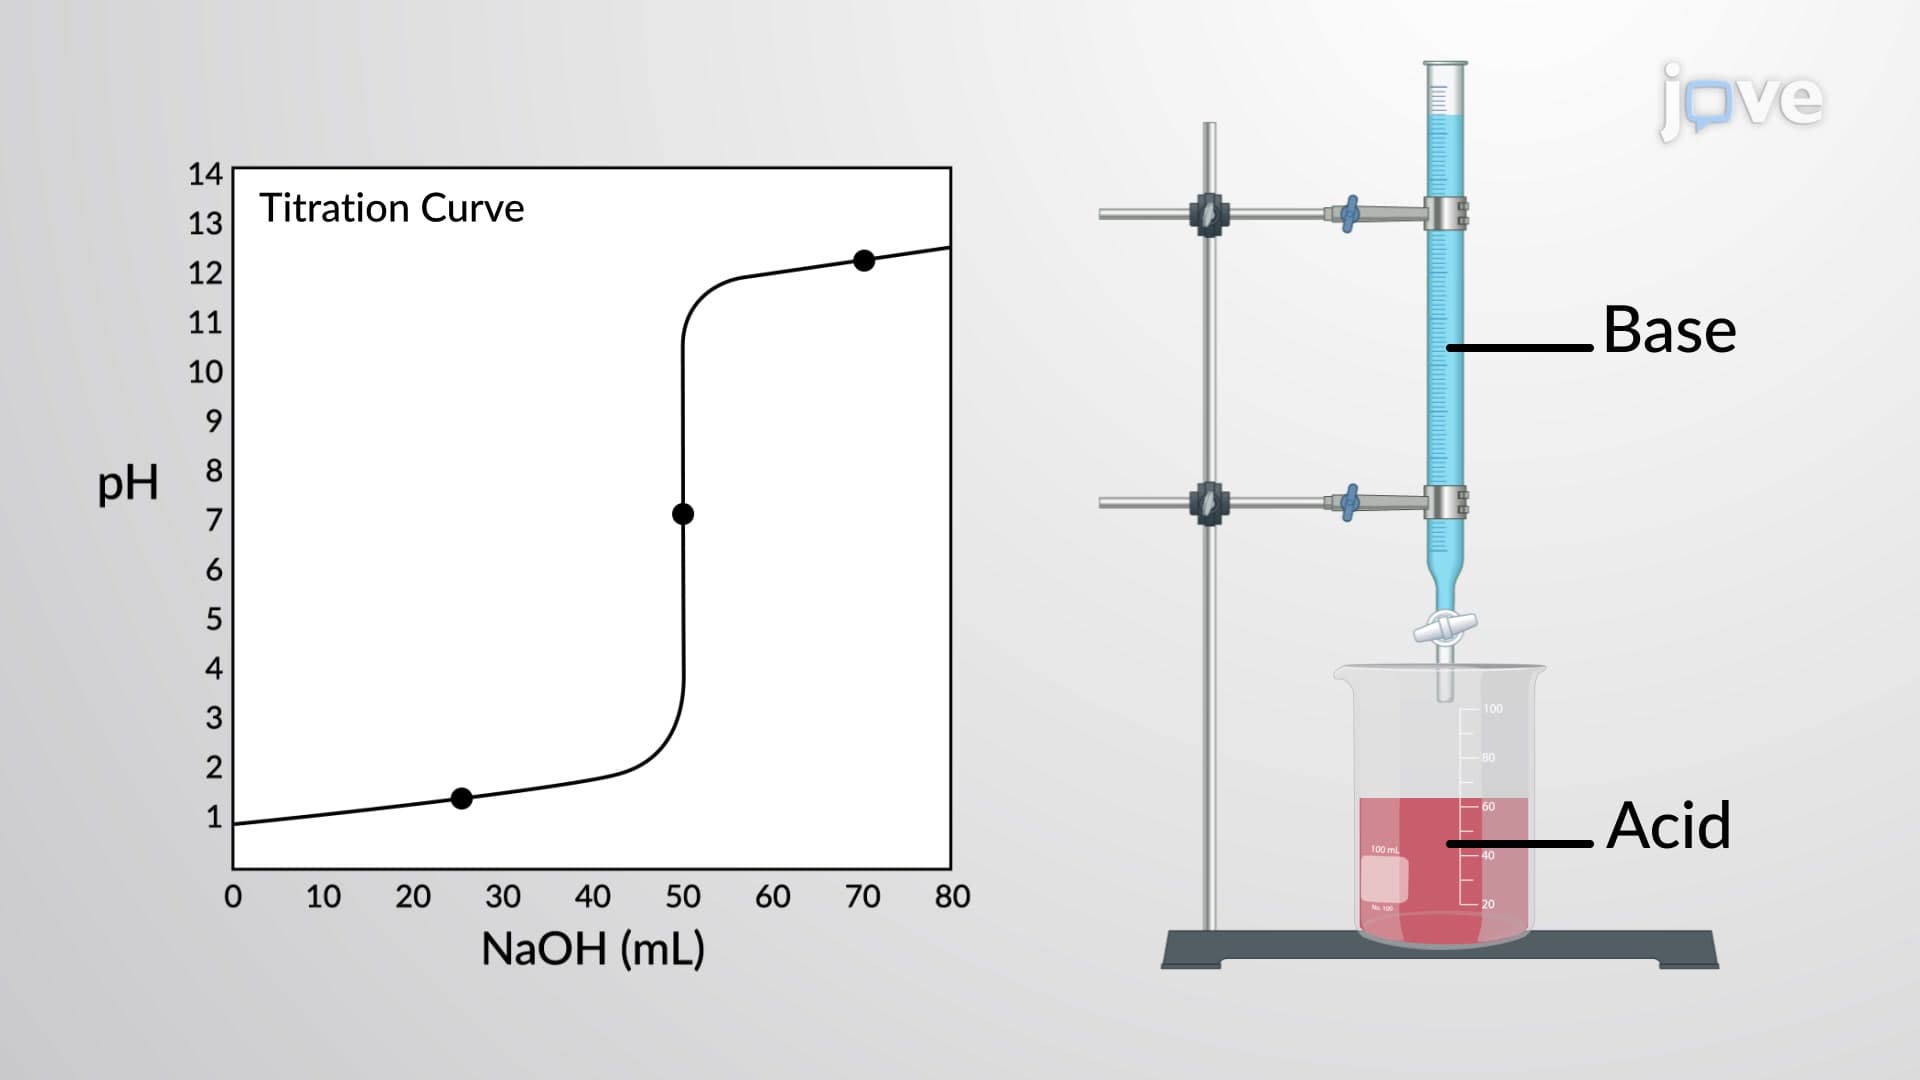
Titration Calculations: Weak Acid - Strong Base
For the titration of 25.00 mL of 0.100 M CH3CO2H with 0.100 M NaOH, the reaction can be represented as:
 02:28
Titration Calculations: Strong Acid - Strong Base
A titration is carried out for 25.00 mL of 0.100 M HCl (strong acid) with 0.100 M of a strong base NaOH. The pH at different volumes of added base solution can be calculated as follows:
(a) Titrant volume = 0 mL. The solution pH is due to the acid ionization of HCl. Because this is a strong acid, the ionization is complete and the hydronium ion molarity is 0.100 M. The pH of the solution is then:
 01:21
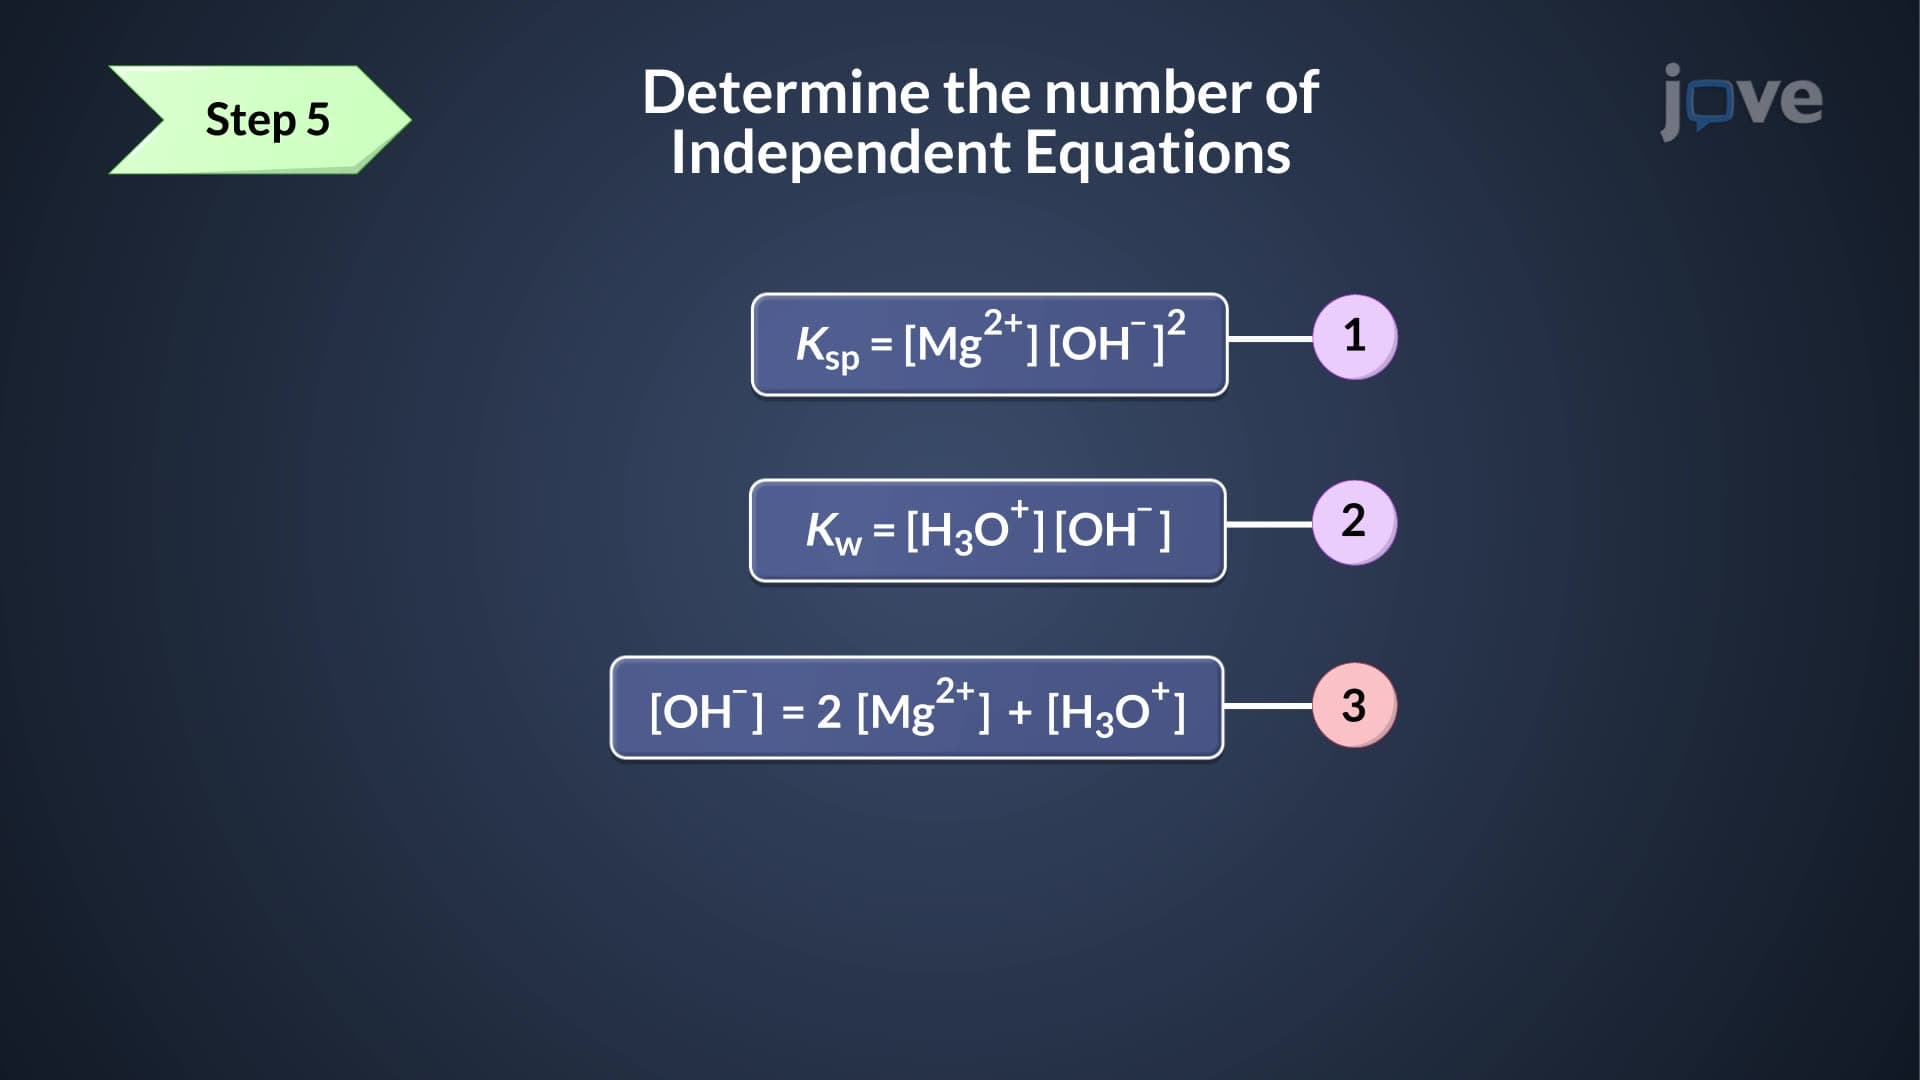
Chemical Equilibria: Systematic Approach to Equilibrium Calculations
The first step is to identify all the chemical reactions involved, The...
 02:42
Half-life of a Reaction
 01:23
Characteristics of Life