Related Experiment Video
Updated: Feb 15, 2026
Double Direct Injection of Blood into the Cisterna Magna as a Model of Subarachnoid Hemorrhage
Published on: August 30, 2020
Evaluation and Management of Spinal Subarachnoid Hemorrhage in a Patient with Lupus Vasculitis
Ryan M Glynn1, Madeline R Garza1, Franco M Campanella2
1Chicago Medical School, Rosalind Franklin University of Medicine and Science, North Chicago, IL, USA.

BACKGROUND Isolated spinal artery subarachnoid hemorrhage is a rare occurrence in the general population, but occurs more commonly as one of many neurologic sequela of systemic lupus erythematosus (SLE). The etiology of a neurologic deficit in an SLE patient is often multifactorial. Comorbid conditions, such as antiphospholipid antibody syndrome, predispose to stroke. Other diagnoses, including transverse myelitis, may also be attributed to local inflammation. CASE REPORT A 37-year-old woman with SLE and antiphospholipid antibody syndrome experienced severe back pain followed by sudden paralysis and sensory loss below the T2 level. She remained alert and oriented on examination, with neurologic exam positive for diminished strength in the arms and with total loss of sensation and strength in the legs. Diagnostic workup was limited due to a contrast allergy and severe lupus nephritis; however, initial imaging showed increased cervical-thoracic spinal cord signal and concern for acute blood in the subarachnoid space. No neurosurgical intervention occurred, and the patient was treated with high-dose steroids and plasmapheresis for a possible transverse myelitis and non-aneurysmal subarachnoid hemorrhage. The patient received further neurologic and rheumatologic workup and remained neurologically stable, with improvement in proximal arm strength on physical exam. CONCLUSIONS We highlight the diagnostic challenges in treating a patient with SLE with acute paralysis and sensory loss. In this case, aggressive early treatment of the patient's myelitis and myelopathy were successful in leading to mild neurological improvement.
BACKGROUND Isolated spinal artery subarachnoid hemorrhage is a rare occurrence in the general population, but occurs more commonly as one of many neurologic sequela of systemic lupus erythematosus (SLE). The etiology of a neurologic deficit in an SLE patient is often multifactorial. Comorbid conditions, such as antiphospholipid antibody syndrome, predispose to stroke. Other diagnoses, including transverse myelitis, may also be attributed to local inflammation. CASE REPORT A 37-year-old woman with SLE and antiphospholipid antibody syndrome experienced severe back pain followed by sudden paralysis and sensory loss below the T2 level. She remained alert and oriented on examination, with neurologic exam positive for diminished strength in the arms and with total loss of sensation and strength in the legs. Diagnostic workup was limited due to a contrast allergy and severe lupus nephritis; however, initial imaging showed increased cervical-thoracic spinal cord signal and concern for acute blood in the subarachnoid space. No neurosurgical intervention occurred, and the patient was treated with high-dose steroids and plasmapheresis for a possible transverse myelitis and non-aneurysmal subarachnoid hemorrhage. The patient received further neurologic and rheumatologic workup and remained neurologically stable, with improvement in proximal arm strength on physical exam. CONCLUSIONS We highlight the diagnostic challenges in treating a patient with SLE with acute paralysis and sensory loss. In this case, aggressive early treatment of the patient's myelitis and myelopathy were successful in leading to mild neurological improvement.
Related Concept Videos
 01:20
Nursing Process for Patient and Caregiver Teaching III: Evaluation and Documentation
Nurses can use several methods to evaluate patient outcomes. For example, oral questions can assess cognitive learning,...
 01:26
Spinal Cord
 01:26
Tonsillitis II: Management
 01:54
The Spinal Cord
 01:29
Impression Management Techniques I: Managing Appearances
 01:10
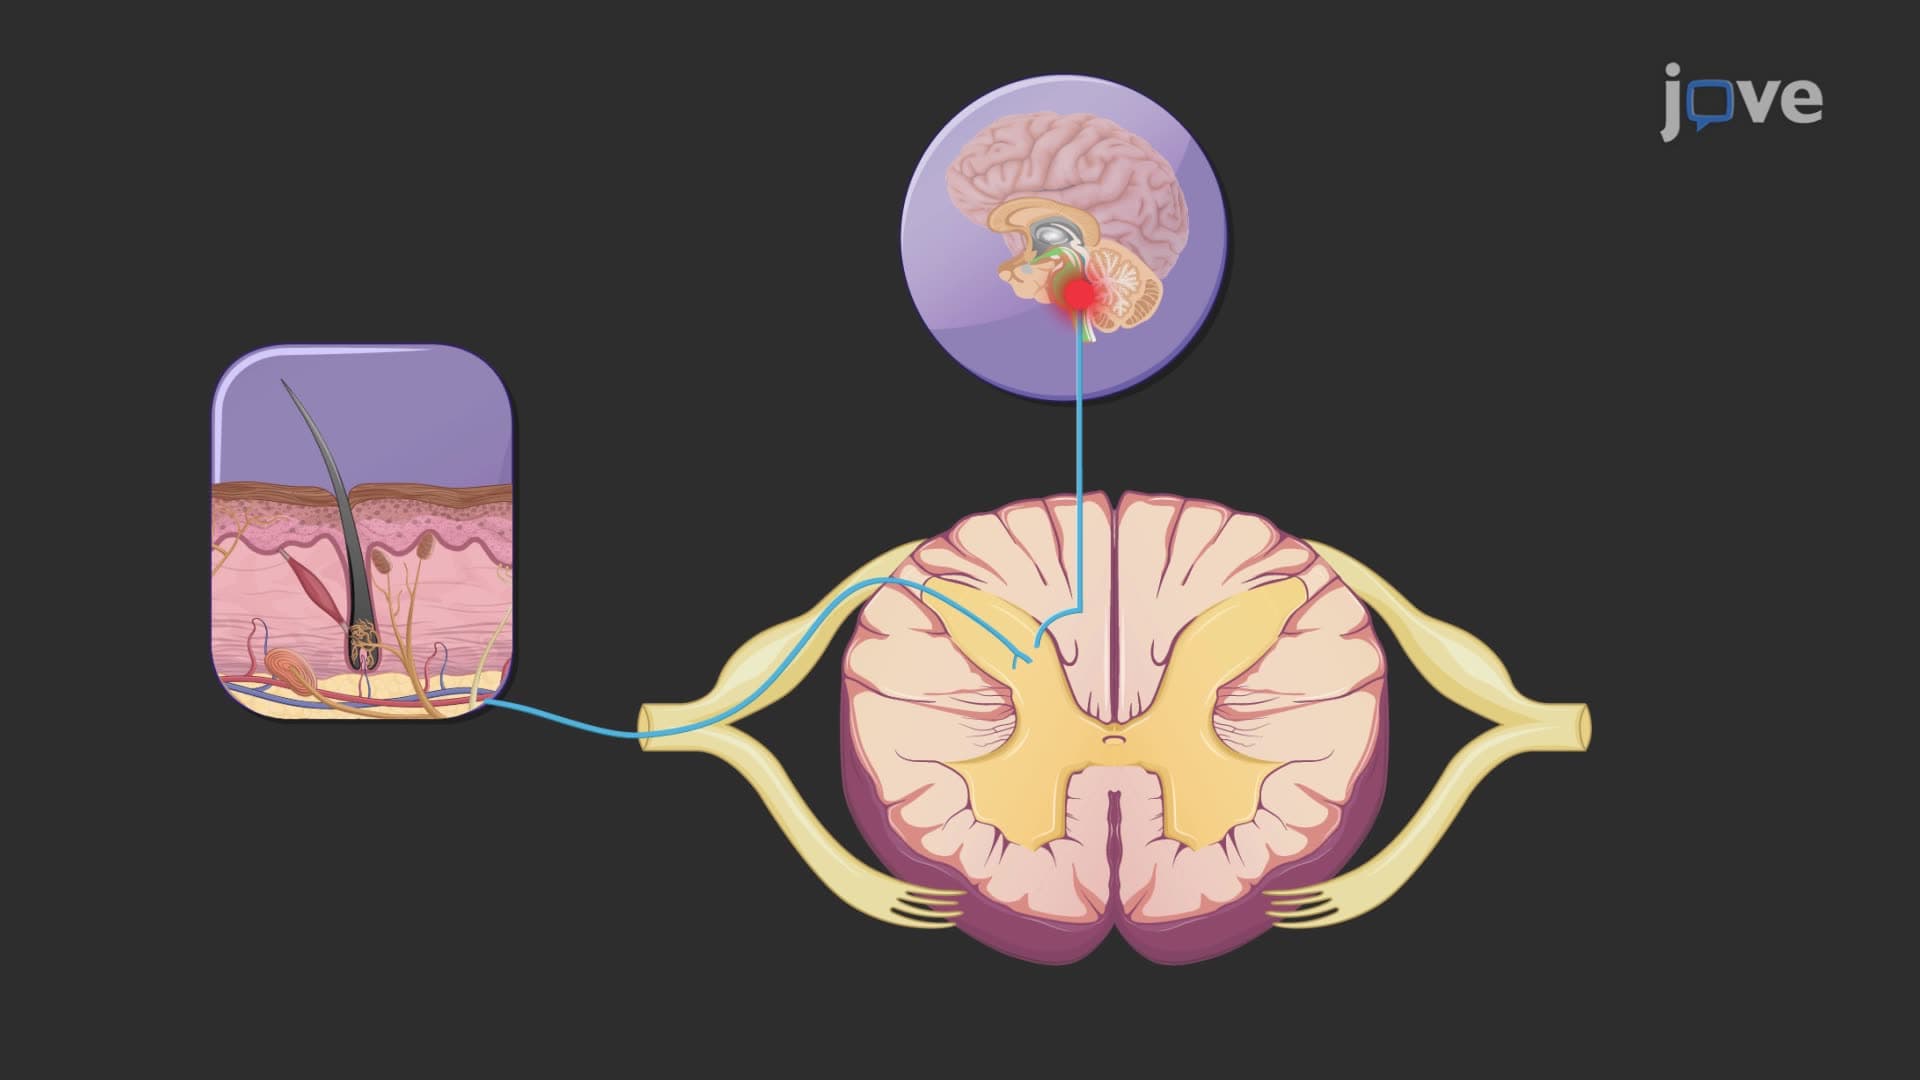
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...