Related Experiment Video
Updated: Feb 15, 2026


Isolation of Monocyte-Macrophage Lineage Cells from Rat Bones by Secondary Adherence Method
Published on: July 13, 2022
Hospital Variation in Adherence Rates to Secondary Prevention Medications and the Implications on Quality
Robin Mathews1, William Wang2, Lisa A Kaltenbach2
1Duke Clinical Research Institute, Durham, NC (R.M., W.W., L.A.K., L.T., E.D.P., T.Y.W.) robin.mathews@duke.edu.

Background:
Medication adherence is important to improve the long-term outcomes after acute myocardial infarction (MI). We hypothesized that there is significant variation among US hospitals in terms of medication adherence after MI, and that patients treated at hospitals with higher medication adherence after MI will have better long-term cardiovascular outcomes.
Methods:
We identified 19 704 Medicare patients discharged after acute MI from 347 US hospitals participating in the ACTION Registry-GWTG (Acute Coronary Treatment and Intervention Outcomes Network Registry-Get With the Guidelines) from January 2, 2007, to October 1, 2010. Using linked Medicare Part D prescription filling data, medication adherence was defined as proportion of days covered >80% within 90 days after discharge. Cox proportional hazards modeling was used to compare 2-year major adverse cardiovascular events among hospitals with high, moderate, and low 90-day medication adherence.
Results:
By 90 days after MI, overall rates of adherence to medications prescribed at discharge were 68% for β-blockers, 63% for statins, 64% for angiotensin-converting enzyme inhibitors/angiotensin receptor blockers, and 72% for thienopyridines. Adherence to these medications up to 90 days varied significantly among hospitals: β-blockers (proportion of days covered >80%; 59% to 75%), statins (55% to 69%), thienopyridines (64% to 77%), and angiotensin-converting enzyme inhibitors/angiotensin receptor blockers (57% to 69%). Compared with hospitals in the lowest quartile of 90-day composite medication adherence, hospitals with the highest adherence had lower unadjusted and adjusted 2-year major adverse cardiovascular event risk (27.5% versus 35.3%; adjusted hazard ratio, 0.88; 95% confidence interval, 0.80-0.96). High-adherence hospitals also had lower adjusted rates of death or readmission (hazard ratio, 0.90; 95% confidence interval, 0.85-0.96), whereas there was no difference in mortality after adjustment.
Conclusions:
Use of secondary prevention medications after discharge varies significantly among US hospitals and is inversely associated with 2-year outcomes. Hospitals may improve medication adherence after discharge and patient outcomes through better coordination of care between inpatient and outpatient settings.


Related Concept Videos
 00:59
Hospitals-II
Nurses that work in...
 01:28
Hospitals-I
 01:14
What is Variation?
The range, standard deviation, standard error, and variance are the different measures of variation.
Range: The range is the difference between its maximum and...
 01:19
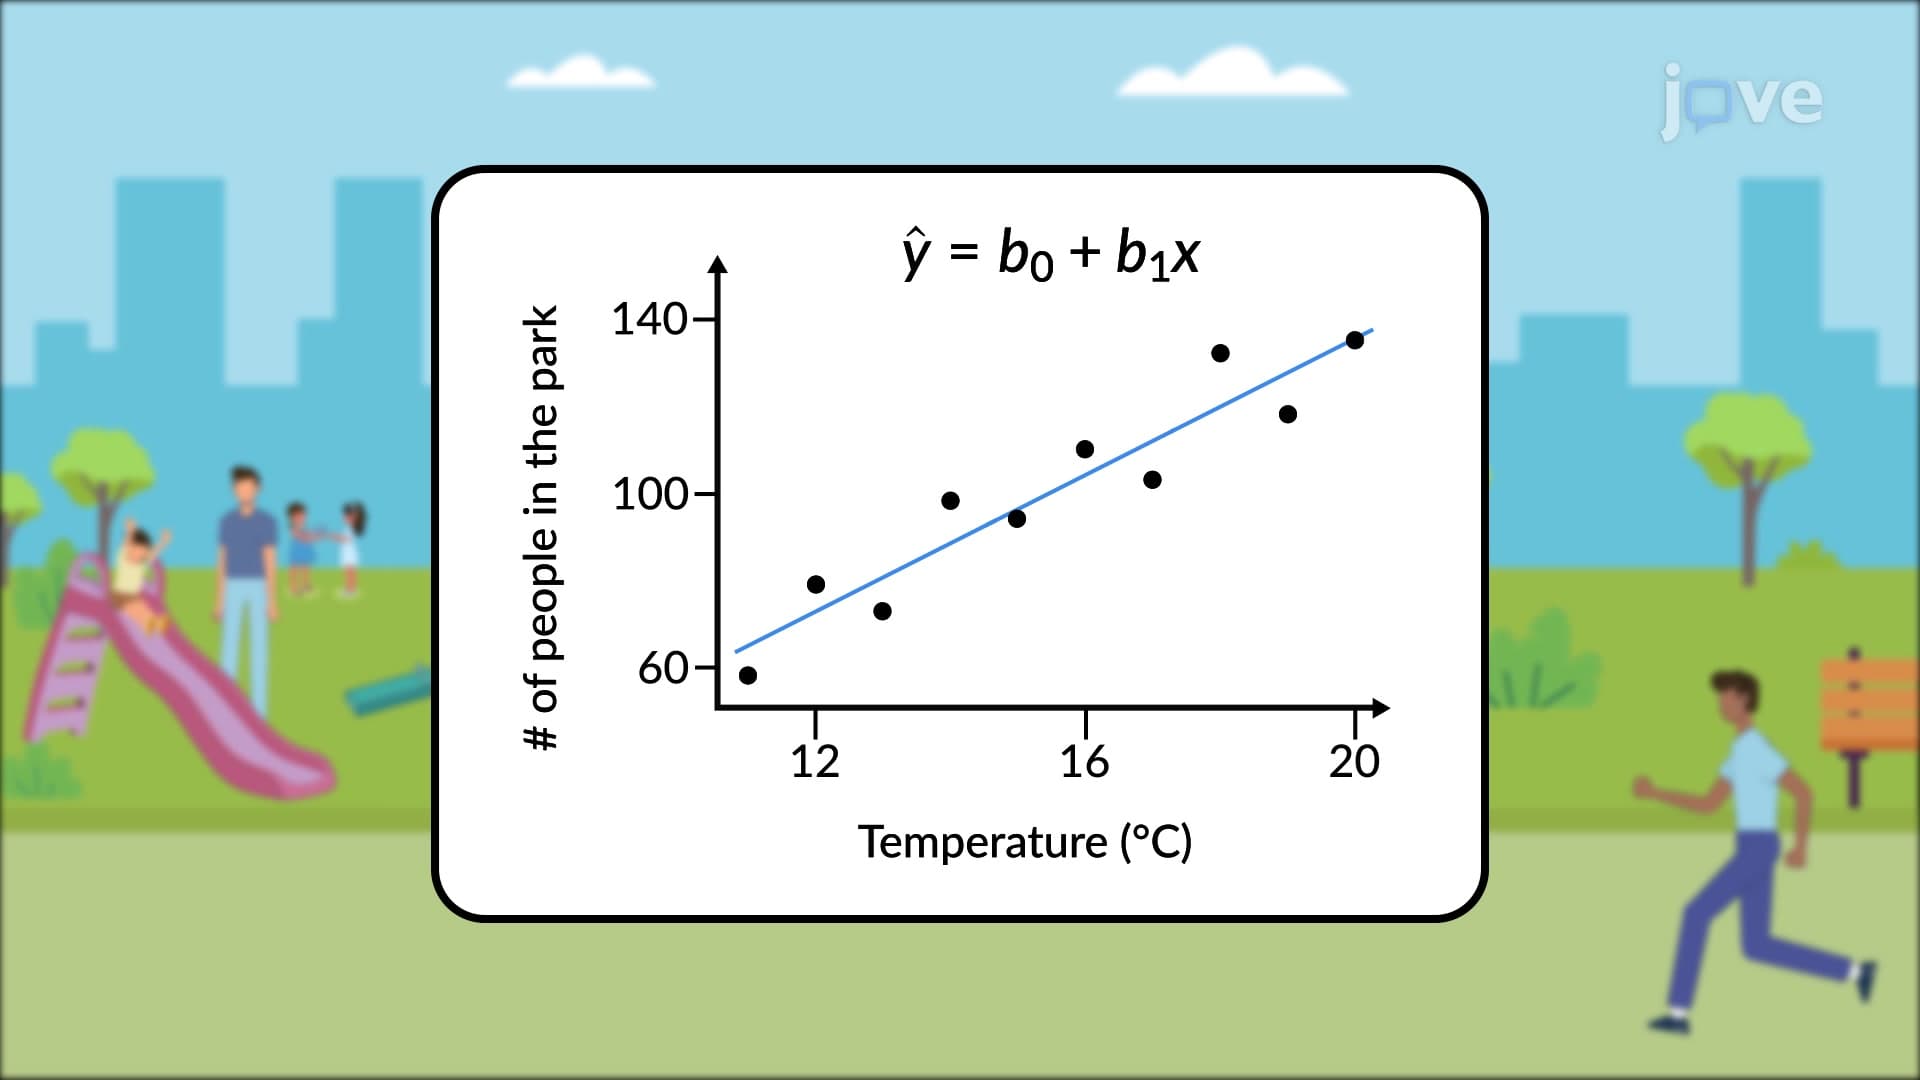
Variation
When independent and dependent variables are plotted on a scatter plot, the slope of a line is a value that describes the rate of change between the two...
 01:55
Secondary Active Transport
 02:53
Conservative Site-specific Recombination and Phase Variation
The recognition sites for Cre recombinase called LoxP...