Related Experiment Video
Updated: Feb 14, 2026
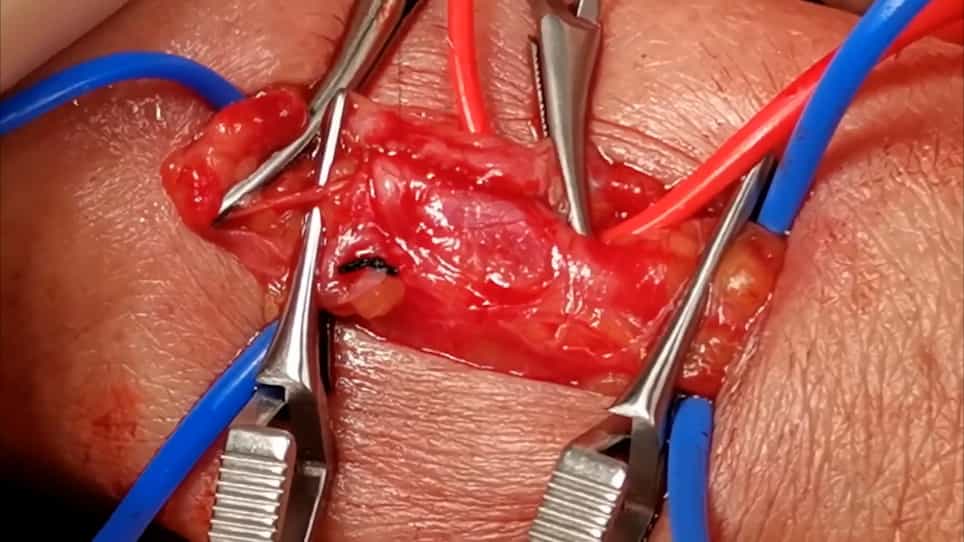
Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Surgical Treatment of Cephalic Arch Problems in Arteriovenous Fistulas: A Center Experience
Mónica Fructuoso1, Joana Ferreira2, Pedro Sousa3
1Nephrology Department, Centro Hospitalar de Trás os Montes e Alto Douro EPE, Vila Real, Portugal; Faculdade de Ciências da Saúde da Universidade da Beira Interior, Covilhã, Portugal.

Insights
Surgical cephalic vein transposition for arteriovenous fistula (AVF) complications reduced interventions and thrombosis. However, reintervention was still necessary, highlighting the need for individualized treatment plans for complex cephalic arch issues.
Area of Science:
- Vascular Surgery
- Nephrology
- Interventional Radiology
Background:
- Cephalic arch stenosis is a frequent cause of arteriovenous fistula (AVF) failure, often necessitating repeat interventions.
- Current treatment strategies for cephalic arch problems lack a definitive standard, leading to challenges in maintaining AVF patency.
Purpose of the Study:
- To evaluate the outcomes of surgical cephalic vein transposition for managing complex cephalic arch problems in AVFs.
- To assess the impact of surgical intervention on endovascular intervention rates, thrombosis, and fistula patency.
Main Methods:
- Retrospective analysis of seven patients undergoing cephalic vein transposition for AVF cephalic arch issues between 2013 and 2015.
- Outcomes measured included endovascular intervention rate, thrombosis rate, and primary/secondary patency rates.
Main Results:
- Surgical transposition significantly reduced endovascular interventions (1.9 to 0.4 per patient-year) and thrombosis rates (0.93 to 0.17 per patient-year).
- Primary and secondary patencies at 6 months were 57% and 71%, respectively, with reinterventions needed for anastomosis or vein stenosis.
- No surgical complications were reported; most patients utilized the AVF for dialysis post-procedure.
Conclusions:
- Surgical treatment for cephalic arch problems in AVFs can decrease intervention and thrombosis rates.
- Despite improvements, reinterventions remain necessary, underscoring the need for personalized treatment approaches for complex cephalic arch complications.
Background:
Cephalic arch problems, mainly stenosis, are a common cause of arteriovenous fistulas (AVFs) failure, and the most effective treatment is yet to be clearly defined. Restenosis usually occurs soon, and multiple interventions become necessary to maintain patency and functionality. The authors present the experience of their center with cephalic vein transposition in a group of patients with different problems involving the cephalic arch.
Methods:
After consultation of the medical records, an observational retrospective analysis was performed to evaluate the outcomes of surgical treatment in cephalic arch problems of AVFs treated at the author's center between January 2013 and December 2015. The considered outcomes were endovascular intervention rate, thrombosis rate, and primary and secondary patencies.
Results:
Seven patients were treated by venovenostomy with transposition of the cephalic arch and anastomosis to the axillary vein. The average patient age was 72 years (59-81), and most patients were female (71%) and diabetic (71%). All accesses were brachiocephalic AVFs with a mean duration of 4 years (1-7). The underlying problems were intrinsic cephalic arch stenosis (n = 5), entrapment of the cephalic vein (n = 1), and clinically significant vein tortuosity at the cephalic arch (n = 1). These last 2 problems conducted to a surgical approach as first-line therapy instead of endovascular intervention, the initial treatment in the other 5 cases (all with high-pressure balloons, with cutting balloon in one case). Previous thrombotic episodes were reported in 57% of the patients. The mean access flow before surgical intervention was 425 mL/min (350-1,500). No complications related with the surgical procedure were reported. One patient underwent surgical thrombectomy after AVF thrombosis, followed by transposition of the vein. In another case, a simultaneous flow reduction was performed. Most of the patients on dialysis (5/6) used the AVF after surgery. After a mean follow-up period of 9 months (1-22), surgical treatment was associated with a reduction in endovascular intervention rate (1.9 interventions per patient-year presurgery versus 0.4 postsurgery; P < 0.05) and thrombosis rate (0.93 thrombotic episodes per patient-year presurgery versus 0.17 postsurgery; P < 0.05). The problems leading to endovascular reintervention were as follows: new venous anastomosis stenosis (57%), axillary vein stenosis (29%), and swing-point stenosis (14%). Primary and secondary patencies at 6 months were 57% and 71%, respectively.
Conclusions:
In this group of patients with cephalic arch problems and multiple previous procedures, surgical treatment was associated with a reduction in endovascular intervention and thrombosis rate but did not avoid reintervention. Facing the complexity and multiplicity of the cephalic arch complications, treatment should be individually decided.

Related Concept Videos
 01:10
The Arch of Aorta
Encircling the heart, the coronary arteries form a ring-like structure before...
 01:24
Cephalic Phase of Digestion
 02:33
Lattice Centering and Coordination Number
Types of Unit Cells
Imagine taking a large number of identical...
 00:58
Center of Gravity
 01:15
Center of Gravity
To determine its location, the principle of moments can be utilized by dividing the object into...
 00:59
Center of Mass
The knowledge of the center of mass can also help us to describe and predict the motion of objects. For example, when a ball is thrown...