Related Experiment Video
Updated: Feb 14, 2026

Author Spotlight: Exploring the Role of Unfolded Protein Response in HIV-1 Replication and Infectivity
Published on: June 14, 2024
The B-Cell Follicle in HIV Infection: Barrier to a Cure
Matthew P Bronnimann1, Pamela J Skinner2, Elizabeth Connick1
1Division of Infectious Disease, Department of Medicine, University of Arizona, Tucson, AZ, United States.

Abstract:
The majority of HIV replication occurs in secondary lymphoid organs (SLOs) such as the spleen, lymph nodes, and gut-associated lymphoid tissue. Within SLOs, HIV RNA+ cells are concentrated in the B-cell follicle during chronic untreated infection, and emerging data suggest that they are a major source of replication in treated disease as well. The concentration of HIV RNA+ cells in the B-cell follicle is mediated by several factors. Follicular CD4+ T-cell subsets including T-follicular helper cells and T-follicular regulatory cells are significantly more permissive to HIV than extrafollicular subsets. The B cell follicle also contains a large reservoir of extracellular HIV virions, which accumulate on the surface of follicular dendritic cells (FDCs) in germinal centers. FDC-bound HIV virions remain infectious even in the presence of neutralizing antibodies and can persist for months or even years. Moreover, the B-cell follicle is semi-immune privileged from CTL control. Frequencies of HIV- and SIV-specific CTL are lower in B-cell follicles compared to extrafollicular regions as the majority of CTL do not express the follicular homing receptor CXCR5. Additionally, CTL in the B-cell follicle may be less functional than extrafollicular CTL as many exhibit the recently described CD8 T follicular regulatory phenotype. Other factors may also contribute to the follicular concentration of HIV RNA+ cells. Notably, the contribution of NK cells and γδ T cells to control and/or persistence of HIV RNA+ cells in secondary lymphoid tissue remains poorly characterized. As HIV research moves increasingly toward the development of cure strategies, a greater understanding of the barriers to control of HIV infection in B-cell follicles is critical. Although no strategy has as of yet proven to be effective, a range of novel therapies to address these barriers are currently being investigated including genetically engineered CTL or chimeric antigen receptor T cells that express the follicular homing molecule CXCR5, treatment with IL-15 or an IL-15 superagonist, use of bispecific antibodies to harness the killing power of the follicular CD8+ T cell population, and disruption of the follicle through treatments such as rituximab.


Related Concept Videos
 01:20
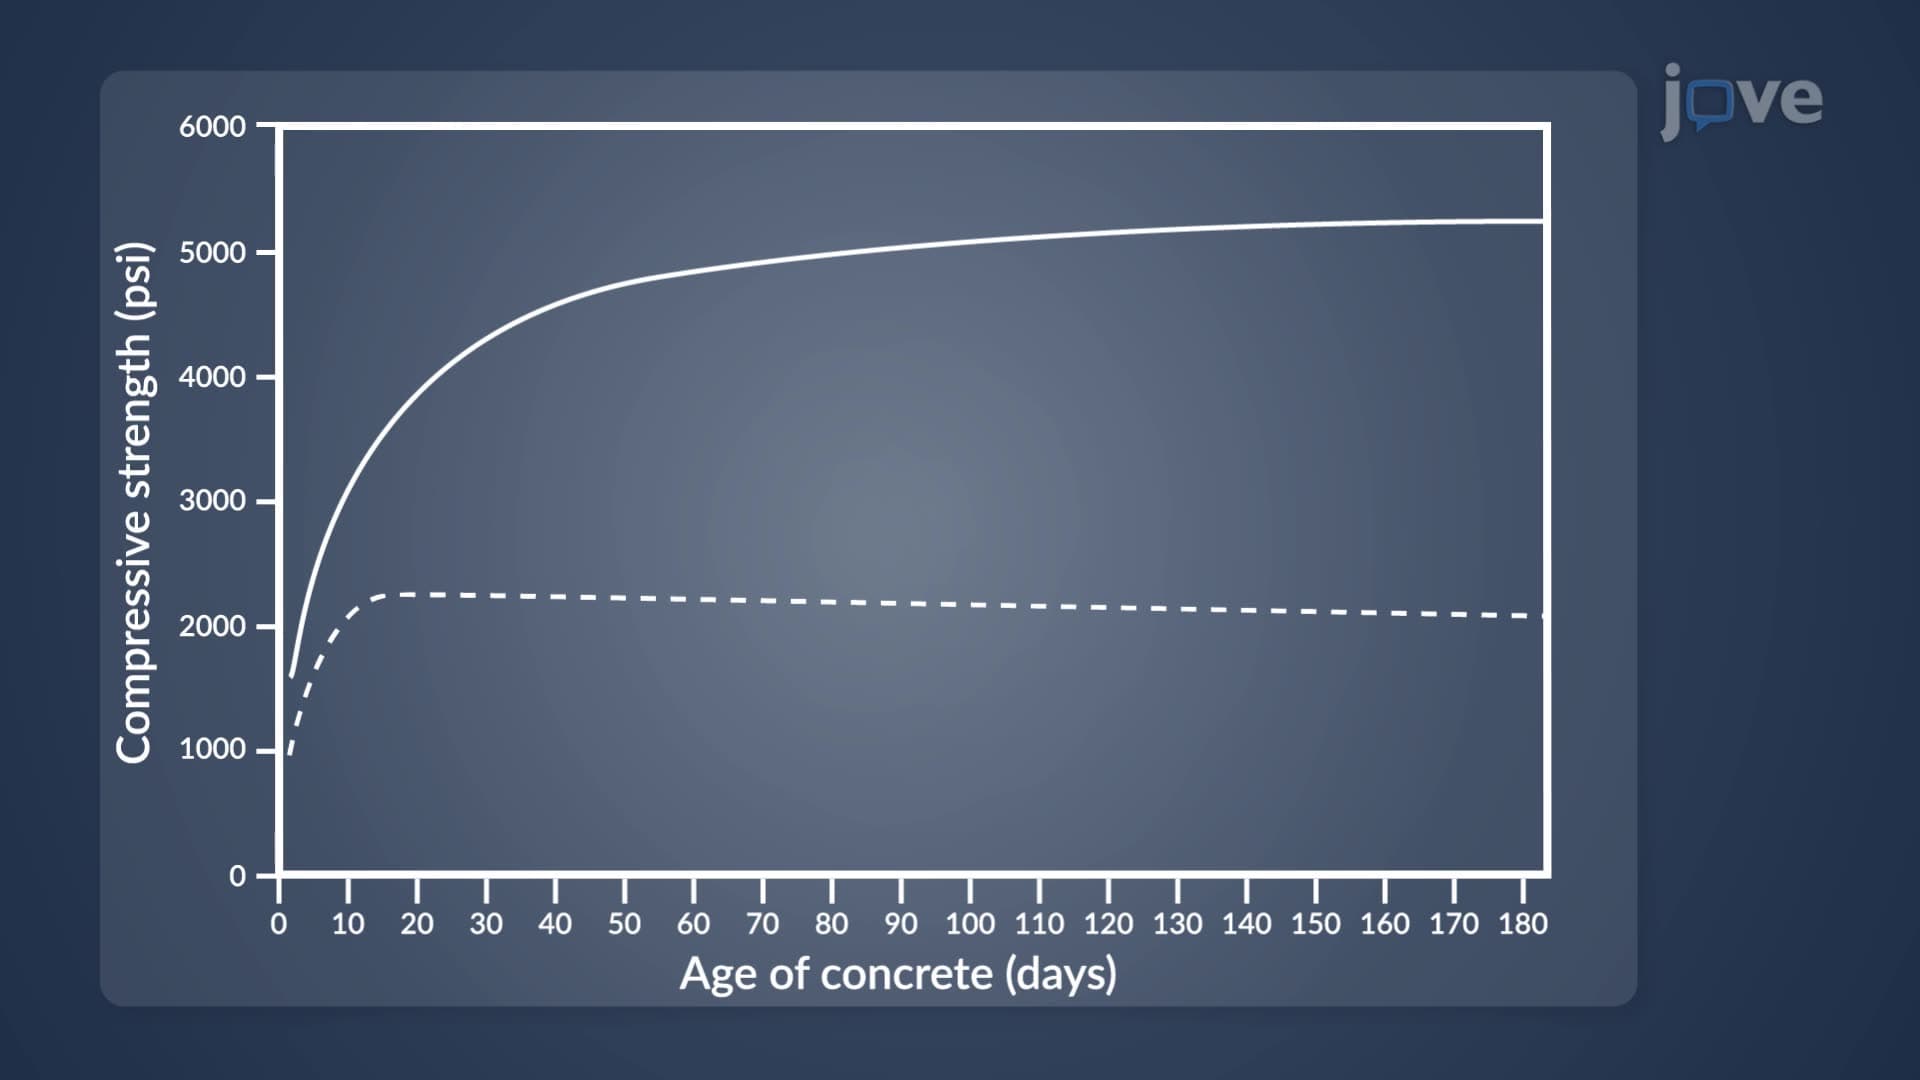
Curing of Concrete
 01:26
Curing Methods
 01:25
Accelerated Curing of Concrete
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:25
Mucosal Barrier of the Stomach
Within parietal cells, carbonic acid is first formed through the reaction of water and carbon dioxide. The dissociation of carbonic acid releases bicarbonate and hydrogen ions. The bicarbonate...
 01:21
Barriers to Effective Communication II
Cultural barriers:
Differences in values, beliefs, religion, knowledge, and tradition can significantly impact communication. Awareness of nonverbal cues is critical, especially when conversing with a patient from a different culture. What appears appropriate in one culture may be inappropriate in another.
Semantic barriers:
As a result of their tendency to use...