Related Experiment Video
Updated: Feb 14, 2026
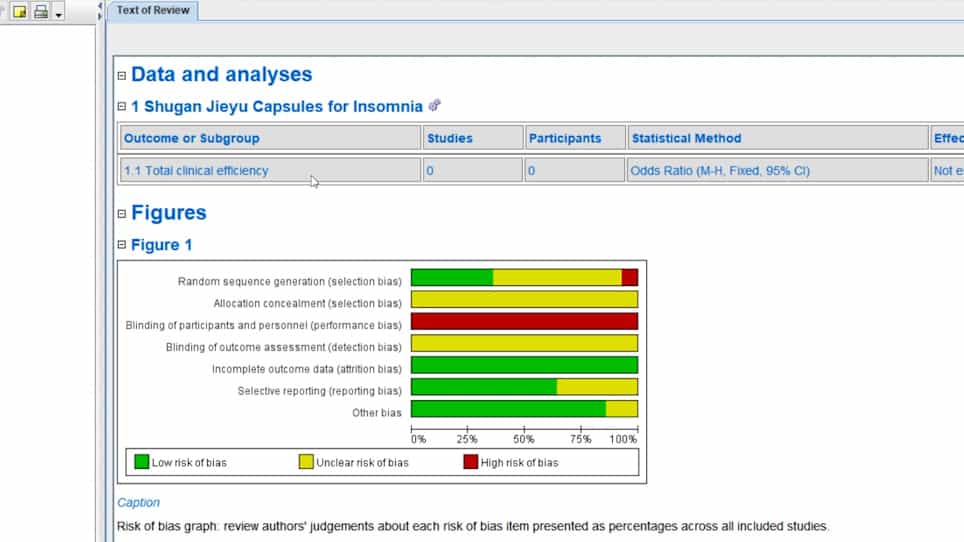
Meta-Analysis of the Effectiveness and Safety of Shugan Jieyu Capsules for the Treatment of Insomnia
Published on: February 17, 2023
Rapid intravenous rehydration of children with acute gastroenteritis and dehydration: a systematic review and
1Oxford Vaccine Group, Department of Paediatrics and the NIHR Biomedical Research Centre, University of Oxford, Headington, Oxford, OX3 7LE, UK.

Insights
Rapid intravenous rehydration for children with acute gastroenteritis is not proven to be more effective or safer than slower methods. Further research is needed to optimize fluid therapy guidelines for severe dehydration.
Area of Science:
- Pediatric Emergency Medicine
- Critical Care
- Infectious Diseases
Background:
- The World Health Organization (WHO) recommends rapid intravenous rehydration for children with acute gastroenteritis (AGE) and severe dehydration.
- Current guidelines suggest fluid volumes of 70-100mls/kg over 3-6 hours, including initial fluid boluses for hypovolemic shock.
- However, evidence supporting the safety and efficacy of rapid versus slower rehydration remains uncertain.
Purpose of the Study:
- To systematically review randomized controlled trials (RCTs) comparing different rates of intravenous fluid therapy in children with AGE and moderate or severe dehydration.
- To assess the safety and efficacy of rapid versus slower intravenous rehydration strategies.
Main Methods:
- A systematic review of RCTs was conducted using standard search terms.
- Two authors independently assessed trial quality and extracted data, excluding non-RCTs and non-English articles.
- Primary endpoint was mortality; secondary endpoints included adverse events and treatment efficacy.
Main Results:
- Three studies (n=464) met inclusion criteria, primarily involving children with moderate dehydration and not conducted in resource-poor settings.
- Fluid volumes ranged from 20-60 ml/kg over 1-2 hours (fast) versus 2-4 hours (slow), with substantial methodological heterogeneity.
- No deaths were reported. Adverse events included edema (n=6) and dysnatremia (n=2). Pooled analysis showed no significant difference in treatment failures or readmission rates between rapid and slow rehydration groups.
Conclusions:
- Limited clinical evaluation exists for intravenous rehydration rates in resource-limited settings for severe AGE.
- Current evidence does not definitively support rapid intravenous rehydration over slower methods for children with AGE and severe dehydration.
- Further research is warranted to inform optimal guidelines for intravenous rehydration rates in severe AGE, especially given concerns about aggressive fluid expansion.
Background:
The World Health Organization (WHO) recommends rapid intravenous rehydration, using fluid volumes of 70-100mls/kg over 3-6 h, with some of the initial volume given rapidly as initial fluid boluses to treat hypovolaemic shock for children with acute gastroenteritis (AGE) and severe dehydration. The evidence supporting the safety and efficacy of rapid versus slower rehydration remains uncertain.
Methods:
We conducted a systematic review of randomised controlled trials (RCTs) on 11th of May 2017 comparing different rates of intravenous fluid therapy in children with AGE and moderate or severe dehydration, using standard search terms. Two authors independently assessed trial quality and extracted data. Non-RCTs and non-English articles were excluded. The primary endpoint was mortality and secondary endpoints included adverse events (safety) and treatment efficacy.
Main Results:
Of the 1390 studies initially identified, 18 were assessed for eligibility. Of these, 3 studies (n = 464) fulfilled a priori criteria for inclusion; most studied children with moderate dehydration and none were conducted in resource-poor settings. Volumes and rates of fluid replacement varied from 20 to 60 ml/kg given over 1-2 h (fast) versus 2-4 h (slow). There was substantial heterogeneity in methodology between the studies with only one adjudicated to be of high quality. There were no deaths in any study. Safety endpoints only identified oedema (n = 6) and dysnatraemia (n = 2). Pooled analysis showed no significant difference between the rapid and slow intravenous rehydration groups for the proportion of treatment failures (N = 468): pooled RR 1.30 (95% CI: 0.87, 1.93) and the readmission rates (N = 439): pooled RR 1.39 (95% CI: 0.68, 2.85).
Conclusions:
Despite wide implementation of WHO Plan C guideline for severe AGE, we found no clinical evaluation in resource-limited settings, and only limited evaluation of the rate and volume of rehydration in other parts of the world. Recent concerns over aggressive fluid expansion warrants further research to inform guidelines on rates of intravenous rehydration therapy for severe AGE.
Related Concept Videos
 01:15
Dehydration Synthesis
Dehydration synthesis (also called a condensation reaction) is the chemical process in which two molecules covalently link together to form a new molecule, along with the release of a water molecule. Many physiologically important compounds form by dehydration synthesis reactions, such as complex carbohydrates, proteins, DNA, and RNA.
Synthesis of carbohydrates
Sugar molecules are covalently linked together by dehydration synthesis. During the reaction, the hydroxyl (-OH) group from...
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 02:35
Acid-Catalyzed Dehydration of Alcohols to Alkenes
 01:20
Random and Systematic Errors
 01:09
Directing Effect of Substituents: meta-Directing Groups