Related Experiment Video
Updated: Feb 14, 2026


Esophageal Heat Transfer for Patient Temperature Control and Targeted Temperature Management
Published on: November 21, 2017
Esophagitis associated with multimodality management of pediatric Ewing sarcoma of thorax
Vibhuti Agarwal1, Natalie Logie2, Christopher G Morris2
1Division of Hematology/Oncology, Nemours Children's Specialty Care, Jacksonville, Florida.

Background:
Ewing sarcoma of the thoracic spine and chest wall is frequently treated with concurrent chemotherapy and radiation therapy (RT). Treatment-related acute esophagitis can lead to hospitalization and treatment delays. The aim of this study was to analyze the incidence, risk factors, and management of esophagitis in pediatric patients with Ewing sarcoma of the thoracic region.
Methods:
We conducted a single-institution retrospective review of patients treated over a 10-year period. Medical records were reviewed for patient and treatment characteristics associated with Common Terminology Criteria for Adverse Events grade 2 or higher esophagitis. RT plans were also reviewed and various esophageal dose metrics were analyzed.
Results:
Twelve of 37 patients (32%) developed acute esophagitis. Neutropenia was associated with an increased risk of esophagitis (60% vs. 14%; P < 0.01). RT significantly contributed to its incidence when maximum esophageal dose was >47 Gy (69% vs. 5%; P < 0.0001) and esophageal D5cm3 was >15 Gy (67% vs. 9%; P < 0.001). All 12 patients with esophagitis were managed with oral opioid analgesics. Nine patients with persistent symptoms received subsequent fluconazole for empiric fungal treatment and each had a decreased need for opioid analgesics within 2-5 days.
Conclusion:
Approximately one-third of patients with Ewing sarcoma of the thoracic region will develop acute esophagitis. An esophageal D5cm3 dose < 15 Gy and maximal esophageal dose < 47 Gy may keep the rate of acute esophagitis under 5%. However, the association with neutropenia and consistent response to antifungal therapy suggest chemotherapy-associated toxicity and an infectious component as part of the process.
More Related Videos
Related Concept Videos
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:25
Muscles of the Thorax
The diaphragm is at the core of thoracic musculature, the primary muscle involved in breathing. This expansive, dome-shaped muscle marks the division between the thoracic and abdominal cavities. It...
 01:19
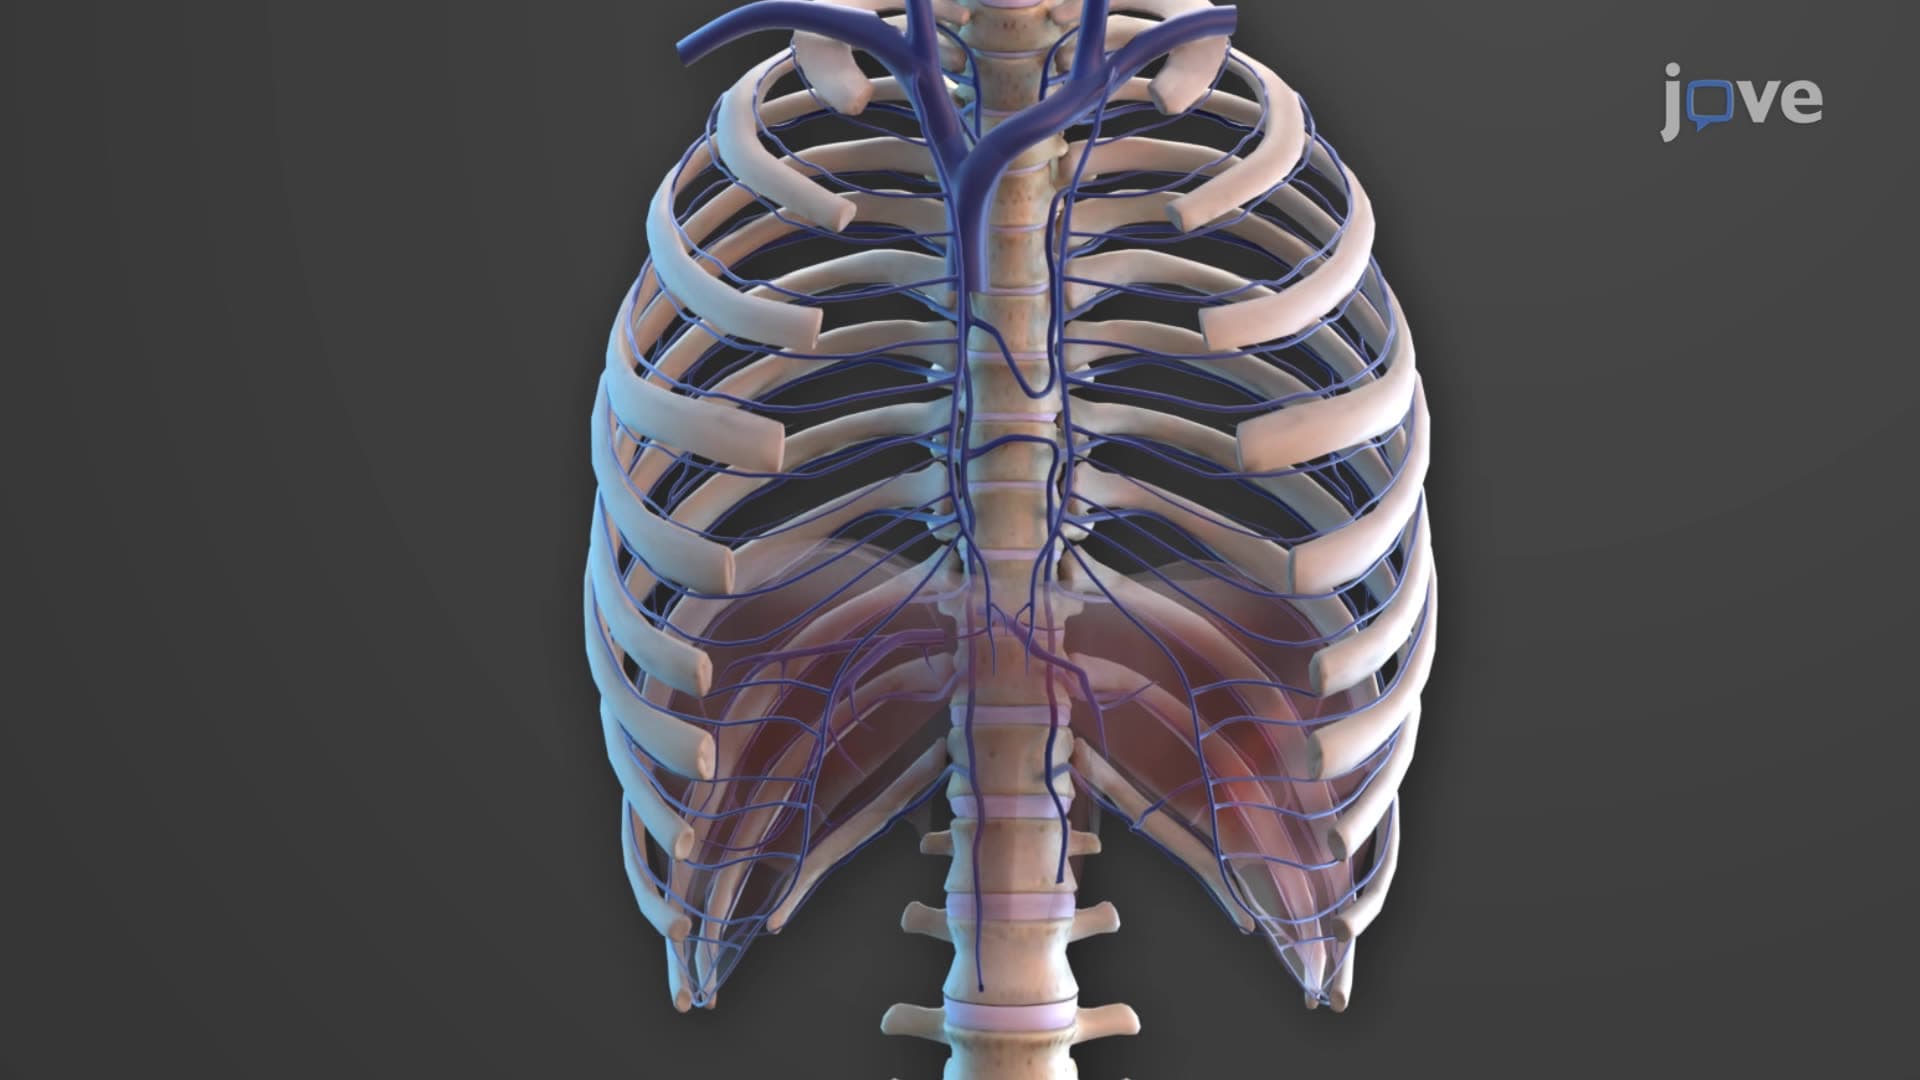
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:24
Esophageal Varices-I: Introduction