Related Experiment Video
Updated: Feb 14, 2026
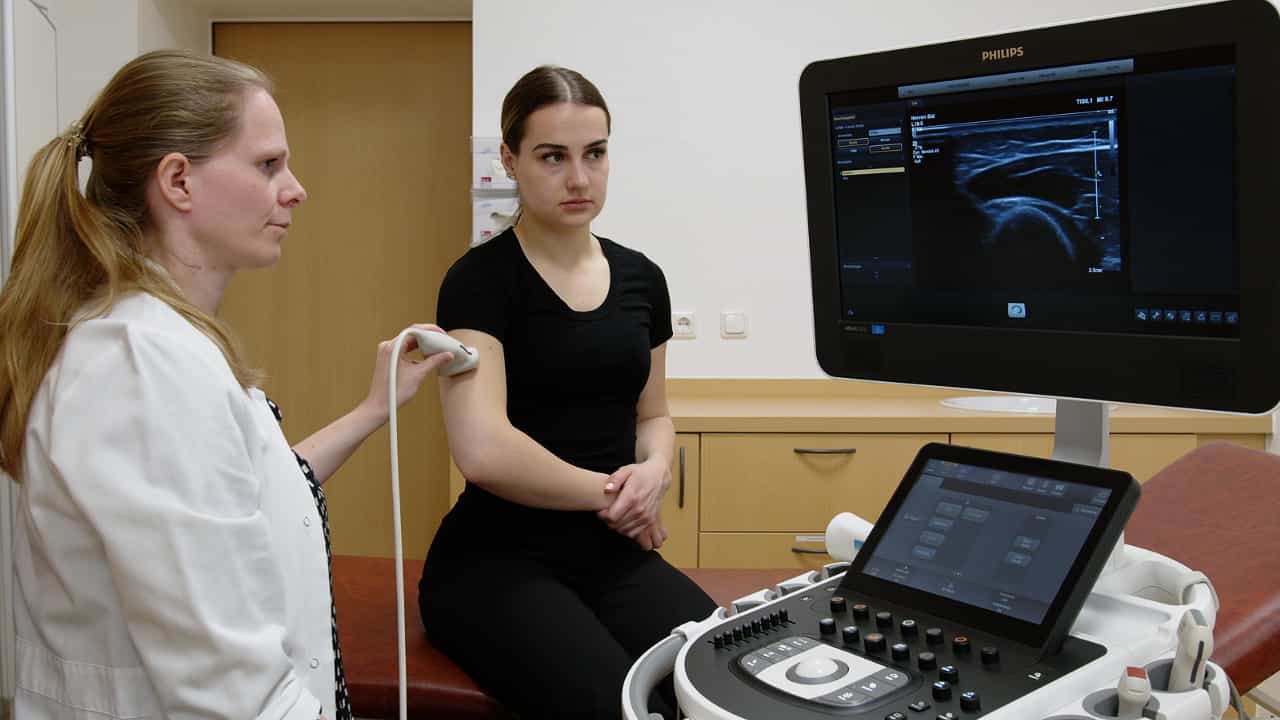
Nerve Ultrasound Protocol to Detect Dysimmune Neuropathies
Published on: October 7, 2021
Nerve Ultrasound Predicts Treatment Response in Chronic Inflammatory Demyelinating Polyradiculoneuropathy-a
Florian Härtig1,2, Marlene Ross1, Nele Maria Dammeier1,2
1Department of Neurology, Tübingen University Hospital, University of Tübingen, Hoppe-Seyler-Str. 3, 72076, Tubingen, Germany.

Abstract:
As reliable biomarkers of disease activity are lacking, monitoring of therapeutic response in chronic inflammatory demyelinating polyradiculoneuropathy (CIDP) remains a challenge. We sought to determine whether nerve ultrasound and electrophysiology scoring could close this gap. In CIDP patients (fulfilling EFNS/PNS criteria), we performed high-resolution nerve ultrasound to determine ultrasound pattern sum scores (UPSS) and predominant echotexture nerve conduction study scores (NCSS) as well as Medical Research Council sum scores (MRCSS) and inflammatory neuropathy cause and treatment disability scores (INCAT) at baseline and after 12 months of standard treatment. We retrospectively correlated ultrasound morphology with nerve histology when available. 72/80 CIDP patients featured multifocal nerve enlargement, and 35/80 were therapy-naïve. At baseline, clinical scores correlated with NCSS (r2 = 0.397 and r2 = 0.443, p < 0.01), but not or hardly with UPSS (Medical Research Council sum scores MRCSS r2 = 0.013, p = 0.332; inflammatory neuropathy cause and treatment disability scores INCAT r2 = 0.053, p = 0.048). Longitudinal changes in clinical scores, however, correlated significantly with changes in both UPSS and NCSS (r2 = 0.272-0.414, p < 0.0001). Combining nerve/fascicle size with echointensity and histology at baseline, we noted 3 distinct classes: 1) hypoechoic enlargement, reflecting active inflammation and onion bulbs; 2) nerve enlargement with additional hyperechogenic fascicles/perifascicular tissue in > 50% of measured segments, possibly reflecting axonal degeneration; and 3) almost no enlargement, reflecting "burned-out" or "cured" disease without active inflammation. Clinical improvement after 12 months was best in patients with pattern 1 (up to 75% vs up to 43% in pattern 2/3, Fisher's exact test p < 0.05). Nerve ultrasound has additional value not only for diagnosis, but also for classification of disease state and may predict treatment response.
More Related Videos
 06:43
Increased Recovery Time and Decreased LPS Administration to Study the Vagus Nerve Stimulation Mechanisms in Limited Inflammatory Responses
Published on: March 29, 2017
 02:41
Author Spotlight: Enhancing Women's Chronic Pelvic Pain Management Through Acupoint Catgut Embedding
Published on: May 3, 2024
Related Concept Videos
 01:28
Inflammatory Response
Inflammation can be triggered by various stimuli, such as impact, abrasion, chemical irritation, infections, and extreme hot or cold temperatures. These can damage cells and connective tissue fibers,...
 01:24
Inflammatory Response II: Inflammatory Exudate and Tissue Repair
The typical wound exudate is odorless, transparent, straw-colored, thin, and watery. Exudate, however, can differ depending on the state of wound healing. Likewise, the...
 01:30
Inflammatory Response I: Vascular and Cellular
 02:27
Predicting Molecular Geometry
 01:03
Prediction Intervals
However, the point estimate is most likely not the exact value of the population parameter, but close to it. After calculating point estimates, we construct interval estimates, called confidence intervals or prediction intervals. This prediction interval comprises a range of values unlike the point estimate and is a better predictor of the observed sample value, y.
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):