Capacity of non-invasive hepatic fibrosis algorithms to replace transient elastography to exclude cirrhosis in people with hepatitis C virus infection: A multi-centre observational study
Related Experiment Video
Updated: Feb 14, 2026
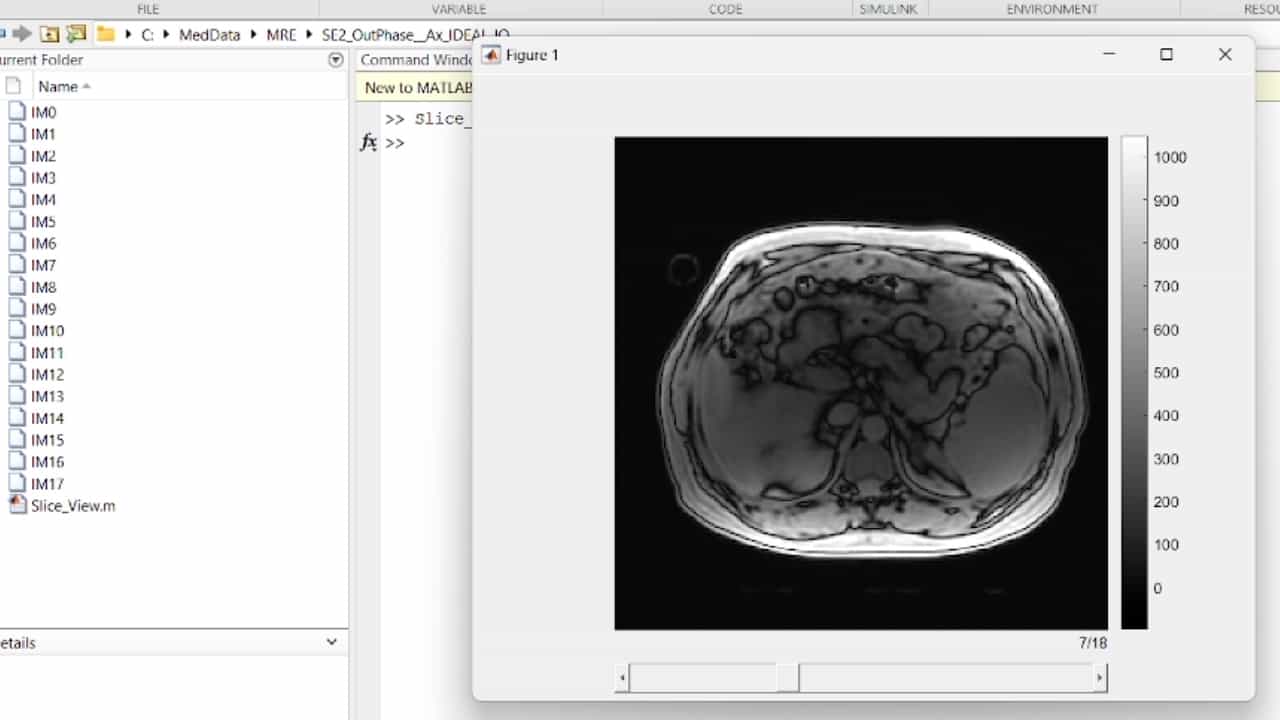
Author Spotlight: Advancing Hepatic Fibrosis Diagnosis Using Magnetic Resonance Elastography and AI
Published on: July 21, 2023
Melissa Louise Kelly1,2,3, Stephen M Riordan4,5, Rohan Bopage2
1Department of Infectious Diseases, Prince of Wales Hospital, Randwick, NSW, Australia.

Introduction:
Achievement of the 2030 World Health Organisation (WHO) global hepatitis C virus (HCV) elimination targets will be underpinned by scale-up of testing and use of direct-acting antiviral treatments. In Australia, despite publically-funded testing and treatment, less than 15% of patients were treated in the first year of treatment access, highlighting the need for greater efficiency of health service delivery. To this end, non-invasive fibrosis algorithms were examined to reduce reliance on transient elastography (TE) which is currently utilised for the assessment of cirrhosis in most Australian clinical settings.
Materials And Methods:
This retrospective and prospective study, with derivation and validation cohorts, examined consecutive patients in a tertiary referral centre, a sexual health clinic, and a prison-based hepatitis program. The negative predictive value (NPV) of seven non-invasive algorithms were measured using published and newly derived cut-offs. The number of TEs avoided for each algorithm, or combination of algorithms, was determined.
Results:
The 850 patients included 780 (92%) with HCV mono-infection, and 70 (8%) co-infected with HIV or hepatitis B. The mono-infected cohort included 612 men (79%), with an overall prevalence of cirrhosis of 16% (125/780). An 'APRI' algorithm cut-off of 1.0 had a 94% NPV (95%CI: 91-96%). Newly derived cut-offs of 'APRI' (0.49), 'FIB-4' (0.93) and 'GUCI' (0.5) algorithms each had NPVs of 99% (95%CI: 97-100%), allowing avoidance of TE in 40% (315/780), 40% (310/780) and 40% (298/749) respectively. When used in combination, NPV was retained and TE avoidance reached 54% (405/749), regardless of gender or co-infection.
Conclusions:
Non-invasive algorithms can reliably exclude cirrhosis in many patients, allowing improved efficiency of HCV assessment services in Australia and worldwide.
More Related Videos

Related Concept Videos
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:21
Hepatic Portal System
At its core, the hepatic portal vein is the result of a confluence of the superior and inferior mesenteric veins along with the splenic vein. Each of these veins has a unique role. The superior mesenteric vein is...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:16
Hepatic Drug Excretion: Influencing Factors
 01:14
Hepatic Drug Clearance: Role of Transporters
 01:47
Lung Capacity