Related Experiment Video
Updated: Feb 14, 2026
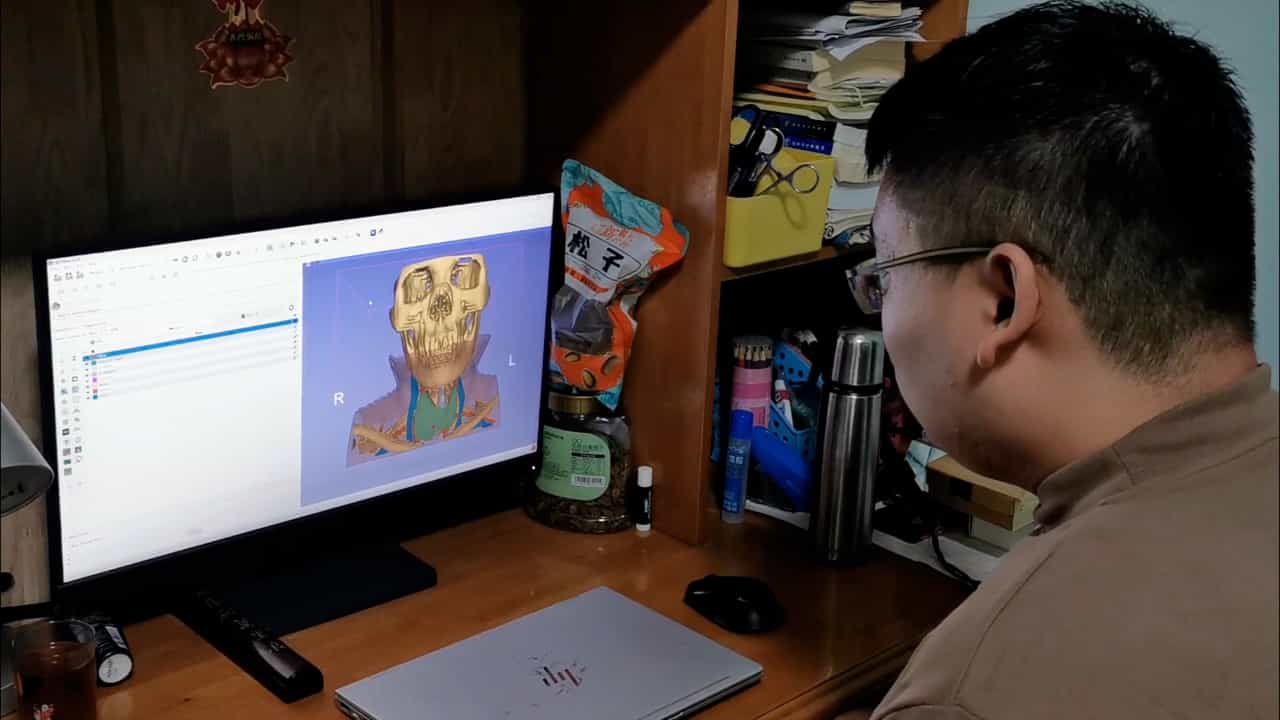
Mixed Reality Assisted Radical Endoscopic Thyroidectomy
Published on: January 31, 2025
A clinical pathway for the postoperative management of hypocalcemia after pediatric thyroidectomy reduces blood draws
Neha A Patel1, Randall A Bly2, Seth Adams3
1Cohen Children's Medical Center, Division of Pediatric Otolaryngology, New Hyde Park, NY, USA; Hofstra Northwell School of Medicine, Department of Otolaryngology-Head and Neck Surgery, Hempstead, NY, USA; Seattle Children's Hospital, Division of Pediatric Otolaryngology-Head and Neck Surgery, Seattle, WA, USA; University of Washington, Department of Otolaryngology-Head and Neck Surgery, Seattle, WA, USA.

Insights
A new protocol using intraoperative parathyroid hormone (PTH) levels significantly reduced daily calcium blood draws in pediatric thyroidectomy patients. Hospital length of stay remained unchanged, but the protocol simplifies postoperative electrolyte management.
Area of Science:
- Pediatric Endocrinology
- Surgical Patient Management
- Clinical Protocol Development
Background:
- Postoperative calcium management in pediatric thyroidectomy patients presents challenges due to difficulties in self-reporting symptoms and adhering to blood draw schedules.
- Standardized protocols are needed to optimize electrolyte monitoring and patient care following pediatric thyroidectomy.
Purpose of the Study:
- To evaluate the impact of a novel postoperative management protocol on calcium blood draws and hospital length of stay in pediatric thyroidectomy patients.
- To assess the effectiveness of utilizing intraoperative parathyroid hormone (PTH) levels for guiding postoperative electrolyte management.
Main Methods:
- A retrospective study analyzed data from pediatric total thyroidectomy and completion thyroidectomy cases between 2010 and 2016 at a tertiary children's institution.
- Patients were divided into pre-protocol (control) and post-protocol (experimental) groups, with the latter implementing a new management strategy based on intraoperative PTH levels.
- Multivariable regression models were used to compare the number of calcium blood draws and length of hospital stay between the two groups.
Main Results:
- The study included 53 pediatric patients (23 control, 30 experimental).
- Post-protocol implementation, the mean number of daily postoperative calcium draws decreased significantly from 5.2 to 3.6 (Rate Ratio = 0.70, p < .001).
- While the overall length of stay did not significantly change (2.1 days control vs. 1.8 days experimental, p = .29), concurrent neck dissection and hypocalcemia were associated with longer hospital stays.
Conclusions:
- A standardized postoperative protocol guided by intraoperative parathyroid hormone (PTH) levels effectively reduced the frequency of calcium blood draws in pediatric thyroidectomy patients.
- The implemented protocol did not alter the overall length of hospital stay but offers a structured approach to postoperative electrolyte management.
- This protocol may improve efficiency and reduce patient burden by minimizing unnecessary blood draws following pediatric thyroidectomy.
Objectives:
Postoperative calcium management is challenging following pediatric thyroidectomy given potential limitations in self-reporting symptoms and compliance with phlebotomy. A protocol was created at our tertiary children's institution utilizing intraoperative parathyroid hormone (PTH) levels to guide electrolyte management during hospitalization. The objective of this study was to determine the effect of a new thyroidectomy postoperative management protocol on two primary outcomes: (1) the number of postoperative calcium blood draws and (2) the length of hospital stay.
Study Design:
Institutional review board approved retrospective study (2010-2016).
Methods:
Consecutive pediatric total thyroidectomy and completion thyroidectomy ± neck dissection cases from 1/1/2010 through 8/5/2016 at a single tertiary children's institution were retrospectively reviewed before and after initiation of a new management protocol. All cases after 2/1/2014 comprised the experimental group (post-protocol implementation). The pre-protocol control group consisted of cases prior to 2/1/2014. Multivariable linear and Poisson regression models were used to compare the control and experimental groups for outcome measure of number of calcium lab draws and hospital length of stay.
Results:
53 patients were included (n = 23, control group; n = 30 experimental group). The median age was 15 years. 41 patients (77.4%) were female. Postoperative calcium draws decreased from a mean of 5.2 to 3.6 per day post-protocol implementation (Rate Ratio = 0.70, p < .001), adjusting for covariates. The mean number of total inpatient calcium draws before protocol initiation was 13.3 (±13.20) compared to 7.2 (±4.25) in the post-protocol implementation group. Length of stay was 2.1 days in the control group and 1.8 days post-protocol implementation (p = .29). Patients who underwent concurrent neck dissection had a longer mean length of stay of 2.32 days compared to 1.66 days in those patients who did not undergo a neck dissection (p = .02). Hypocalcemia was also associated with a longer mean length of stay of 2.41 days compared to 1.60 days in patients who did not develop hypocalcemia (p < .01).
Conclusions:
The number of calcium blood draws was significantly reduced after introduction of a standardized protocol based on intraoperative PTH levels. The hospital length of stay did not change. Adoption of a standardized postoperative protocol based on intraoperative PTH levels may reduce the number of blood draws in children undergoing thyroidectomy.
More Related Videos

Related Concept Videos
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...