Related Experiment Video
Updated: Feb 14, 2026

Investigation into Deep Breathing through Measurement of Ventilatory Parameters and Observation of Breathing Patterns
Published on: September 16, 2019
Transnasal humidified rapid insufflation ventilatory exchange for oxygenation of children during apnoea: a
T Riva1, T H Pedersen1, S Seiler1
1Department of Anaesthesiology & Pain Therapy, Bern University Hospital, Inselspital, Freiburgstrasse 8, 3010 Bern, Switzerland.

Background:
Transnasal humidified rapid insufflation ventilatory exchange (THRIVE) comprises the administration of heated, humidified, and blended air/oxygen mixtures via nasal cannula at rates of ≥2 litres kg-1 min-1. The aim of this randomized controlled study was to evaluate the length of the safe apnoea time using THRIVE with two different oxygen concentrations (100% vs 30% oxygen) compared with standard low-flow 100% oxygen administration.
Methods:
Sixty patients, aged 1-6 yr, weighing 10-20 kg, undergoing general anaesthesia for elective surgery, were randomly allocated to receive one of the following oxygen administration methods during apnoea: 1) low-flow 100% oxygen at 0.2 litres kg-1 min-1; 2) THRIVE 100% oxygen at 2 litres kg-1 min-1; and 3) THRIVE 30% oxygen at 2 litres kg-1 min-1. Primary outcome was time to desaturation to 95%. Termination criteria included SpO2 decreased to 95%, transcutaneous CO2 increased to 65 mmHg, or apnoea time of 10 min.
Results:
The median (interquartile range) [range] apnoea time was 6.9 (5.7-7.8) [2.8-10.0] min for low-flow 100% oxygen, 7.6 (6.2-9.1) [5.2-10.0] min for THRIVE 100% oxygen, and 3.0 (2.4-3.7) [0.2-5.3] min for THRIVE 30% oxygen. No significant difference was detected between apnoea times with low-flow and THRIVE 100% oxygen administration (P=0.15). THRIVE with 30% oxygen demonstrated significantly shorter apnoea times (P<0.001) than both 100% oxygen modalities. The overall rate of transcutaneous CO2 increase was 0.57 (0.49-0.63) [0.29-8.92] kPa min-1 without differences between the 3 groups (P=0.25).
Conclusions:
High-flow 100% oxygen (2 litres kg-1 min-1) administered via nasal cannulas did not extend the safe apnoea time for children weighing 10-20 kg compared with low-flow nasal cannula oxygen (0.2 litres kg-1 min-1). No ventilatory effect was observed with THRIVE at 2.0 litres kg-1 min-1.
Clinical Trial Registration:
NCT02979067.
More Related Videos


Related Concept Videos
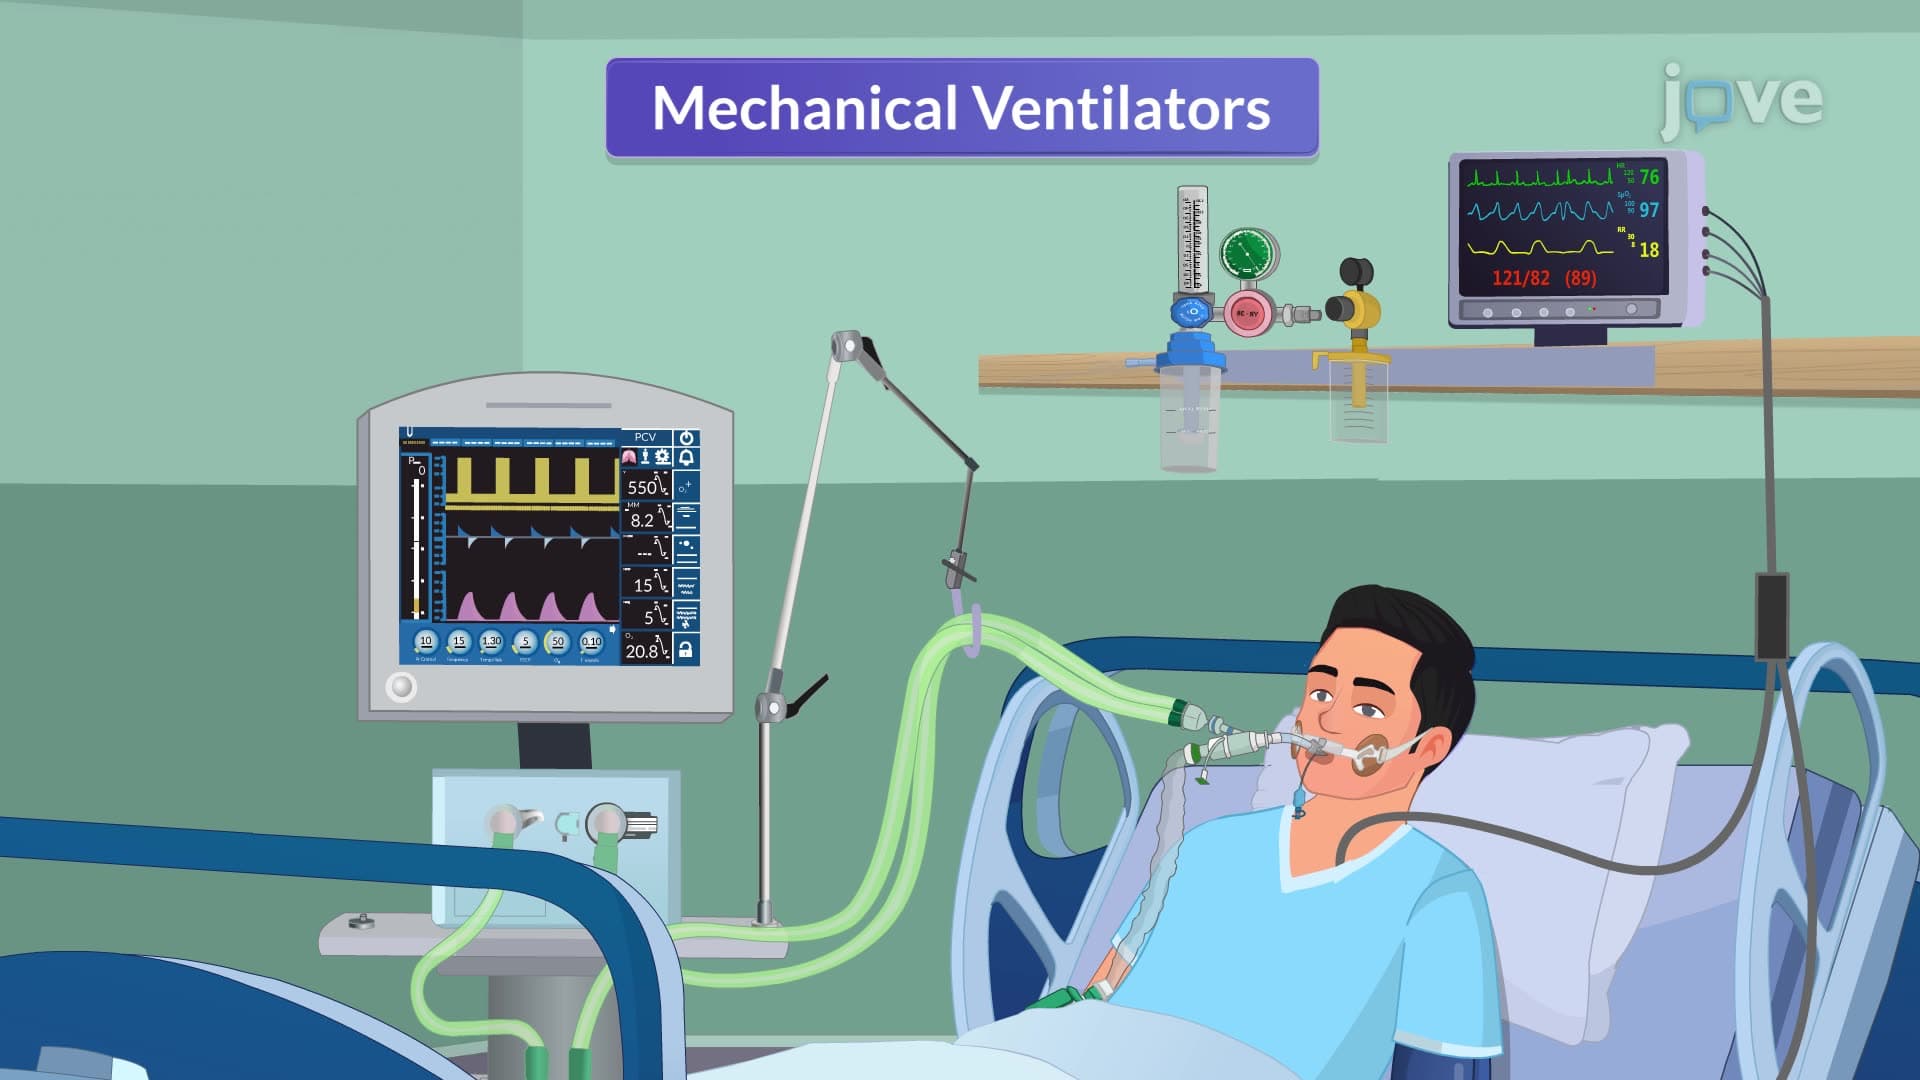 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:20
Gas Exchange and Transport
 02:06
Social Exchange Theory
 01:26
Social Exchange Theory
 01:12
Trial and Error and Algorithm
 01:11
Clinical Trials: Overview