Related Experiment Video
Updated: Feb 14, 2026

Single-Cell Calcium Imaging for Studying the Activation of Calcium Ion Channels
Published on: December 13, 2024
Differential effects of a single dose of oral calcium based on postpartum plasma calcium concentration in Holstein
B M Leno1, R C Neves2, I M Louge2
1Department of Animal Science, College of Veterinary Medicine, Cornell University, Ithaca, NY 14853.

Our objectives were to determine (1) the effect of a single dose of an oral Ca bolus within 24 h after parturition on plasma Ca concentration, (2) the response of primiparous (PP) and multiparous (MP) cows to this supplementation strategy, and (3) differential responses based on plasma Ca at enrollment. For objective 1, cows from 1 commercial dairy in New York State were enrolled within 19 h after parturition (mean ± standard deviation = 8.3 ± 5.3 h) and randomized within parity group (first, second, and ≥third) to control [CON (n = 25); no placebo] or a single dose bolus treatment [BOL (n = 25); 3 oral Ca boluses supplying 54 to 64 g of Ca]. Plasma Ca was measured repeatedly between 1 and 24 h following treatment. For objectives 2 and 3, cows on 6 commercial farms in New York State were assigned to treatment as for objective 1 (CON, n = 1,973; BOL, n = 1,976). Herd records for health, reproduction, and Dairy Herd Improvement Association test day milk production were collected. Mixed effect multivariable models were developed using repeated measures ANOVA, Poisson regression, or proportional hazard models. Objective 2 analyses considered treatment with periparturient risk factors, whereas objective 3 analyses also considered Ca status. No difference was observed for plasma Ca between 1 and 24 h after treatment. Primiparous cows assigned to BOL calving at >712 d old had decreased risk of one or more health disorders [≤30 d in milk; risk ratio (RR) = 0.65, 95% confidence interval (CI) = 0.51 to 0.84] and those with body condition score >3.5 responded to BOL with increased milk production (CON = 31.7 ± 1.1, BOL = 35.1 ± 1.1 kg/d), as did those with days carried calf >277 (CON = 31.9 ± 1.0, BOL = 34.7 ± 1.0 kg/d). Reduced risk of one or more health disorders was observed in parity ≥3 (RR = 0.85, 95% CI = 0.81 to 0.89) and MP cows with body condition score >3.5 (retained placenta; RR = 0.70, 95% CI = 0.58 to 0.84) or that were lame (displaced abomasum; RR = 0.49, 95% CI = 0.32 to 0.75). Differential responses for PP cows by Ca status were minimal. For MP cows with low plasma Ca, BOL decreased risk of additional Ca treatment (≤1.8 mmol/L; RR = 0.57, 95% CI = 0.40 to 0.80) as well as risk of one or more health disorders (≤2.15 mmol/L; RR = 0.90, 95% CI = 0.85 to 0.95). Supplementation with a single oral dose of Ca could be targeted to periparturient risk groups for improved health. Calcium status did not differentiate responses of PP cows, but MP cows with low Ca at parturition had improved health status when supplemented.
Our objectives were to determine (1) the effect of a single dose of an oral Ca bolus within 24 h after parturition on plasma Ca concentration, (2) the response of primiparous (PP) and multiparous (MP) cows to this supplementation strategy, and (3) differential responses based on plasma Ca at enrollment. For objective 1, cows from 1 commercial dairy in New York State were enrolled within 19 h after parturition (mean ± standard deviation = 8.3 ± 5.3 h) and randomized within parity group (first, second, and ≥third) to control [CON (n = 25); no placebo] or a single dose bolus treatment [BOL (n = 25); 3 oral Ca boluses supplying 54 to 64 g of Ca]. Plasma Ca was measured repeatedly between 1 and 24 h following treatment. For objectives 2 and 3, cows on 6 commercial farms in New York State were assigned to treatment as for objective 1 (CON, n = 1,973; BOL, n = 1,976). Herd records for health, reproduction, and Dairy Herd Improvement Association test day milk production were collected. Mixed effect multivariable models were developed using repeated measures ANOVA, Poisson regression, or proportional hazard models. Objective 2 analyses considered treatment with periparturient risk factors, whereas objective 3 analyses also considered Ca status. No difference was observed for plasma Ca between 1 and 24 h after treatment. Primiparous cows assigned to BOL calving at >712 d old had decreased risk of one or more health disorders [≤30 d in milk; risk ratio (RR) = 0.65, 95% confidence interval (CI) = 0.51 to 0.84] and those with body condition score >3.5 responded to BOL with increased milk production (CON = 31.7 ± 1.1, BOL = 35.1 ± 1.1 kg/d), as did those with days carried calf >277 (CON = 31.9 ± 1.0, BOL = 34.7 ± 1.0 kg/d). Reduced risk of one or more health disorders was observed in parity ≥3 (RR = 0.85, 95% CI = 0.81 to 0.89) and MP cows with body condition score >3.5 (retained placenta; RR = 0.70, 95% CI = 0.58 to 0.84) or that were lame (displaced abomasum; RR = 0.49, 95% CI = 0.32 to 0.75). Differential responses for PP cows by Ca status were minimal. For MP cows with low plasma Ca, BOL decreased risk of additional Ca treatment (≤1.8 mmol/L; RR = 0.57, 95% CI = 0.40 to 0.80) as well as risk of one or more health disorders (≤2.15 mmol/L; RR = 0.90, 95% CI = 0.85 to 0.95). Supplementation with a single oral dose of Ca could be targeted to periparturient risk groups for improved health. Calcium status did not differentiate responses of PP cows, but MP cows with low Ca at parturition had improved health status when supplemented.

Related Concept Videos
 01:27
Feedback Regulation of Calcium Concentration
Various transmembrane receptors, such as G protein-coupled receptors (GPCRs), elicit a response to extracellular signals by increasing cytosolic calcium. Activated GPCRs...
 01:21
Skeleton and Calcium Homeostasis
 01:28
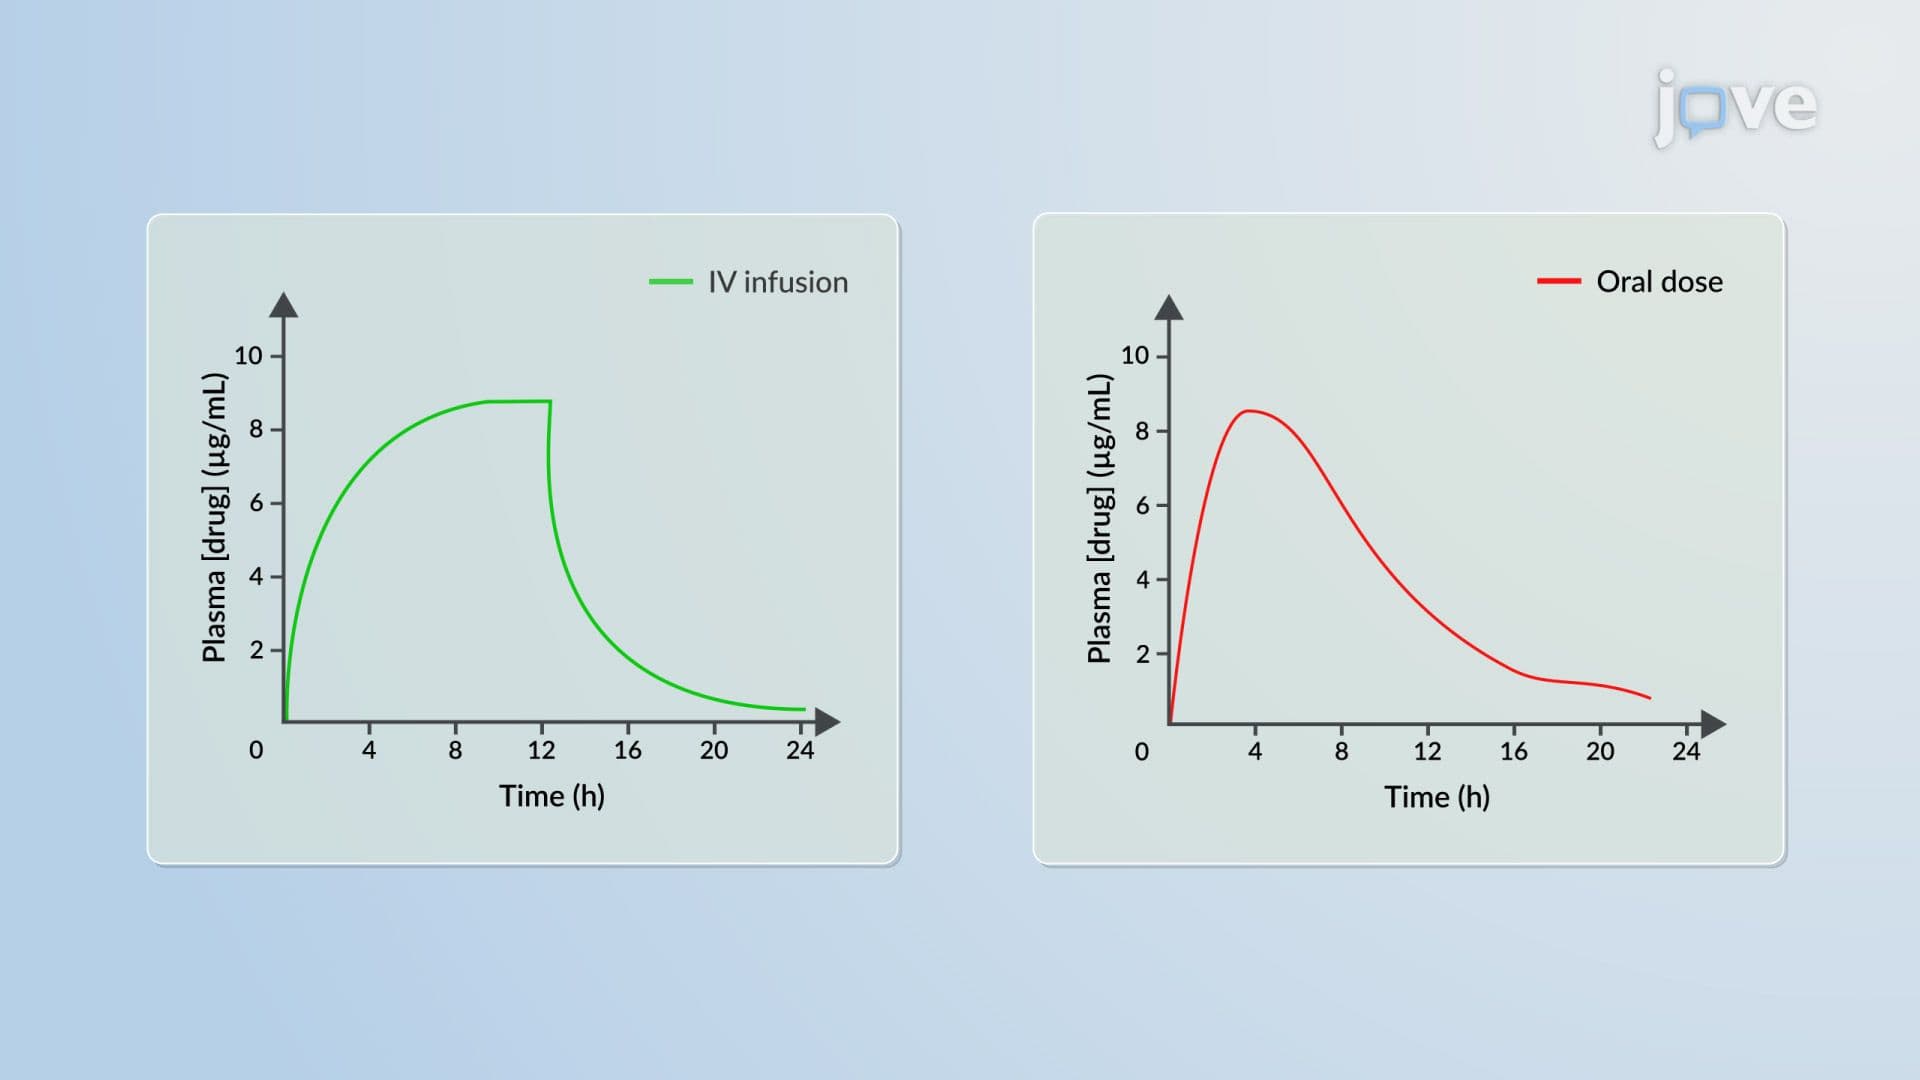
IV Infusion to Oral Dosing: Conversion Methods
 01:27
Roles of Electrolytes: Calcium and Phosphate
The calcium concentration in blood plasma is primarily...
 01:20
Radical Reactivity: Concentration Effects
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...