Related Experiment Video
Updated: Feb 14, 2026
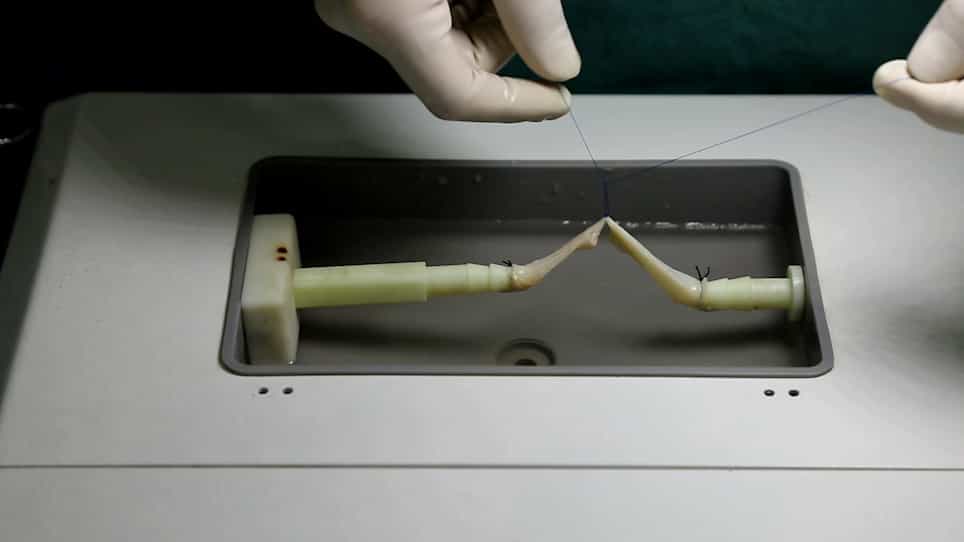
A Training and Testing System for Performing Vascular Reconstruction In Vitro
Published on: October 26, 2019
Vascular surgery during U.S. combat operations from 2002 to 2016: Analysis of vascular procedures performed to inform
Caryn A Turner1, Zsolt T Stockinger, Jennifer M Gurney
1From the Joint Trauma System (C.A.T., Z.T.S., J.M.G.), Fort Sam Houston, Texas.

Background:
Vascular surgery constitutes approximately 6.5% of surgical procedures performed for combat injuries, yet general surgeons are increasingly unfamiliar with vascular surgery. This study examines the frequency and type of vascular surgical procedures performed during recent US Military operations from 2002 to 2016.
Methods:
A retrospective analysis of the Department of Defense Trauma Registry was performed for all Role (R)2 and R3 medical treatment facilities (MTFs), from January 2002 to May 2016. A total of 106 International Classification of Diseases-9th Rev.-Clinical Modification (ICD-9-CM) procedure codes were categorized as vascular and were included in the present analysis. Procedure codes were separated by anatomic location and procedure type. Ligation as part of an amputation was excluded. Grafts were further subdivided by type: synthetic, autologous, and unknown. Procedure grouping and categorization were determined by subject matter experts. Data analysis used Stata Version 14 (College Station, TX).
Results:
A total of 25,816 vascular surgical procedures were identified at R2 and R3 MTFs. Role 3 MTFs reported more than four times the number of procedures compared to R2 MTFs. The most common anatomic locations documented were extremity (64.96%) and not otherwise specified (28.1%). The most common procedures overall were amputation (33.36%) and fasciotomy (18.83%). The most common graft type was autologous (68.87%), and the least common was synthetic (5.69%).
Conclusion:
While amputation, fasciotomy, and ligation were the most common vascular procedures performed for combat trauma, the need for definitive repair including grafting is common at both R2 and R3 MTFs. Vascular surgery therefore remains a necessary skill set for the deployed US Military surgeon; military general surgeons need to train and sustain their vascular skills, including proficiency at amputation and fasciotomy.
Level Of Evidence:
Epidemiologic study, level III.


Related Concept Videos
 03:24
Seedless Vascular Plants
 01:16
Vascular Spasm
 01:20
Overview of the Vascular System
 01:20
Vascular Resistance
The primary determinants of vascular resistance are vessel diameter, blood viscosity, and vessel length. Among these, vessel diameter plays the most significant role due to the fourth power relationship described by...
 02:26
Non-vascular Seedless Plants
 01:30
Inflammatory Response I: Vascular and Cellular