Related Experiment Video
Updated: Feb 14, 2026


Predicting the Effectiveness of Population Replacement Strategy Using Mathematical Modeling
Published on: July 4, 2007
Effects of β-Blockers on Maximal Heart Rate Prediction Equations in a Cardiac Population
Elizabeth Godlasky1, Trisha Hoffman, Sonya Weber-Peters
1The Penn State University Milton S. Hershey Medical Center, Heart and Vascular Institute, Hershey, Pennsylvania (Mss Godlasky, Hoffman, and Weber-Peters, Messrs Bradford and Miller, and Dr Lott); and Public Health Sciences, Penn State University Hershey, Pennsylvania (Mr Kunselman).

Insights
New maximal heart rate (HRmax) prediction equations for coronary artery disease (CAD) patients on beta-blocker (BB) therapy were derived. Patients holding BB therapy can use standard equations, but those taking BBs require specific HRmax formulas.
Area of Science:
- Cardiology
- Exercise Physiology
- Pharmacology
Background:
- Maximal heart rate (HRmax) prediction is crucial for exercise prescription and stress testing in patients with coronary artery disease (CAD).
- Existing HRmax equations may not accurately reflect physiological responses in CAD patients, particularly those on beta-blocker (BB) therapy.
- Understanding the impact of BBs on HRmax is essential for safe and effective exercise management in this population.
Purpose of the Study:
- To develop specific HRmax prediction equations for CAD patients undergoing exercise testing, stratified by BB therapy status.
- To compare the accuracy of newly derived equations against established HRmax prediction formulas (e.g., Fox, Brawner).
- To assess the influence of BB therapy timing (held vs. continued) on achieved HRmax during exercise testing.
Main Methods:
- Retrospective analysis of stress echocardiogram treadmill tests in patients diagnosed with CAD.
- Patients were categorized into three groups: no BB therapy, BB therapy held 12-24 hours prior, and BB therapy continued on test day.
- HRmax prediction equations were derived for each group, and their accuracy was compared to existing formulas using mean bias analysis.
Main Results:
- Specific HRmax equations were derived: no BB = 200 - 0.79 × age; held BB = 193 - 0.71 × age; took BB = 168 - 0.51 × age.
- Achieved HRmax was not significantly different between the no BB and held BB groups.
- The 'took BB' group exhibited significantly lower HRmax. Existing equations (Fox, Brawner) showed significant over- or underestimation of achieved HRmax in different patient groups.
Conclusions:
- For CAD patients holding BB therapy on the test day, HRmax estimation equations used for patients never on BBs are applicable.
- The Brawner (no BB) equation demonstrated comparable performance to equations derived for CAD patients holding BBs.
- Further research is warranted to optimize the timing of BB administration in relation to exercise testing for accurate HRmax assessment.
Purpose:
To derive specific maximal heart rate (HRmax) prediction equations for a coronary artery disease (CAD) population based upon status of β-blocker (BB) therapy and to compare these to prior HRmax equations (Fox and Brawner-specific for CAD).
Methods:
We retrospectively reviewed stress echocardiogram treadmill tests in patients with CAD, dividing subjects into 3 groups based upon BB use on test day: not prescribed BB therapy (no BB group; n = 110); held for 12 to 24 hr prior (held BB group; n = 155); and continued taking (took BB group; n = 72).
Results:
Derived HRmax equations for our CAD population were no BB = 200 - 0.79 × age; held BB = 193 - 0.71 × age; and took BB = 168 - 0.51 × age. Achieved HRmax mean was not significantly different between held BB and no BB groups; however, HRmax in the took BB group was significantly lower. Fox and Brawner (no BB)-HRmax equations significantly overestimated (+6 and +9 mean bias) and underestimated (-8 and -6 mean bias) achieved HRmax in no BB and held BB groups, respectively. The Brawner (no BB) equation intercept and slope were not significantly different from our CAD-held BB and no BB equations. The Brawner (on BB) equation intercept and slope were similar to our took BB equation, but greatly underestimated achieved HRmax (-17 mean bias).
Conclusion:
For patients holding BB therapy on test day, a similar CAD HRmax estimation equation to those patients never on BB can be used, comparable to the Brawner (no BB) equation. Further research is needed to determine when patients should take their BB therapy in conjunction with exercise testing.
More Related Videos
 08:51
Intra-cardiac Side-Firing Light Catheter for Monitoring Cellular Metabolism using Transmural Absorbance Spectroscopy of Perfused Mammalian Hearts
Published on: May 12, 2019
 08:14
Capturing the Cardiac Injury Response of Targeted Cell Populations via Cleared Heart Three-Dimensional Imaging
Published on: March 17, 2020
Related Concept Videos
 01:22
Heart Failure Drugs: β-Blockers
 01:19
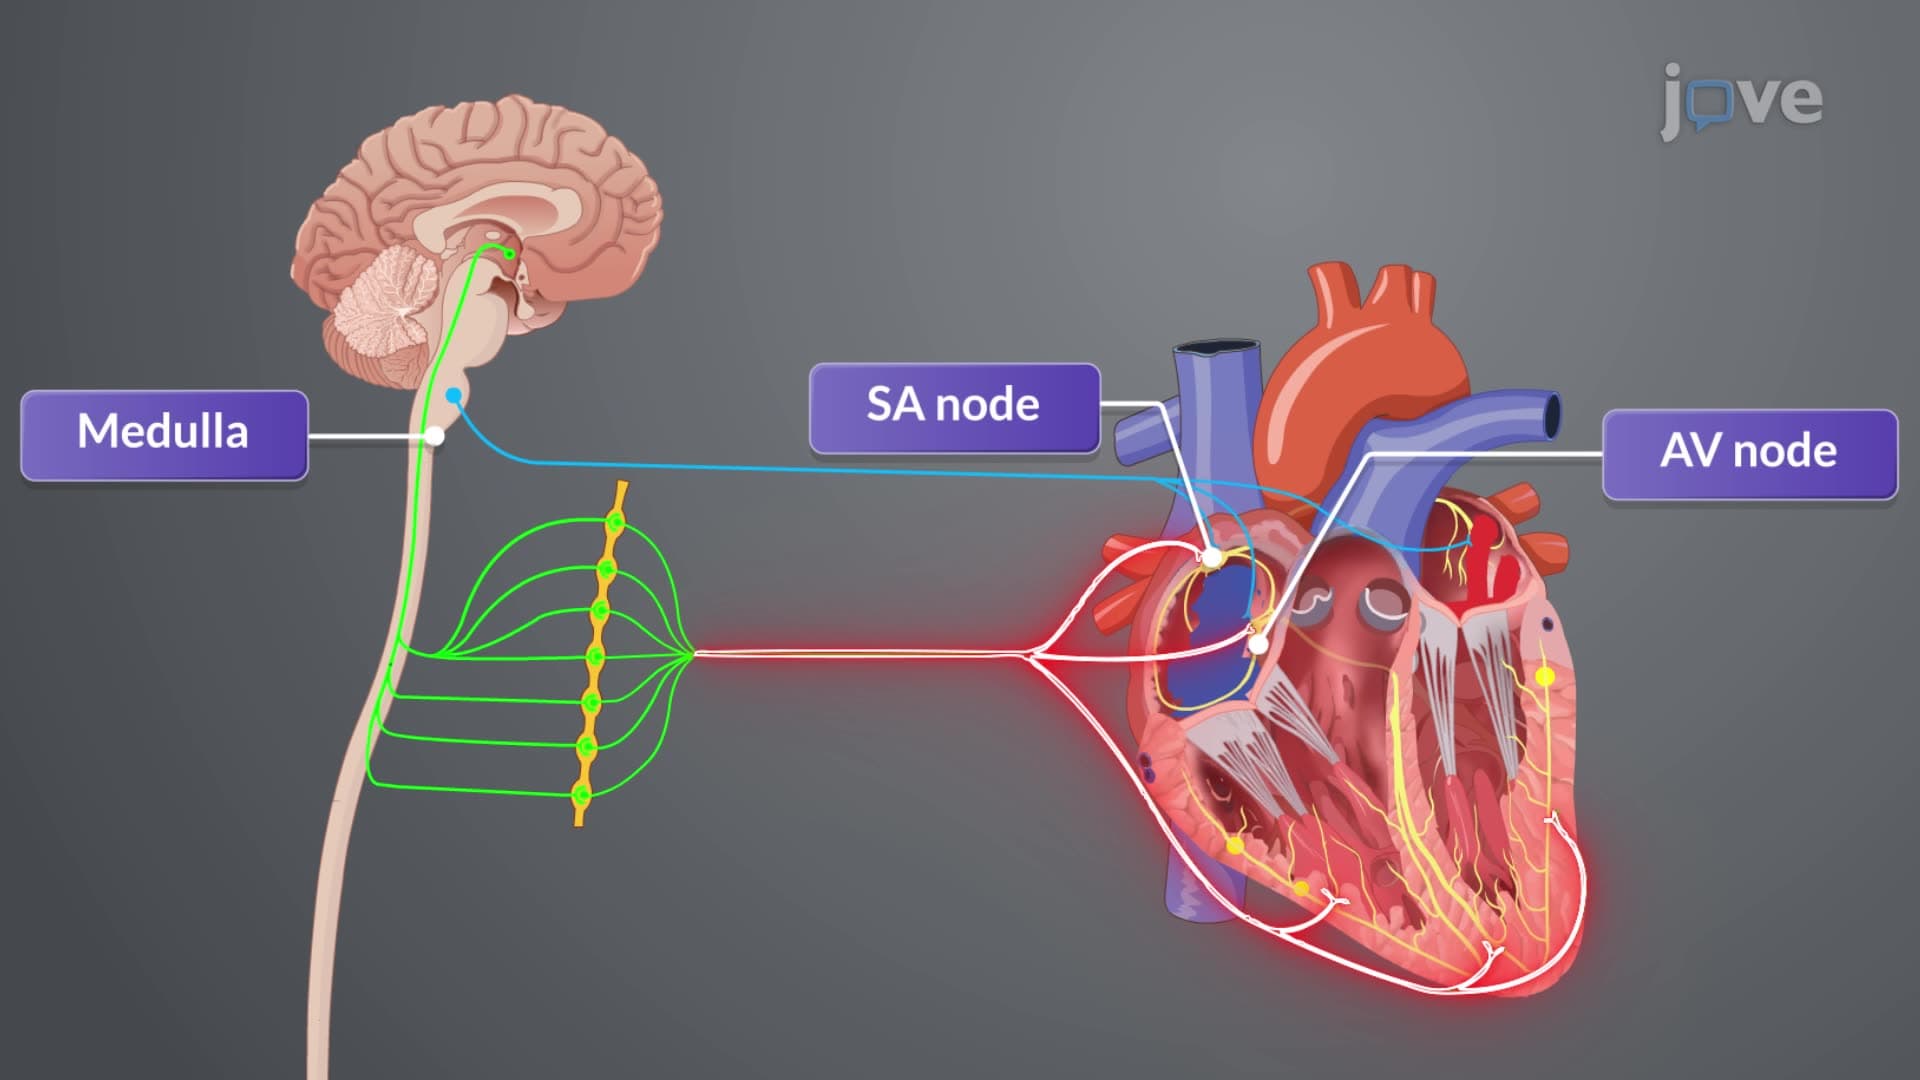
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:16
Antianginal Drugs: Nitrates and β-Blockers
Organic nitrates, such as nitroglycerin, play a pivotal role. Once metabolized, they liberate nitric oxide, a molecular marvel. Nitric oxide triggers guanylyl cyclase and augments cGMP production. This biochemical cascade orchestrates the relaxation of vascular smooth muscles, ushering in vasodilation and enhancing coronary blood flow....
 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:31
Regulation of Heart Rates
The SNS increases heart rate through the release of norepinephrine and epinephrine, which act on beta-1 adrenergic receptors in the heart. This action increases the rate of depolarization in the sinoatrial (SA) node, the heart's...