Related Experiment Video
Updated: Feb 14, 2026
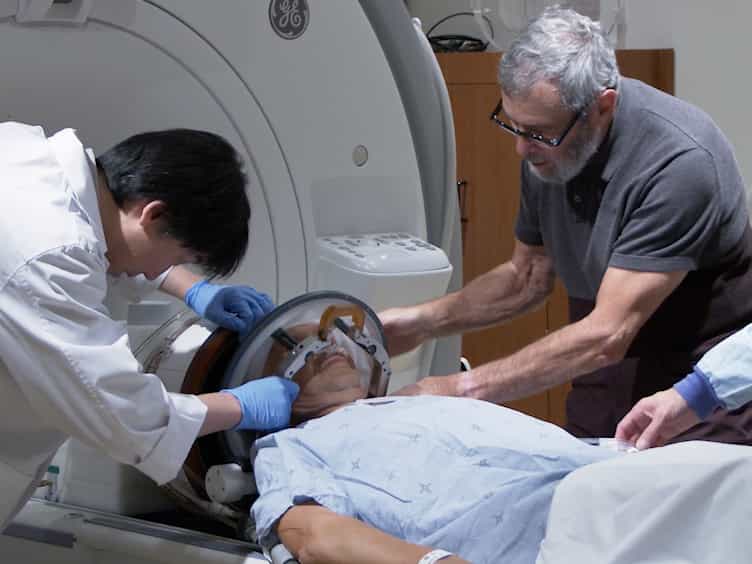

MRI-guided Focused Ultrasound Thalamotomy for Patients with Medically-refractory Essential Tremor
Published on: December 13, 2017
[Cardiovascular Medication in Elderly Patients]

Insights
Elderly individuals face higher risks of atherosclerotic diseases, heart failure, and atrial fibrillation. Guideline-based treatments may cause polypharmacy, necessitating careful drug selection and consideration of reduced kidney function in older adults.
Area of Science:
- Gerontology
- Cardiology
- Clinical Pharmacology
Background:
- Elderly populations have a higher incidence of atherosclerotic diseases, leading to increased prevalence of heart failure and atrial fibrillation.
- Current treatment guidelines can result in polypharmacy (use of >5 drugs daily), increasing the risk of drug interactions and adverse events, particularly in older adults with diminished kidney function.
Purpose of the Study:
- To evaluate the evidence-based use of cardiovascular medications in the elderly, focusing on efficacy, safety, and specific conditions like heart failure and atrial fibrillation.
- To highlight the importance of individualized treatment strategies considering age-related physiological changes and the risk-benefit profile of medications.
Main Methods:
- Systematic review of clinical trials and guidelines pertaining to cardiovascular disease management in elderly patients.
- Analysis of drug efficacy in prolonging life or reducing symptoms, with specific attention to primary prevention, heart failure subtypes, and anticoagulation in atrial fibrillation.
Main Results:
- Limited evidence supports routine use of low-dose aspirin or lipid-lowering agents for primary prevention in the elderly.
- ACE inhibitors, beta-blockers, and MRAs improve outcomes in Heart Failure with reduced Ejection Fraction (HFrEF), but not in HFmEF or HFpEF, even in older adults.
- Oral anticoagulation offers the highest absolute benefit for stroke prevention in elderly atrial fibrillation patients, with NOACs showing comparable efficacy and improved safety over warfarin.
Conclusions:
- Treatment decisions for cardiovascular conditions in the elderly should prioritize drugs with proven benefits in controlled trials, carefully weighing risks like polypharmacy and reduced kidney function.
- Discontinuation of long-term diuretic therapy in elderly patients may precipitate heart failure symptoms or hypertension.
- Beta-blockers are beneficial for symptom control and reducing interventions post-myocardial infarction in coronary heart disease patients.
Abstract:
Elderly people show increased probability to develop atherosclerotic diseases; in consequence heart failure - most often following coronary heart disease - as well as atrial fibrillation is more common. Following guidelines may lead to polypharmacy, i. e. use of more than 5 drugs daily. Thus, drug interactions as well as side effects become more likely; especially in elderly patients reduced kidney function has to be taken into account. Only drugs which have shown to prolong life or to reduce symptoms in controlled clinical trials should be used. There is little evidence to use low dose aspirin or lipid lowering agents in primary prevention especially in elderly. ACE inhibitors, β blocker and MRA are effective to improve symptoms and outcome in HFrEF but not in HFmEF or HFpEF. This also holds true for the elderly. Withdrawal of long term diuretic treatment in the elderly patients may lead to symptoms of heart failure or increase in blood pressure to hypertensive values often. In coronary heart disease ß blocker may be used to control symptoms as well as to reduce the need for coronary intervention following 1 year after myocardial infarction. Because the risk of stroke increases with age more than the risk of bleeding, the absolute benefit of oral anticoagulation in atrial fibrillation patients is highest in the elderly. NOAK appear to be safer and at least as efficacious as warfarin.
Related Concept Videos
 01:14
Overview of the Cardiovascular System
Heart
The heart is the central pump of the cardiovascular system that circulates blood throughout the body. It comprises two atria receiving the blood and two ventricles pumping blood out of the heart. Their rhythmic contractions, called heartbeats, ensure that blood flow remains continuous.
Blood Vessels
Blood...
 01:23
Inhaled Medications
 01:27
Regulation of the Cardiovascular System
The regulation of the cardiovascular system involves the autonomic nervous system (ANS), baroreceptors, and chemoreceptors, ensuring that heart rate and blood pressure are appropriately modulated in response to varying physiological demands.
The ANS comprises two main divisions: the sympathetic and parasympathetic nervous systems. The sympathetic nervous system enhances...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:29
Assessment of the Cardiovascular System II: Inspection
Head and Neck
 01:27
Psychoneuroimmunology: Cardiovascular Disease
A key area of focus in PNI is the relationship between stress and coronary...