Related Experiment Video
Updated: Feb 14, 2026


Heterotopic Auxiliary Rat Liver Transplantation With Flow-regulated Portal Vein Arterialization in Acute Hepatic Failure
Published on: September 13, 2014
Acute liver failure in children-Is living donor liver transplantation justified?
Marek Szymczak1, Piotr Kaliciński1, Grzegorz Kowalewski1
1Department of Pediatric Surgery & Organ Transplantation, The Children's Memorial Health Institute, Warsaw, Poland.

Insights
Living donor liver transplantation (LDLT) offers excellent outcomes for pediatric patients with acute liver failure (ALF), demonstrating reduced waiting times and improved graft function compared to deceased donor liver transplantation (DDLT). This life-saving procedure shows very low morbidity and no mortality in living donors when performed by experienced teams.
Area of Science:
- Hepatology
- Pediatric Surgery
- Transplantation Medicine
Background:
- Acute liver failure (ALF) in children necessitates timely liver transplantation.
- Living donor liver transplantation (LDLT) has emerged as a viable alternative to deceased donor liver transplantation (DDLT).
Purpose of the Study:
- To analyze and compare the outcomes of LDLT versus DDLT in pediatric patients with ALF.
- To evaluate graft characteristics, complications, and long-term results based on donor type.
Main Methods:
- Retrospective analysis of 63 pediatric ALF patients who underwent liver transplantation (1997-2016).
- Comparison of clinical data between 24 LDLT recipients and 39 DDLT recipients.
- Evaluation of factors including waiting time, graft function, complications, and donor morbidity.
Main Results:
- LDLT recipients experienced shorter waiting times and significantly shorter cold ischemia times (4 vs. 9.2 hours).
- LDLT showed no primary non-function (PNF) and excellent early graft function (83.3%), with no late mortality.
- DDLT had a PNF rate of 10.2%, lower early graft function (51.2%), and both early (20.5%) and late (5.1%) mortality.
Conclusions:
- LDLT is a life-saving procedure for pediatric ALF patients, yielding excellent results.
- LDLT is associated with superior outcomes, including reduced waiting times and improved graft survival.
- Living donor procedures, when conducted by experienced teams with strict protocols, demonstrate minimal donor morbidity and no mortality.
Objectives:
Living donor liver transplantation (LDLT) in patients with acute liver failure (ALF) has become an acceptable alternative to transplantation from deceased donors (DDLT). The aim of this study was to analyze outcomes of LDLT in pediatric patients with ALF based on our center's experience.
Material And Methods:
We enrolled 63 children (at our institution) with ALF who underwent liver transplantation between 1997 and 2016. Among them 24 (38%) underwent a LDLT and 39 (62%) received a DDLT. Retrospectively analyzed patient clinical data included: time lapse between qualification for transplantation and transplant surgery, graft characteristics, postoperative complications, long-term results post-transplantation, and living donor morbidity. Overall, we have made a comparison of clinical results between LDLT and DDLT groups.
Results:
Follow-up periods ranged from 12 to 182 months (median 109 months) for LDLT patients and 12 to 183 months (median 72 months) for DDLT patients. The median waiting time for a transplant was shorter in LDLT group than in DDLT group. There was not a single case of primary non-function (PNF) in the LDLT group and 20 out of 24 patients (83.3%) had good early graft function; 3 patients (12.5%) in the LDLT group died within 2 months of transplantation but there was no late mortality. In comparison, 4 out of 39 patients (10.2%) had PNF in DDLT group while 20 patients (51.2%) had good early graft function; 8 patients (20.5%) died early within 2 months and 2 patients (5.1%) died late after transplantation. The LDLT group had a shorter cold ischemia time (CIT) of 4 hours in comparison to 9.2 hours in the DDLT group (p<0.0001).
Conclusions:
LDLT is a lifesaving procedure for pediatric patients with ALF. Our experience showed that it may be performed with very good results, and with very low morbidity and no mortality among living donors when performed by experienced teams following strict procedures.
Related Concept Videos
 01:27
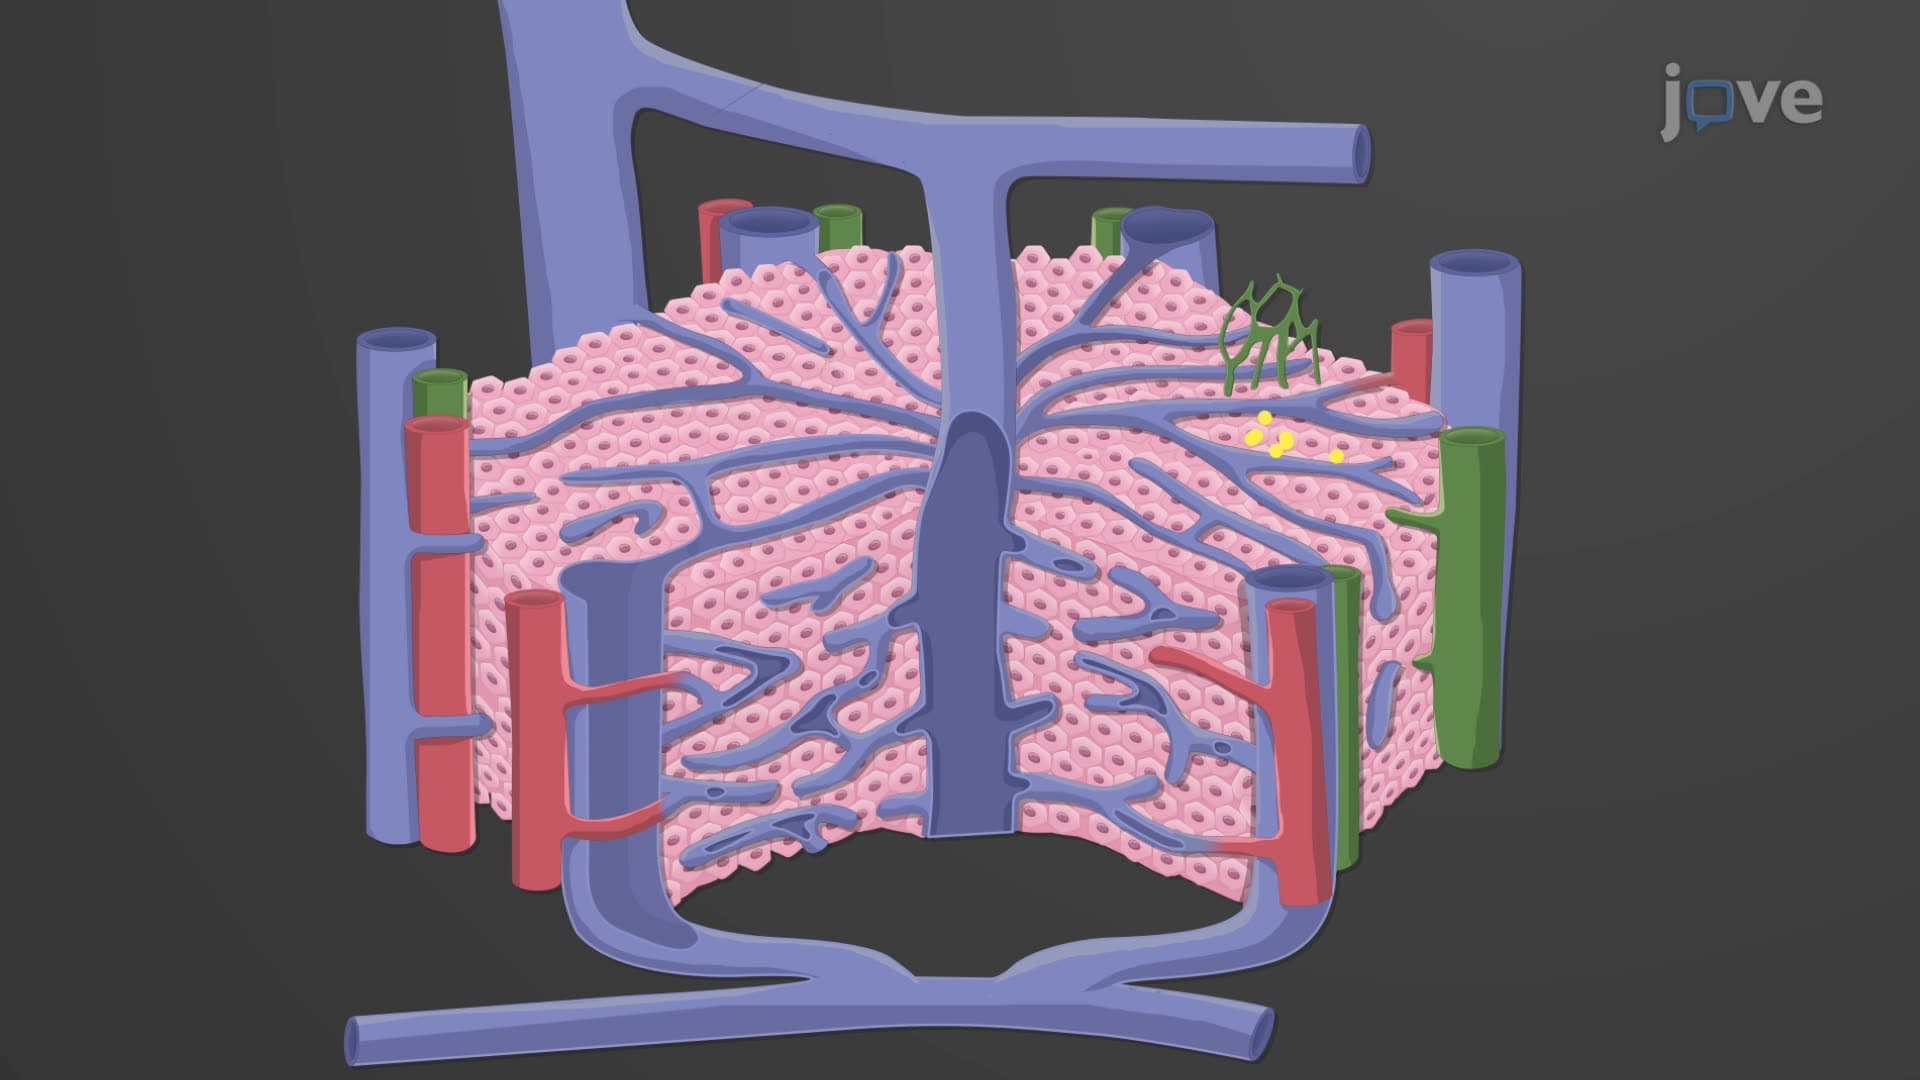
Liver Histology
Hepatocytes perform a variety of essential functions. They secrete...
 01:30
Liver Physiology
Metabolic Regulation:
The liver is the central organ involved in regulating blood composition. It stabilizes blood glucose levels, maintaining them within the range of 70–110 mg/dL. When these levels drop, the liver breaks down glycogen reserves and releases glucose into the bloodstream. It can...
 01:24
Liver Regeneration
Cells of Liver
The liver comprises four major types of cells— hepatocytes, stellate, Kupffer, and sinusoidal endothelial cells. The hepatocytes are...
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...