Related Experiment Video
Updated: Feb 14, 2026


Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
Impact of achieved systolic blood pressure on renal function in hypertensive patients
Peter M Okin1, Sverre E Kjeldsen2,3, Richard B Devereux1
1Greenberg Division of Cardiology, Weill Cornell Medical College, 525 East 68th Street, New York, NY 10065,USA.

Insights
Lower systolic blood pressure (SBP) in hypertensive patients with left ventricular hypertrophy (LVH) was linked to slower kidney function decline over four years. This suggests potential renal benefits from more intensive blood pressure management.
Area of Science:
- Nephrology
- Cardiology
- Hypertension Research
Background:
- High blood pressure (BP) is strongly associated with impaired kidney function.
- While baseline BP predicts chronic kidney disease (CKD) progression, intensive BP control's effect on glomerular filtration rate (GFR) decline in CKD patients remains unclear.
Purpose of the Study:
- To investigate the relationship between achieved systolic blood pressure (SBP) and estimated GFR (eGFR) changes over time in hypertensive patients with electrocardiogram (ECG) left ventricular hypertrophy (LVH).
Main Methods:
- Analysis of 8778 hypertensive patients with ECG LVH from a randomized trial comparing losartan- and atenolol-based treatments.
- eGFR was estimated using the Modification of Diet in Renal Disease (MDRD) study equation.
- Patients were grouped by average on-treatment SBP: ≤130 mmHg, 131–141 mmHg, and ≥142 mmHg.
Main Results:
- Patients with lower on-treatment SBP (≤130 mmHg) had significantly lower baseline eGFR compared to higher SBP groups.
- However, the decrease in eGFR over 4 years was significantly slower in the lowest SBP group (≤130 mmHg) compared to higher SBP groups.
- These findings were independent of baseline eGFR and other risk factors.
Conclusions:
- Lower average on-treatment SBP (≤130 mmHg) in hypertensive patients with ECG LVH is associated with a slower rate of eGFR decline over 4 years.
- This association persists independently of other risk factors for reduced GFR.
- Further research is needed to confirm if targeting lower SBP goals offers greater renal protection.
Aims:
There is strong evidence for the association of high blood pressure (BP) with depressed renal function. Although high BP at baseline is associated with greater progression of chronic kidney disease (CKD), randomized trials in CKD patients have found no significant relationship between more intensive BP control and glomerular filtration rate (GFR) decline. However, the relationship of GFR and change in GFR over time to lower achieved systolic BP (SBP) in hypertensive patients undergoing treatment is unclear.
Methods And Results:
Baseline estimated GFR (eGFR) and change in eGFR during follow-up were examined in relation to average on-treatment SBP in 8778 hypertensive patients with ECG left ventricular hypertrophy (LVH) randomly assigned to losartan- or atenolol-based treatment. GFR was estimated using the Modification of Diet in Renal Disease study equation. Patients with average on-treatment SBP ≤130 mmHg (lowest quintile at last measurement) and average SBP between 131 and 141 mmHg were compared with patients with average SBP ≥142 mmHg (median SBP at last measurement). Patients with an average on-treatment SBP ≤130 mmHg had significantly lower baseline eGFR than those with average SBP between 131 and 141 or average SBP ≥142 mmHg (65.5 ± 14.3 vs. 69.3 ± 14.3 vs. 69.0 ± 14.5 mL/min/1.73 m2, P < 0.001 using analysis of covariance adjusting for age, sex, race, randomized treatment, prior antihypertensive treatment, history of diabetes, myocardial infarction, ischaemic heart disease or heart failure, smoking status, baseline serum glucose, total and HDL cholesterol, albuminuria, and baseline LVH by Cornell product and Sokolow-Lyon voltage). However, the decrease in eGFR between baseline and Year 4 was significantly lower among patients with average SBP ≤130 mmHg (-6.3 ± 10.3 vs. -7.9 ± 11.1 vs. -9.2 ± 10.6 mL/min/1.73 m2, P = 0.001 when adjusting for the same variables and for change in Cornell product and Sokolow-Lyon voltage between baseline and Year 4). These differences in eGFR change persisted even after adjusting for baseline eGFR, and there were no significant interactions with randomized treatment, sex, race, or baseline presence of proteinuria.
Conclusion:
Lower average on-treatment SBP (≤130 mmHg) was associated with a lower baseline eGFR but with a slower reduction in eGFR during 4-year follow-up in hypertensive patients with ECG LVH, independent of other possible risk factors for decreased GFR. Further study is necessary to determine whether randomized treatment to lower SBP goals is more protective of renal function than treatment to standard SBP goals.
Clinical Trial Registration:
http://clinicaltrials.gov/ct/show/NCT00338260?order=1; unique identifier: NCT00338260.


Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:24
Blood Pressure
 01:30
Blood Pressure
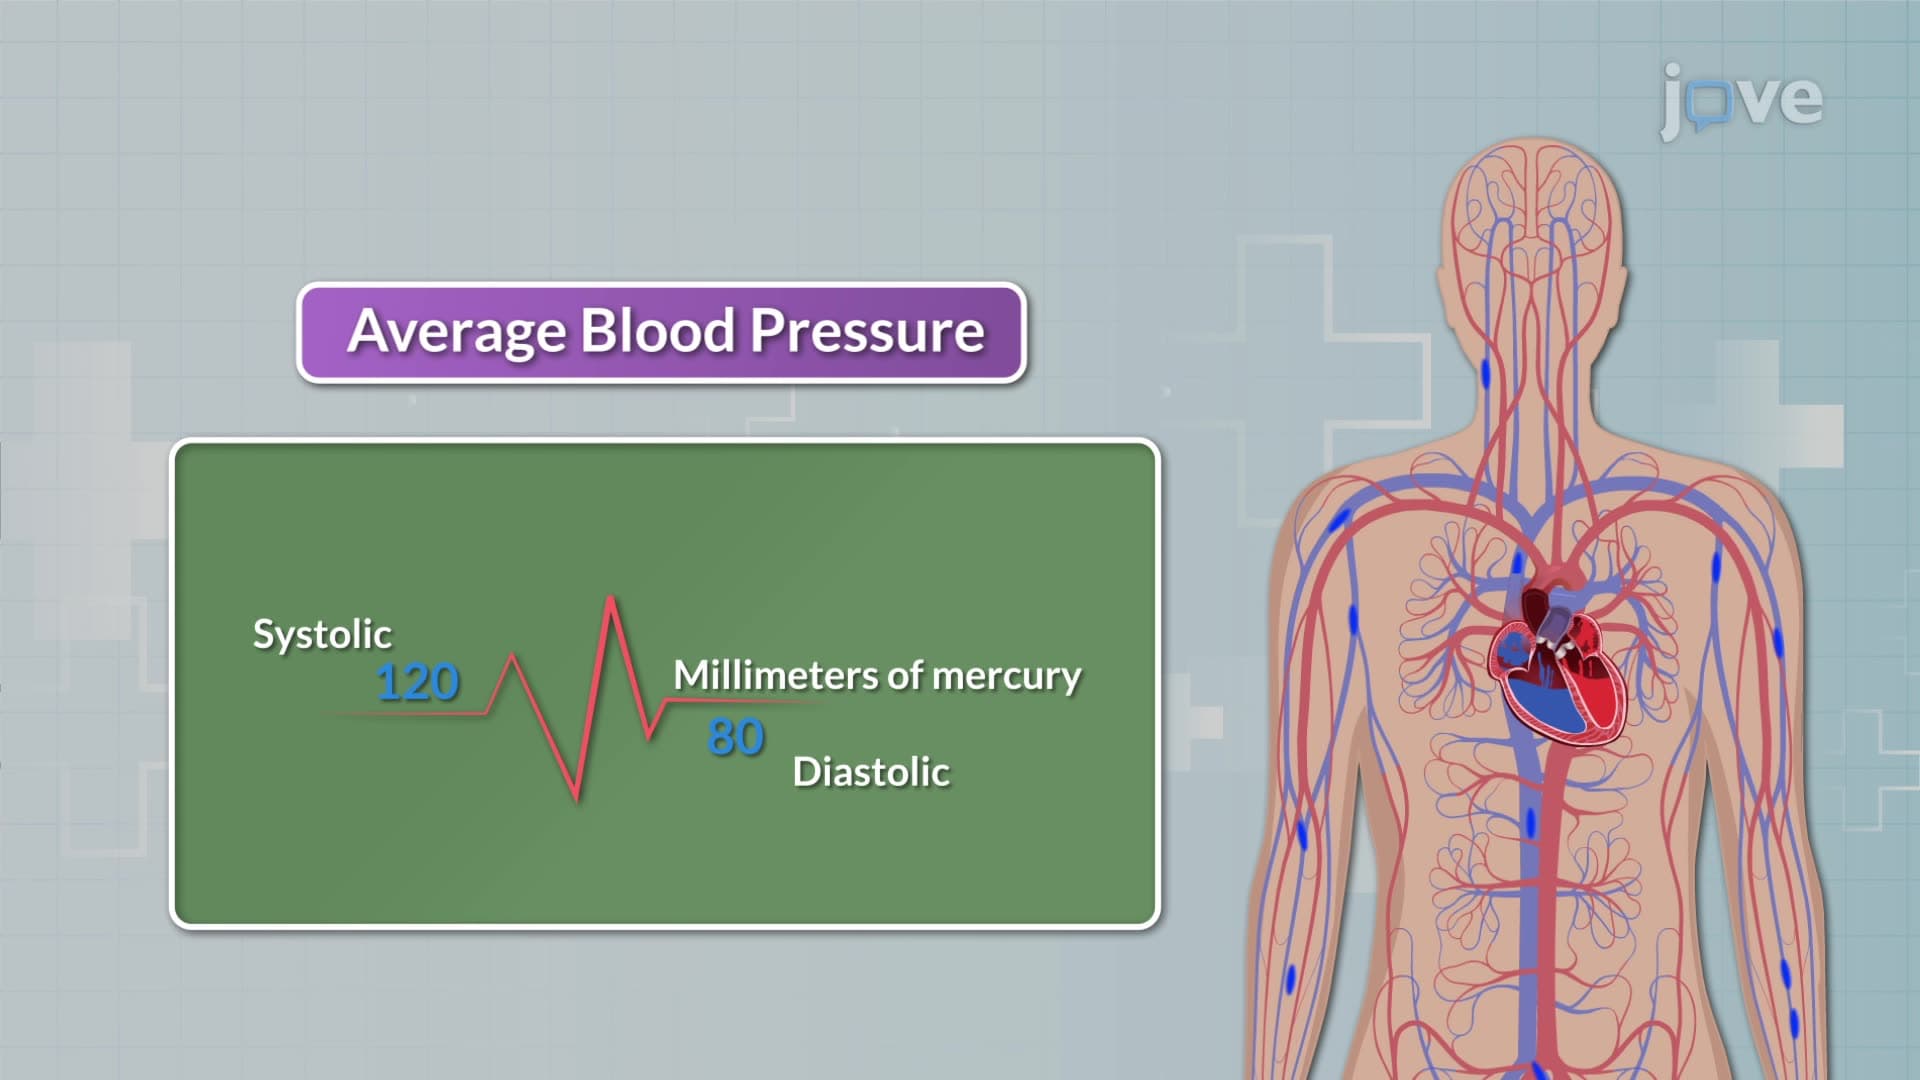
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:17
Measurement of Blood Pressure
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart...