Related Experiment Video
Updated: Feb 13, 2026


Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Chronic Administration of Hydroxyurea (HU) Benefits Caucasian Patients with Sickle-Beta Thalassemia
Rosario Di Maggio1, Matthew M Hsieh2, Xiongce Zhao3
1Campus of Haematology Franco and Piera Cutino, AOOR Villa Sofia-V. Cervello, 90142 Palermo, Italy. rdm83@hotmail.it.

In sickle cell disease (SCD), hydroxyurea (HU) treatment decreases the number of vaso-occlusive crisis (VOC) and acute chest syndrome (ACS) by increasing fetal hemoglobin (HbF). Data are lacking regarding the frequency of HU dose modification or whether sub-therapeutic doses (<15 mg/kg/day) are beneficial. We reviewed the medical records of 140 patients from 2010 to 2014. The laboratory parameters and SCD complications were compared between the first and last visits based on HU use. Fifty patients (36%) never took HU or suspended HU ("no HU" group). Among patients taking <15 mg/kg/day HU on their first visit, half remained at the same dose, and the other half increased to ≥15 mg/kg/day. Among patients taking ≥15 mg/kg/day, 17% decreased to <15 mg/kg/day, and 83% stayed at ≥15 mg/kg/day. The "no HU" group had fewer episodes of VOC and ACS. Both HU treatment groups had a reduction in both complications (p < 0.0001). This improvement was observed in all SCD phenotypes. The white blood cell (WBC) counts were found to be lower, and HbF increased in both HU groups (p = 0.004, 0.001). The maximal HbF response to HU in HbS/β⁺-thalassemia was 20%, similar to those observed for HbSS (19%) and HbS/β⁰-thalassemia (22%). HbS/β⁺-thalassemia could have a similar disease severity as HbSS or HbS/β⁰-thalassemia. Patients with HbS/β⁰-thalassemia or HbS/β⁺-thalassemia phenotypes responded to HU.
In sickle cell disease (SCD), hydroxyurea (HU) treatment decreases the number of vaso-occlusive crisis (VOC) and acute chest syndrome (ACS) by increasing fetal hemoglobin (HbF). Data are lacking regarding the frequency of HU dose modification or whether sub-therapeutic doses (<15 mg/kg/day) are beneficial. We reviewed the medical records of 140 patients from 2010 to 2014. The laboratory parameters and SCD complications were compared between the first and last visits based on HU use. Fifty patients (36%) never took HU or suspended HU ("no HU" group). Among patients taking <15 mg/kg/day HU on their first visit, half remained at the same dose, and the other half increased to ≥15 mg/kg/day. Among patients taking ≥15 mg/kg/day, 17% decreased to <15 mg/kg/day, and 83% stayed at ≥15 mg/kg/day. The "no HU" group had fewer episodes of VOC and ACS. Both HU treatment groups had a reduction in both complications (p < 0.0001). This improvement was observed in all SCD phenotypes. The white blood cell (WBC) counts were found to be lower, and HbF increased in both HU groups (p = 0.004, 0.001). The maximal HbF response to HU in HbS/β⁺-thalassemia was 20%, similar to those observed for HbSS (19%) and HbS/β⁰-thalassemia (22%). HbS/β⁺-thalassemia could have a similar disease severity as HbSS or HbS/β⁰-thalassemia. Patients with HbS/β⁰-thalassemia or HbS/β⁺-thalassemia phenotypes responded to HU.
More Related Videos

Related Concept Videos
 01:25
Benefits of Self-Esteem
 01:23
Chronic Pharyngitis
Etiology
It often arises from persistent viral or bacterial infections affecting sinuses and tonsils.
Additional contributing factors include inadequate dental hygiene, mouth breathing, recurring tonsillitis, allergic rhinitis, laryngopharyngeal reflux, and exposure to smoke, chemicals, and other environmental pollutants. Allergic reactions to pollen, mold, and pet dander, chronic cough, excessive voice usage,...
 01:18
Additional Routes of Drug Administration
Administering drugs via inhalation allows for the direct delivery of gaseous, volatile substances or droplets to different parts of the respiratory tract. One of the advantages of the inhalation route is the rapid absorption of drugs into the circulatory system, which is possible because of the large surface area of...
 01:18
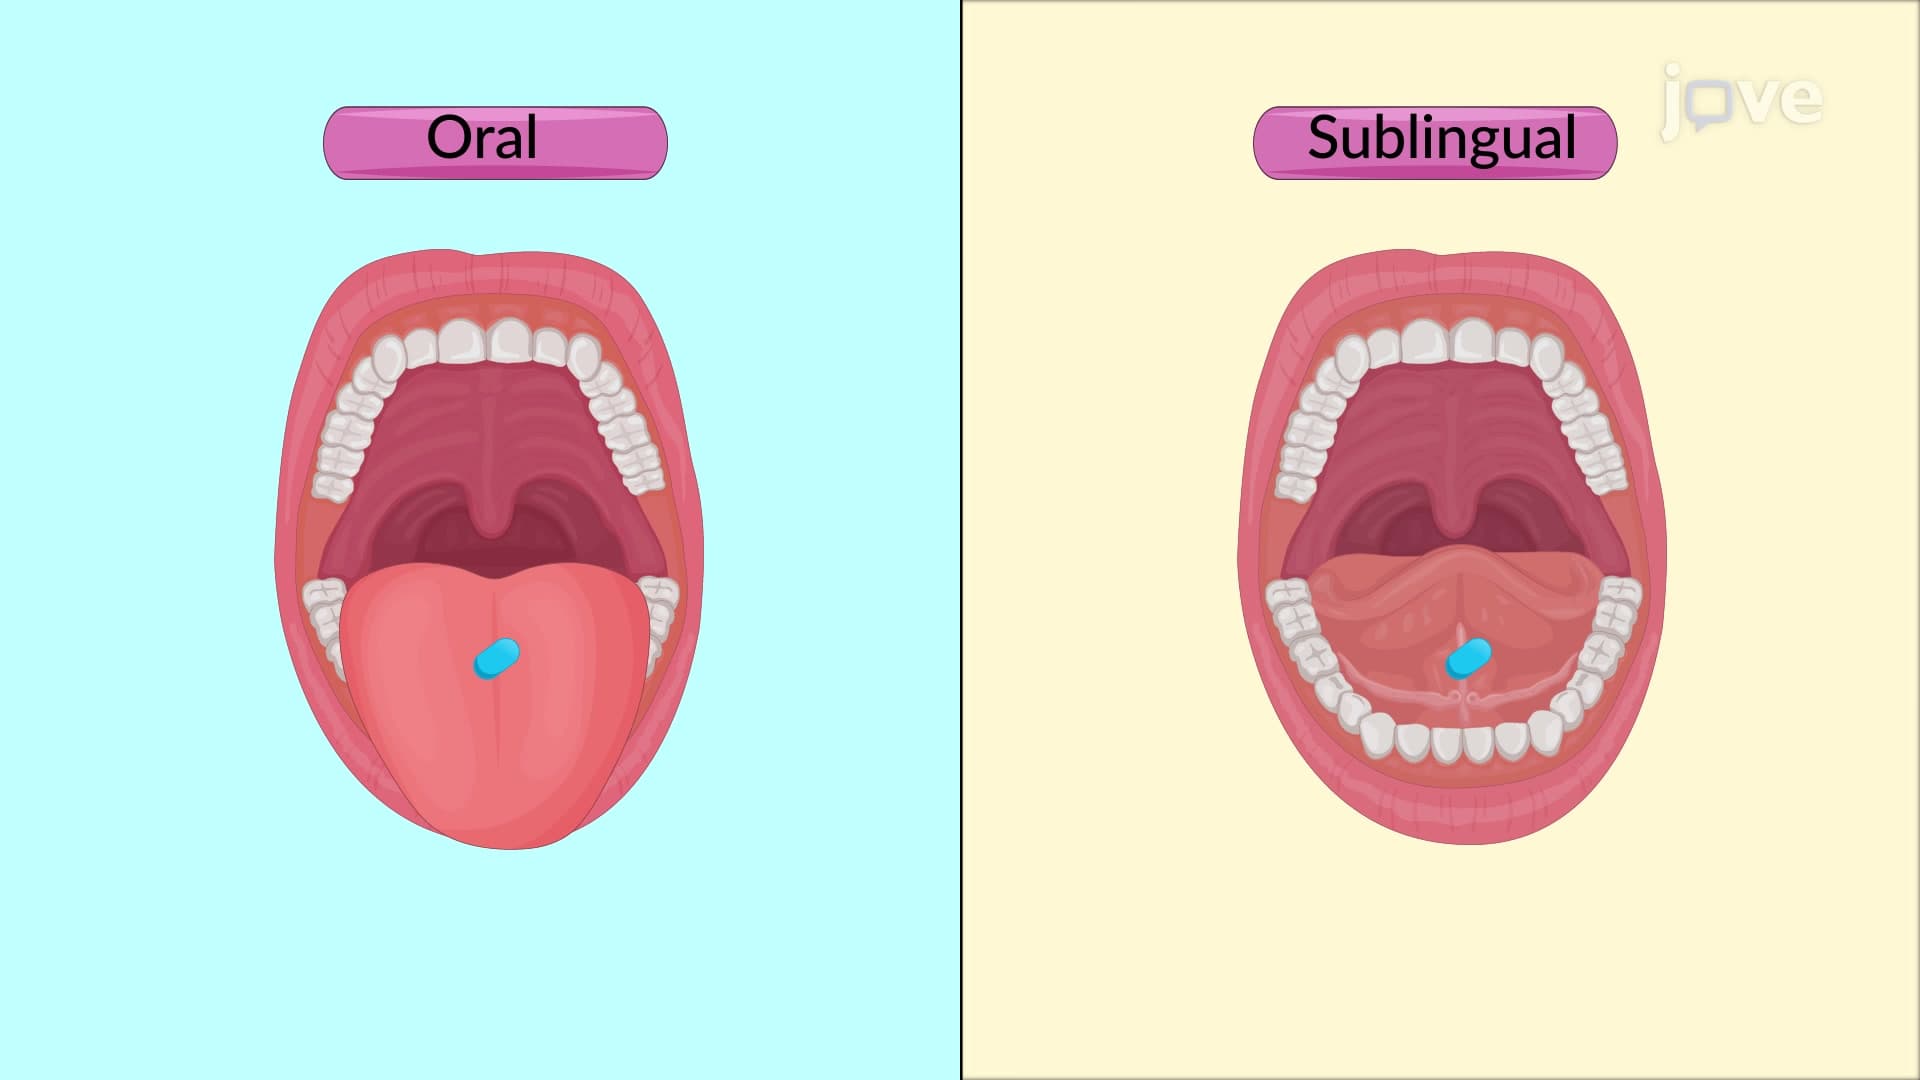
Routes of Drug Administration: Enteral
Enteral administration involves drug administration via the mouth in two ways: orally or sublingually.
Unlike sublingually drugs, drugs that are taken orally pass through the gastrointestinal (GI) tract and get metabolized by the liver. Once metabolized, the drug is absorbed into the systemic circulation, reaching different body parts via the bloodstream. However, while passing through the stomach,...
 01:25
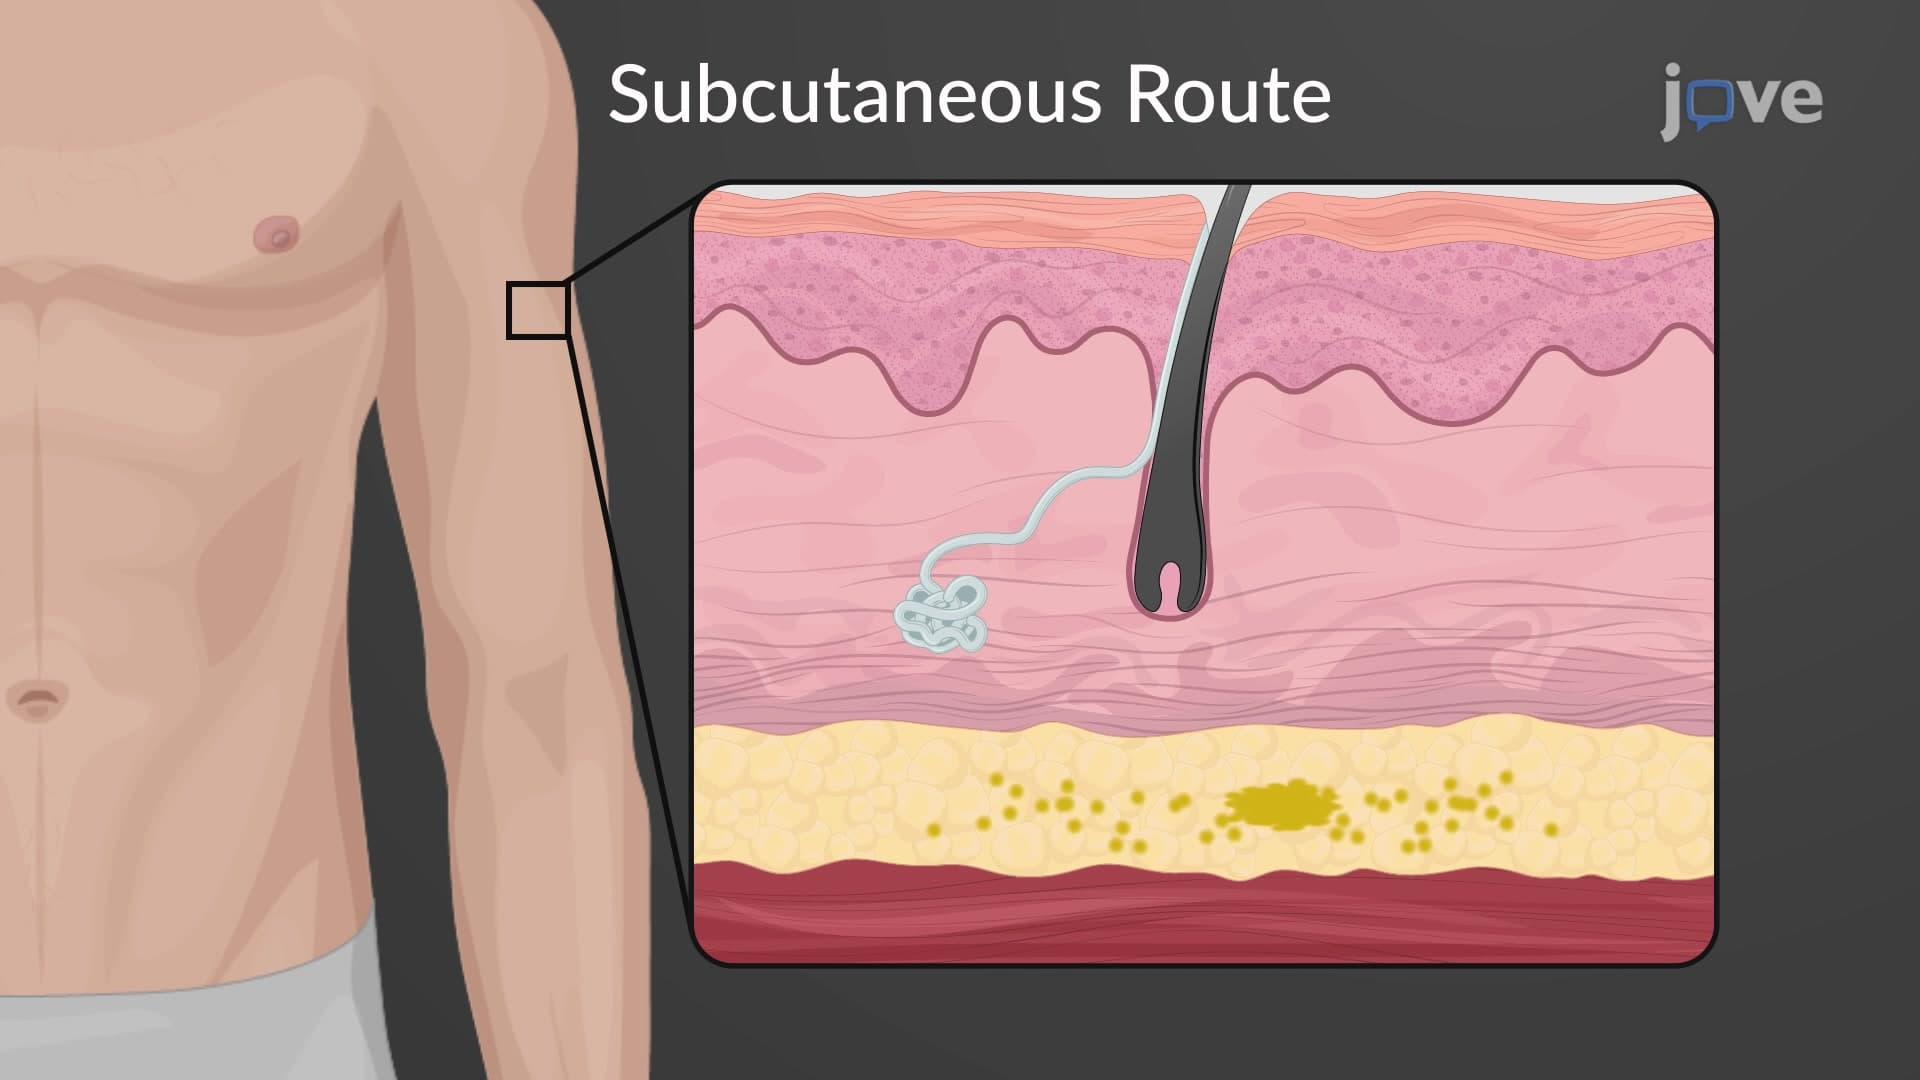
Routes of Drug Administration: Parenteral
The intravenous route (IV) of drug administration can be further categorized into two types. The bolus injection administers the entire dose rapidly, while an intravenous infusion slowly delivers smaller doses steadily.
The IV route is often...
 01:22
Routes of Drug Administration: Overview
Enteral administration refers to drugs absorbed through the gastrointestinal tract. They can be swallowed (perorally), placed under the tongue (sublingually), or on the inner lining of the cheeks (buccally). Perorally administered drugs take time to be absorbed and have a slower onset of action. The rectal route is another form of enteral administration, which allows for...