
Recurrent pituitary abscess: case report and review of the literature
Raluca Maria Furnica1, Julie Lelotte2, Thierry Duprez3
1Departments of Endocrinology, Pathology, and NeuroradiologyUniversité catholique de Louvain, Cliniques Universitaires Saint-Luc, Brussels, Belgium.

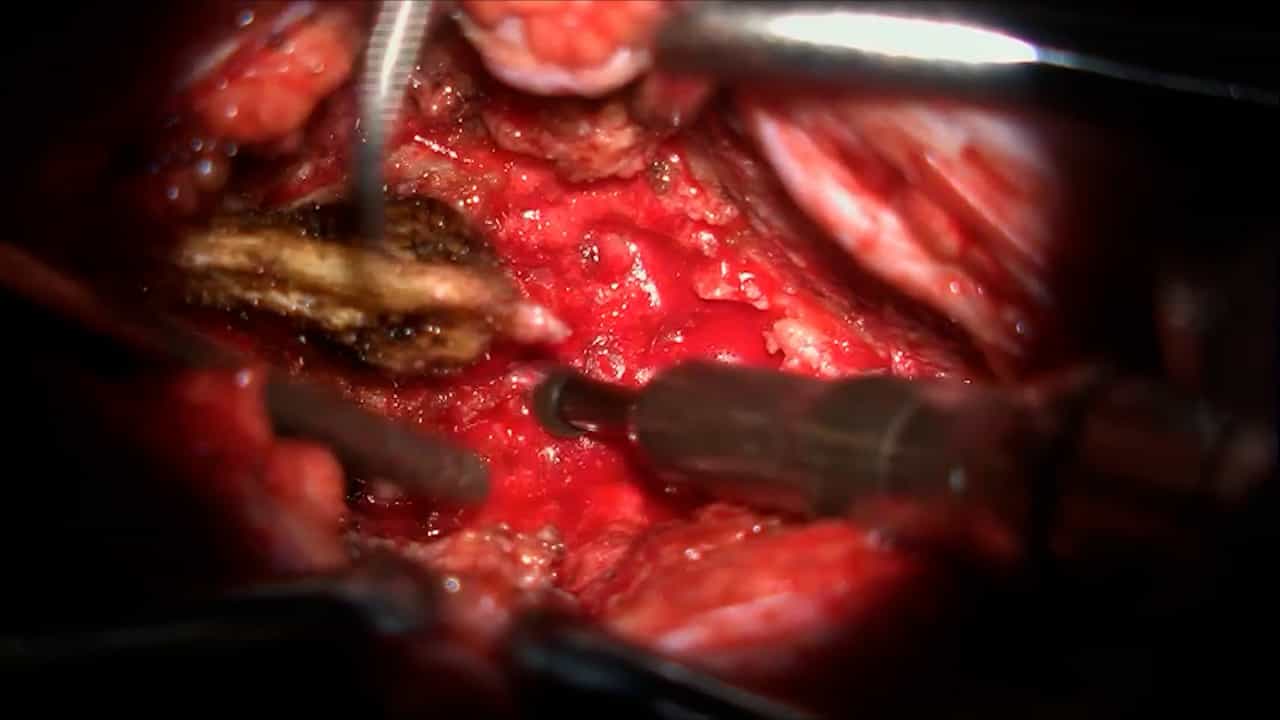
A 26-year-old woman presented with severe postpartum headaches. Magnetic resonance imaging (MRI) revealed a symmetric, heterogeneous enlargement of the pituitary gland. Three months later, she developed central diabetes insipidus. A diagnosis of postpartum hypophysitis was suspected and corticosteroids were prescribed. Six months later, the pituitary mass showed further enlargement and characteristics of a necrotic abscess with a peripheral shell and infiltration of the hypothalamus. Transsphenoidal surgery was performed, disclosing a pus-filled cavity which was drained. No bacterial growth was observed, except a single positive blood culture for Staphylococcus aureus, considered at that time as a potential contaminant. A short antibiotic course was, however, administered together with hormonal substitution for panhypopituitarism. Four months after her discharge, severe headaches recurred. Pituitary MRI was suggestive of a persistent inflammatory mass of the sellar region. She underwent a new transsphenoidal resection of a residual abscess. At that time, the sellar aspiration fluid was positive for Staphylococcus aureus and she was treated with antibiotics for 6 weeks, after which she had complete resolution of her infection. The possibility of a pituitary abscess, although rare, should be kept in mind during evaluation for a necrotic inflammatory pituitary mass with severe headaches and hormonal deficiencies.
A 26-year-old woman presented with severe postpartum headaches. Magnetic resonance imaging (MRI) revealed a symmetric, heterogeneous enlargement of the pituitary gland. Three months later, she developed central diabetes insipidus. A diagnosis of postpartum hypophysitis was suspected and corticosteroids were prescribed. Six months later, the pituitary mass showed further enlargement and characteristics of a necrotic abscess with a peripheral shell and infiltration of the hypothalamus. Transsphenoidal surgery was performed, disclosing a pus-filled cavity which was drained. No bacterial growth was observed, except a single positive blood culture for Staphylococcus aureus, considered at that time as a potential contaminant. A short antibiotic course was, however, administered together with hormonal substitution for panhypopituitarism. Four months after her discharge, severe headaches recurred. Pituitary MRI was suggestive of a persistent inflammatory mass of the sellar region. She underwent a new transsphenoidal resection of a residual abscess. At that time, the sellar aspiration fluid was positive for Staphylococcus aureus and she was treated with antibiotics for 6 weeks, after which she had complete resolution of her infection. The possibility of a pituitary abscess, although rare, should be kept in mind during evaluation for a necrotic inflammatory pituitary mass with severe headaches and hormonal deficiencies.
Learning Points:
The possibility of a pituitary abscess, although rare, should be kept in mind during evaluation for a necrotic inflammatory pituitary mass with severe headaches and hormonal deficiencies.In a significant proportion of cases no pathogenic organism can be isolated.A close follow-up is necessary given the risk of recurrence and the high rate of postoperative pituitary deficiencies.
More Related Videos


Related Concept Videos
 01:37
Hypothalamic-Pituitary Axis
 01:27
Hormones of the Pituitary Gland
The most abundantly secreted hormone from the anterior lobe is the growth hormone, which controls overall growth by...
 01:17
The Pituitary Gland
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:24
Data Reporting and Recording