Related Experiment Video
Updated: Feb 13, 2026

Assessment of Thermal Damage from Robot-Drilled Craniotomy for Cranial Window Surgery in Mice
Published on: November 11, 2022
Early postnatal cranial vault reduction and fixation surgery for severe hydrocephalic macrocephaly
Rajiv R Iyer1, Carolyn M Carey1,2, S Alex Rottgers3
11Institute for Neuroscience and Brain Protection.

Insights
Cranial vault reduction and fixation (CVRF) combined with cerebrospinal fluid (CSF) shunting in infants with severe hydrocephalus and macrocephaly can improve cosmetic outcomes and simplify treatment. This approach may reduce the risk of severe cranial deformities associated with shunting alone.
Area of Science:
- Neurosurgery
- Pediatric Surgery
- Craniofacial Surgery
Background:
- Severe neonatal hydrocephalus with extreme macrocephaly often requires early cerebrospinal fluid (CSF) diversion.
- Early CSF diversion can lead to significant cranial deformities due to overdrainage and overlapping cranial plates.
- Subsequent extensive cranial vault remodeling is challenging, with high morbidity and mortality rates.
Purpose of the Study:
- To evaluate the institutional experience of managing extreme neonatal hydrocephalus with CSF diversion, with and without cranial vault reduction and fixation (CVRF).
- To assess the efficacy of early CVRF in improving cosmesis and simplifying management in infants with severe hydrocephalic macrocephaly.
- To compare outcomes between infants treated with shunting alone versus shunting combined with CVRF.
Main Methods:
- Retrospective review of infants (head circumference > 49 cm) treated between 2005 and 2017 with ventriculoperitoneal shunting, with or without CVRF.
- Data collected included patient demographics, hydrocephalus etiology, CVRF type, follow-up duration, craniometric measurements, operative details, and complications.
- Developmental and esthetic outcomes were assessed using standardized questionnaires and photographic imaging.
Main Results:
- Eleven infants underwent CSF shunting; 5 with shunting alone and 6 with shunting and CVRF.
- The mean calvarial vault volume reduction with CVRF was 44.5%.
- Shunting alone resulted in severe cranial deformities in 3 of 5 patients, whereas CVRF combined with shunting led to only 1 poor cosmetic outcome in 6 patients. Mortality occurred in 2 patients (shunting alone) and 1 patient (shunting and CVRF).
Conclusions:
- CVRF in the neonatal period, combined with CSF shunting, can simplify management for severe hydrocephalic macrocephaly.
- This combined approach leads to favorable cosmetic outcomes, as reported by families.
- Early CVRF may mitigate the severe cranial deformities often seen with CSF diversion alone in this patient population.
Abstract:
OBJECTIVE Infants with severe hydrocephalus and extreme macrocephaly typically undergo CSF diversion early in life, which can result in significant cranial deformity due to CSF overdrainage. In this scenario, overlap of the cranial plates can precede the development of secondary synostosis and/or severe, permanent cranial deformity. As a result, extensive cranial vault remodeling is sometimes undertaken later in life, which is often challenging and has been associated with mortality and a high morbidity rate. The authors have previously described a technique for early postnatal cranial vault reduction and fixation (CVRF), in which the calvarial bones are stabilized using absorbable fixation plates in the neonatal period, in an attempt to facilitate patient positioning, simplify hydrocephalus management, and improve cosmesis. Here, the authors describe their institutional experience managing patients with extreme neonatal hydrocephalus with CSF diversion, with and without CVRF, over the past 12 years. METHODS The authors retrospectively reviewed the charts of infants with extreme hydrocephalus (head circumference > 49 cm) treated at their children's hospital with ventriculoperitoneal shunting, with or without CVRF, between 2005 and 2017. Data collected included age, sex, etiology of hydrocephalus, type of CVRF performed (anterior, posterior, or combined), follow-up duration, orbitofrontal circumference, craniometric measurements, intraoperative blood loss, operative duration, and postoperative complications. Developmental data were collected using the third edition of the Ages and Stages Questionnaire. Photographic imaging was used to demonstrate esthetic outcomes, and family questionnaires were used to evaluate satisfaction with the esthetic outcome. RESULTS Eleven patients with extreme neonatal hydrocephalus underwent CSF shunting; 5 underwent shunting alone and 6 patients underwent shunting and CVRF. For patients who underwent shunting and CVRF, the median age at CVRF was 6 days and the median interval between shunt placement and CVRF was 2.5 days. The mean extent of calvarial vault volume reduction was 44.5% (± 3.9%). The mean duration of the CVRF procedure was 108 minutes, and 5 of 6 patients required intraoperative transfusion. Of the 5 patients who underwent shunting alone, 3 developed severe cranial deformities. Of 6 patients who underwent shunting and CVRF, 1 had a poor cosmetic outcome. In the shunting-alone group, 2 patients died and 1 required extensive cranial vault correction at 10 years of age. One patient in the shunting and CVRF group also died. CONCLUSIONS CVRF in combination with CSF shunting in the neonatal period can simplify the treatment of the rare case of severe hydrocephalic macrocephaly and leads to cosmetic outcomes that are considered good by their families.
Related Concept Videos
 03:11
Oxidation-Reduction Reactions
 01:03
Fixation and Sectioning
The simplest type of preparation is the wet mount, in which the specimen is placed in a drop of liquid on the slide. A liquid specimen can be directly deposited on the slide using a dropper. Solid specimens, such as skin scraping, can be placed on the slide before adding a drop of liquid to prepare the wet mount. Sometimes the liquid is simply water, but stains are often added...
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:22
Cranial Nerves: Types Part II
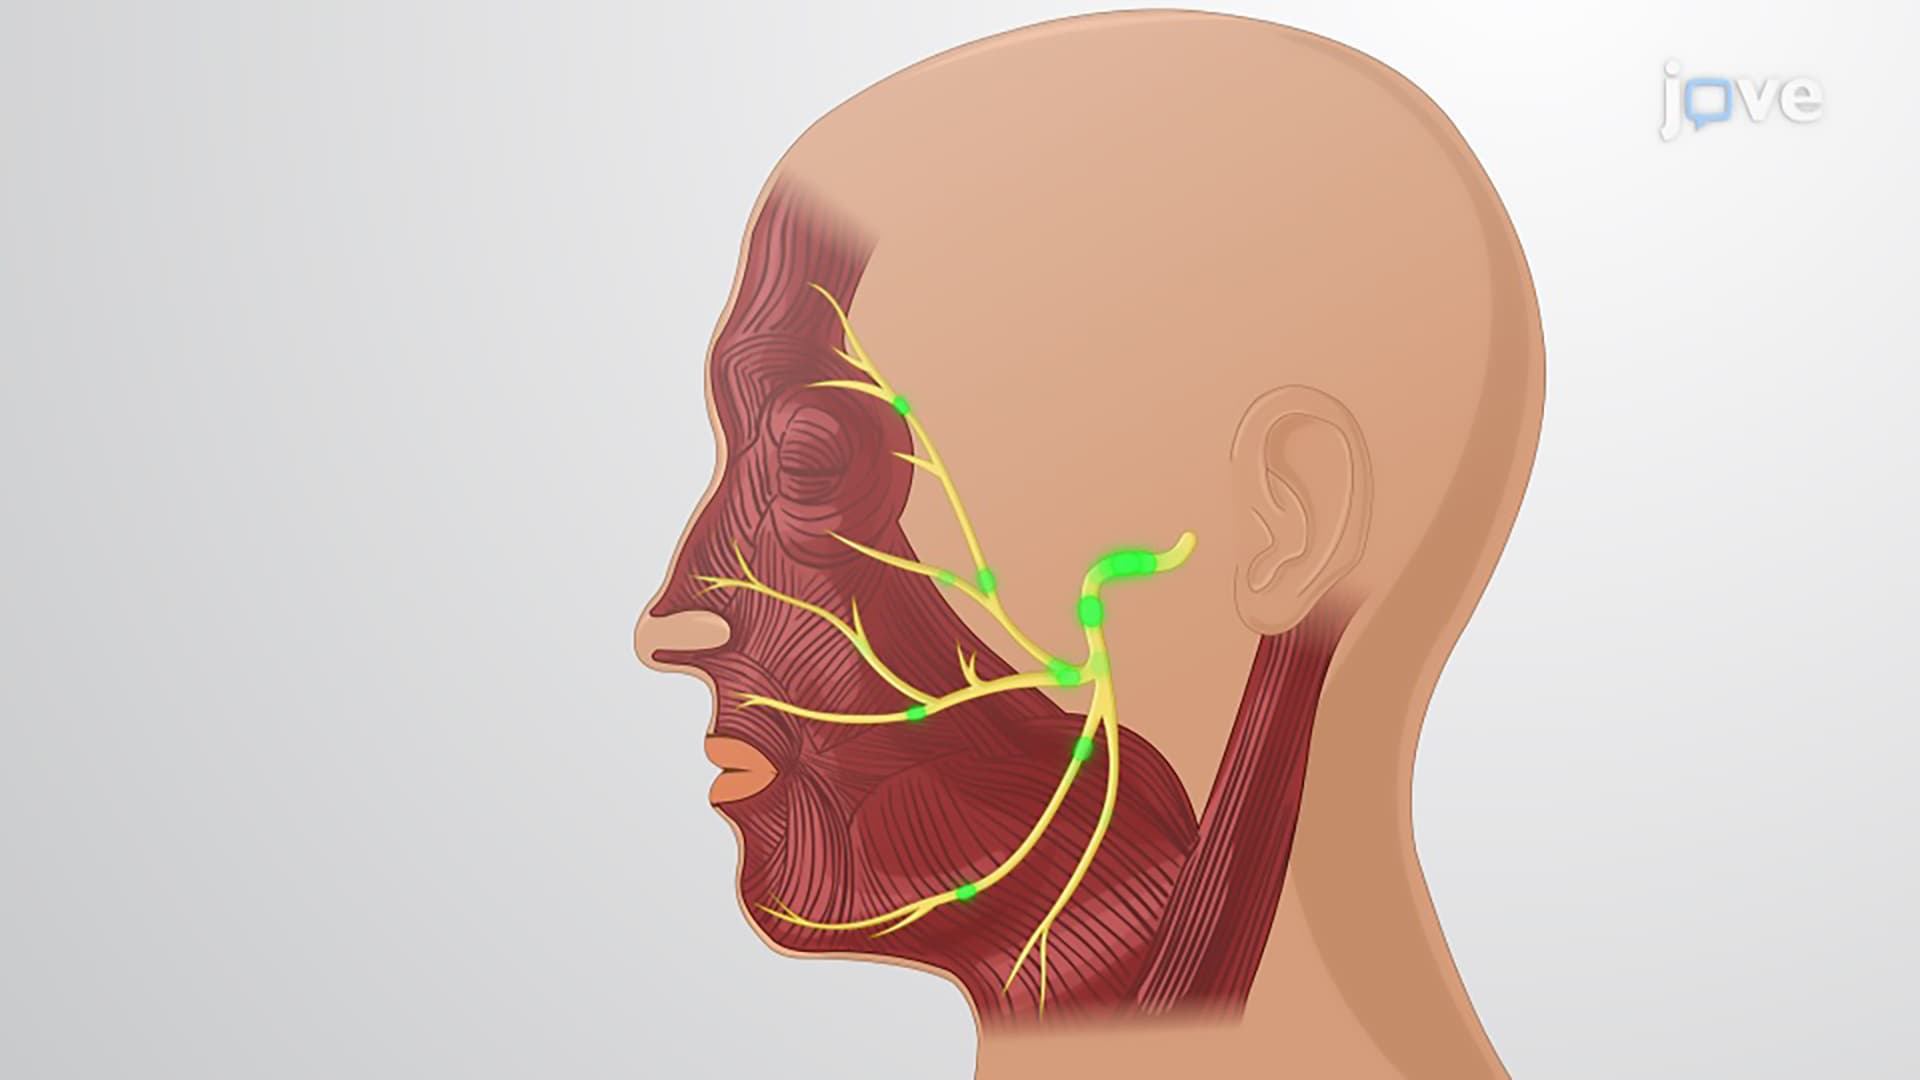
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:18
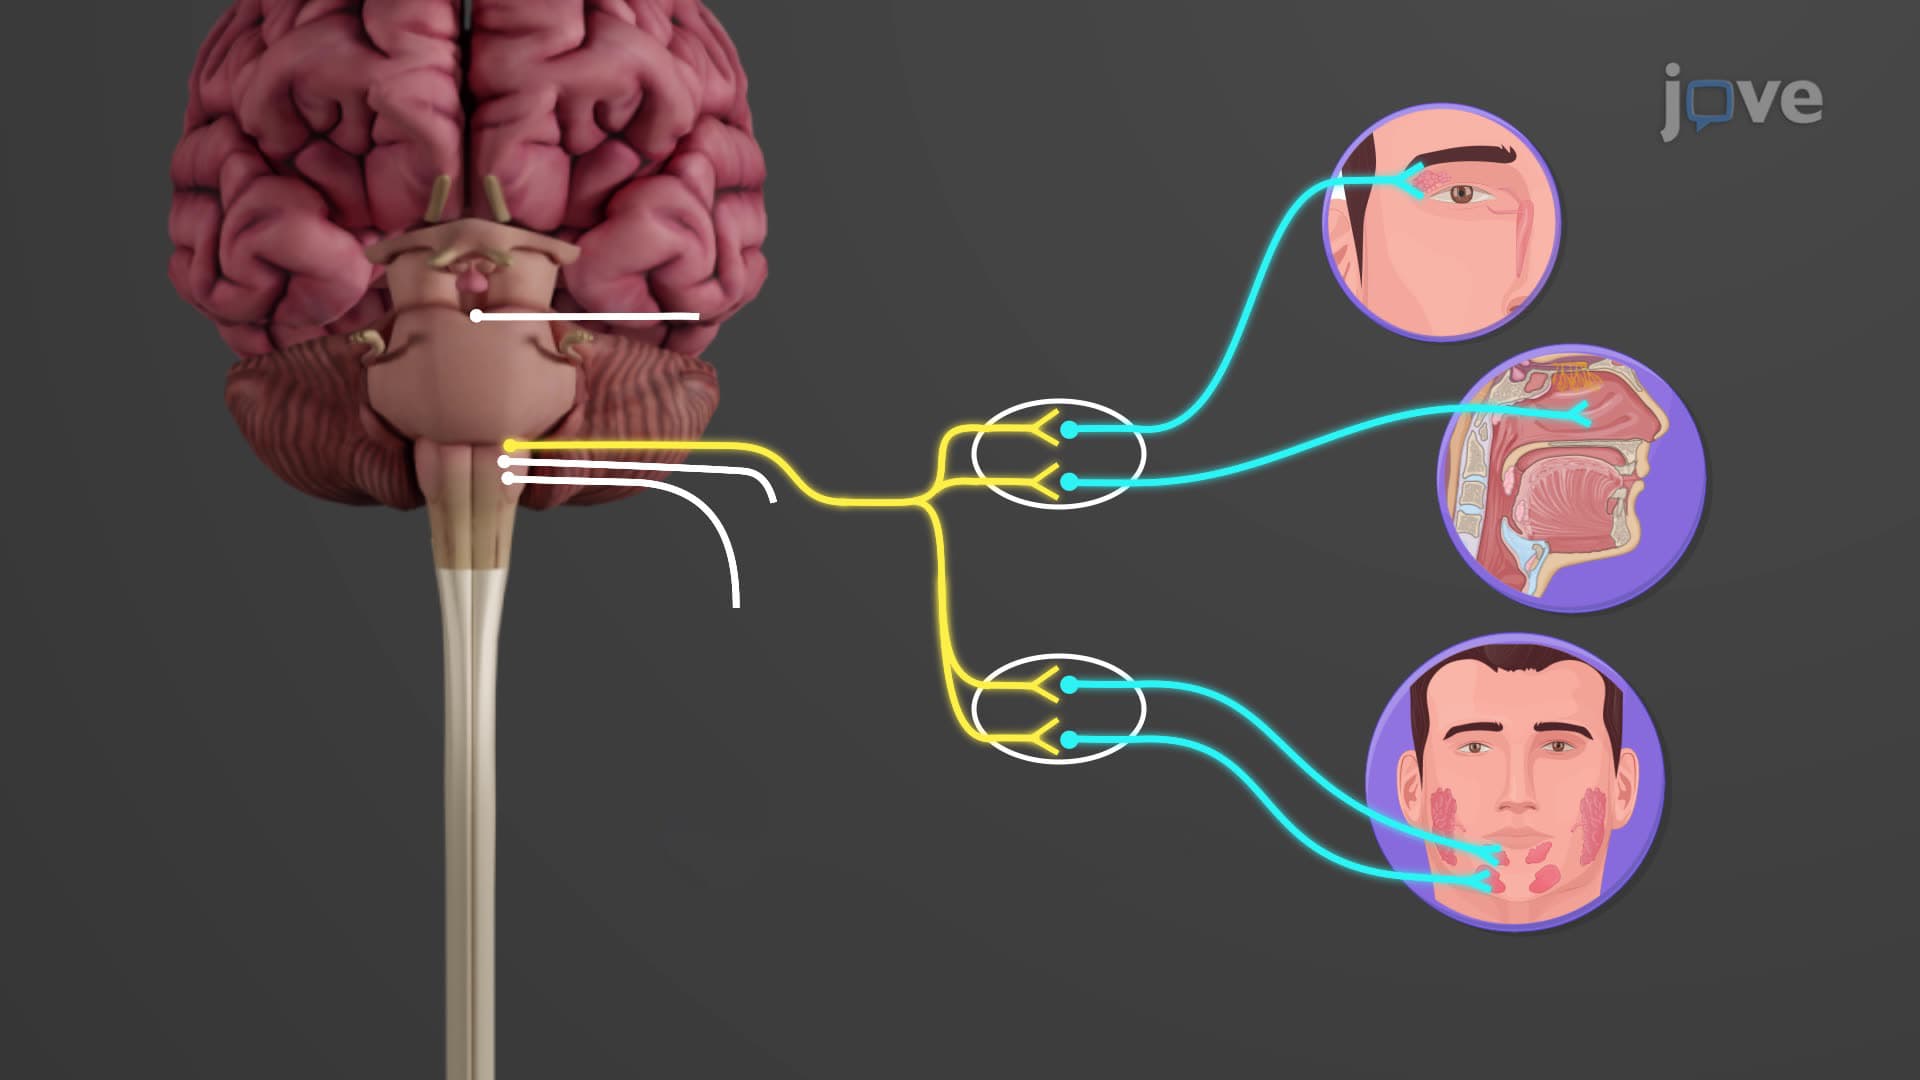
Cranial Part of Parasympathetic Division
The vagus nerve (cranial nerve X) alone accounts for approximately 75...