Related Experiment Video
Updated: Feb 13, 2026


Designing CAD/CAM Surgical Guides for Maxillary Reconstruction Using an In-house Approach
Published on: August 24, 2018
Ruptured Pseudoaneurysm of the Maxillary Artery and Its Branches Following Le Fort I Osteotomy: Evidence-Based
Michael R Bykowski1, Amber Hill, Catherine Garland
1Department of Pediatric Plastic Surgery, Children's Hospital of Pittsburgh, Pittsburgh, PA.

Background:
Although rare, pseudoaneurysms (PA) can develop following Le Fort I osteotomy and lead to life-threatening hemorrhage. However, the typical presentation of a PA following a Le Fort I osteotomy is not well characterized. Evidence-based guidelines are not currently available for evaluation of PA following Le Fort I osteotomy.
Methods:
A case report is presented of a 27-year-old man who underwent Le Fort I advancement and subsequently developed a bleeding PA. A comprehensive search of journal articles was performed using the MEDLINE/PubMed database between 1964 and April 2016. Keywords and phrases used were "(osteotomy OR craniofacial OR orthognathic) AND (pseudoaneurysm OR aneurysm OR epistaxis)." Preferred Reporting Items for Systematic Reviews and Meta- Analyses (PRISMA) guidelines were followed.
Results:
The literature search yielded 13 reports of 18 patients. All 18 patients underwent Le Fort I osteotomy and subsequently developed a delayed postoperative bleeding PA. All studies were level IV or V evidence. Twenty-eight percent (N = 5) of the cases documented "excessive" intraoperative bleeding or more than 500 mL of estimated blood loss. The average time for the first bleeding episode and time until final bleed was 17.3 ± 14.3 days (range: 3-62 days) and 27.8 ± 21.2 days following surgery (range: 6-77 days), respectively. Sixty-seven percent (N = 12) had multiple episodes of bleeding. The duration between the bleeding events averaged 10.6 (± 7.9 days) with a range of 1 to 35 days. Bleeding PA's were treated with image-guided embolization (15/18 patients; 83.3%) or ligation or clamping (3/18 patients; 16.7%).
Conclusion:
In the setting of recurrent and/or delayed postoperative epistaxis following Le Fort I osteotomy, surgeons should maintain a high clinical suspicion for PA. Ruptured PA's are often preceded by multiple episodes of progressively worsening epistaxis. Based on the presented case report and pooled data from the literature, angiography is recommended to evaluate for PA in the setting of recurrent epistaxis following Le Fort I osteotomy, especially within the first 4 weeks following surgery.


Related Concept Videos
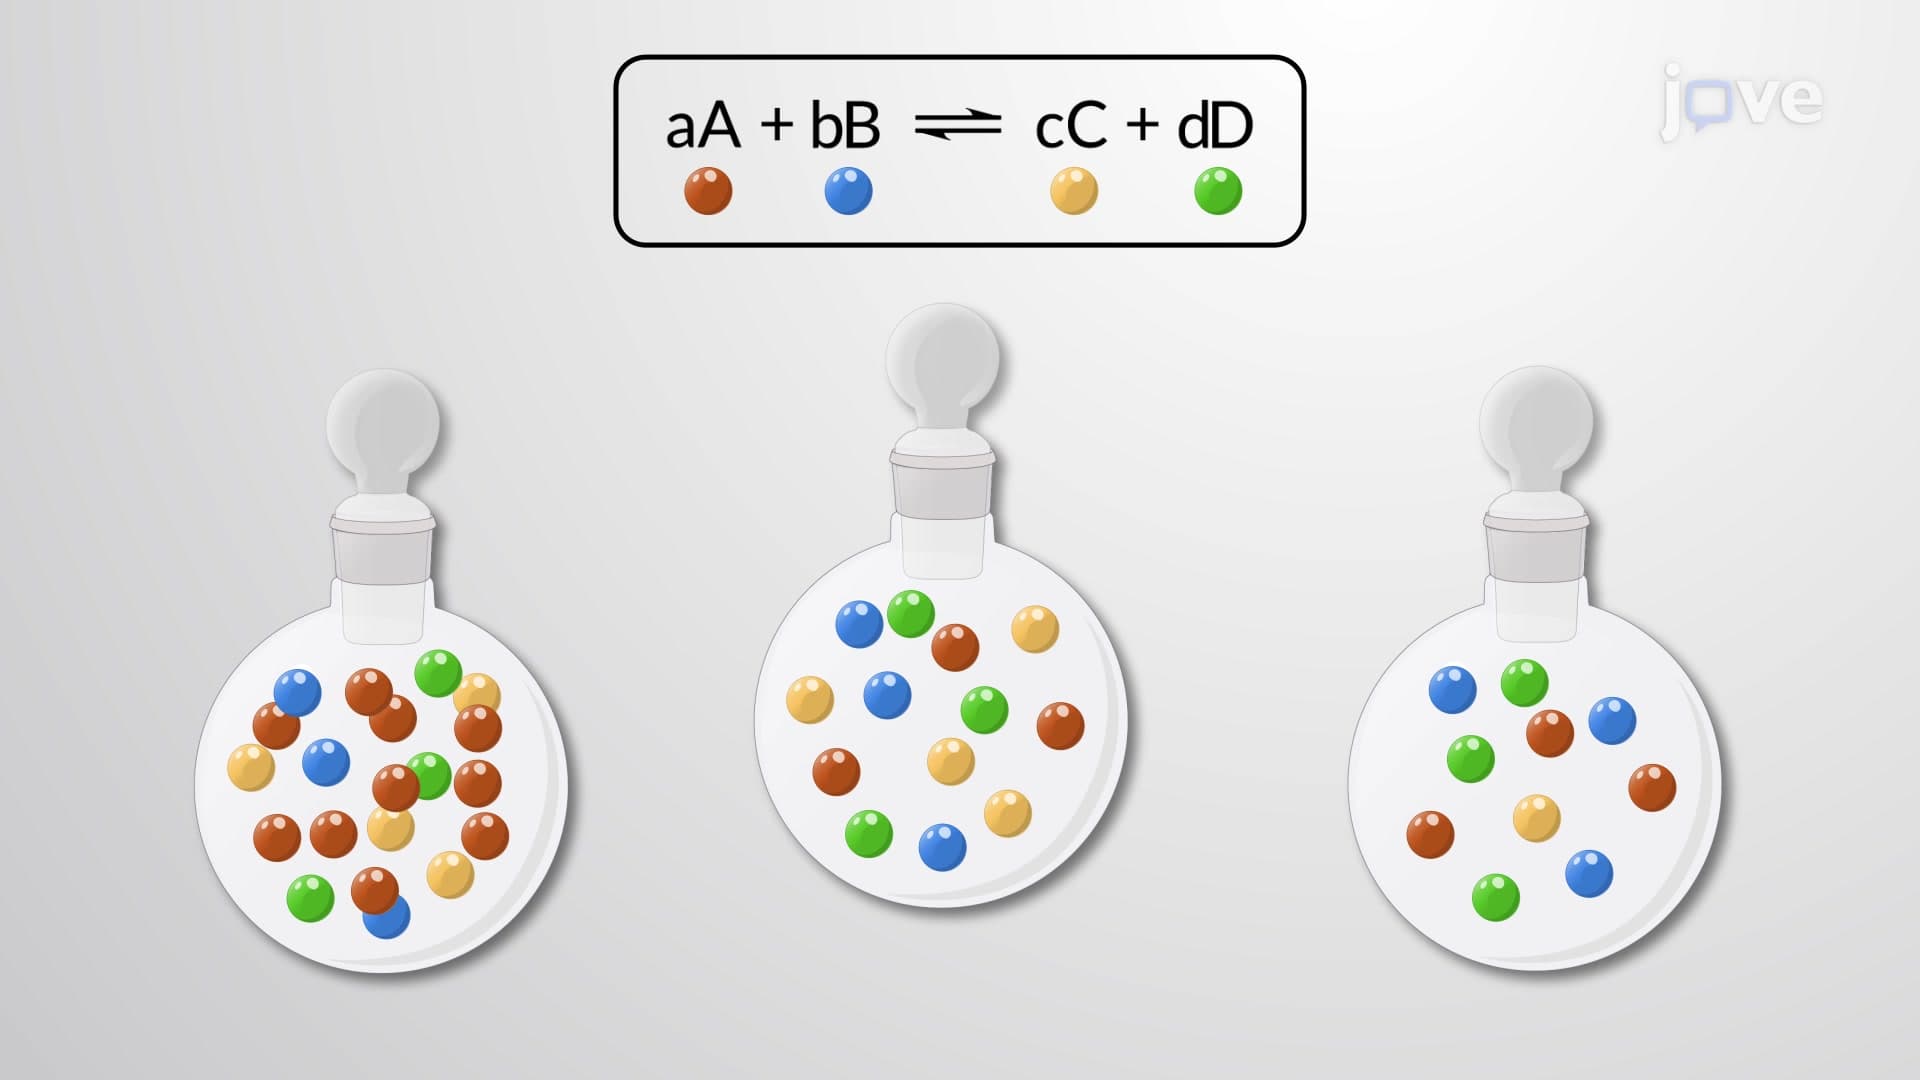 02:27
Le Chatelier's Principle: Changing Concentration
 02:55
The Evidence for Evolution
 02:19
Le Chatelier's Principle: Changing Temperature
To understand this phenomenon, consider the elementary reaction:
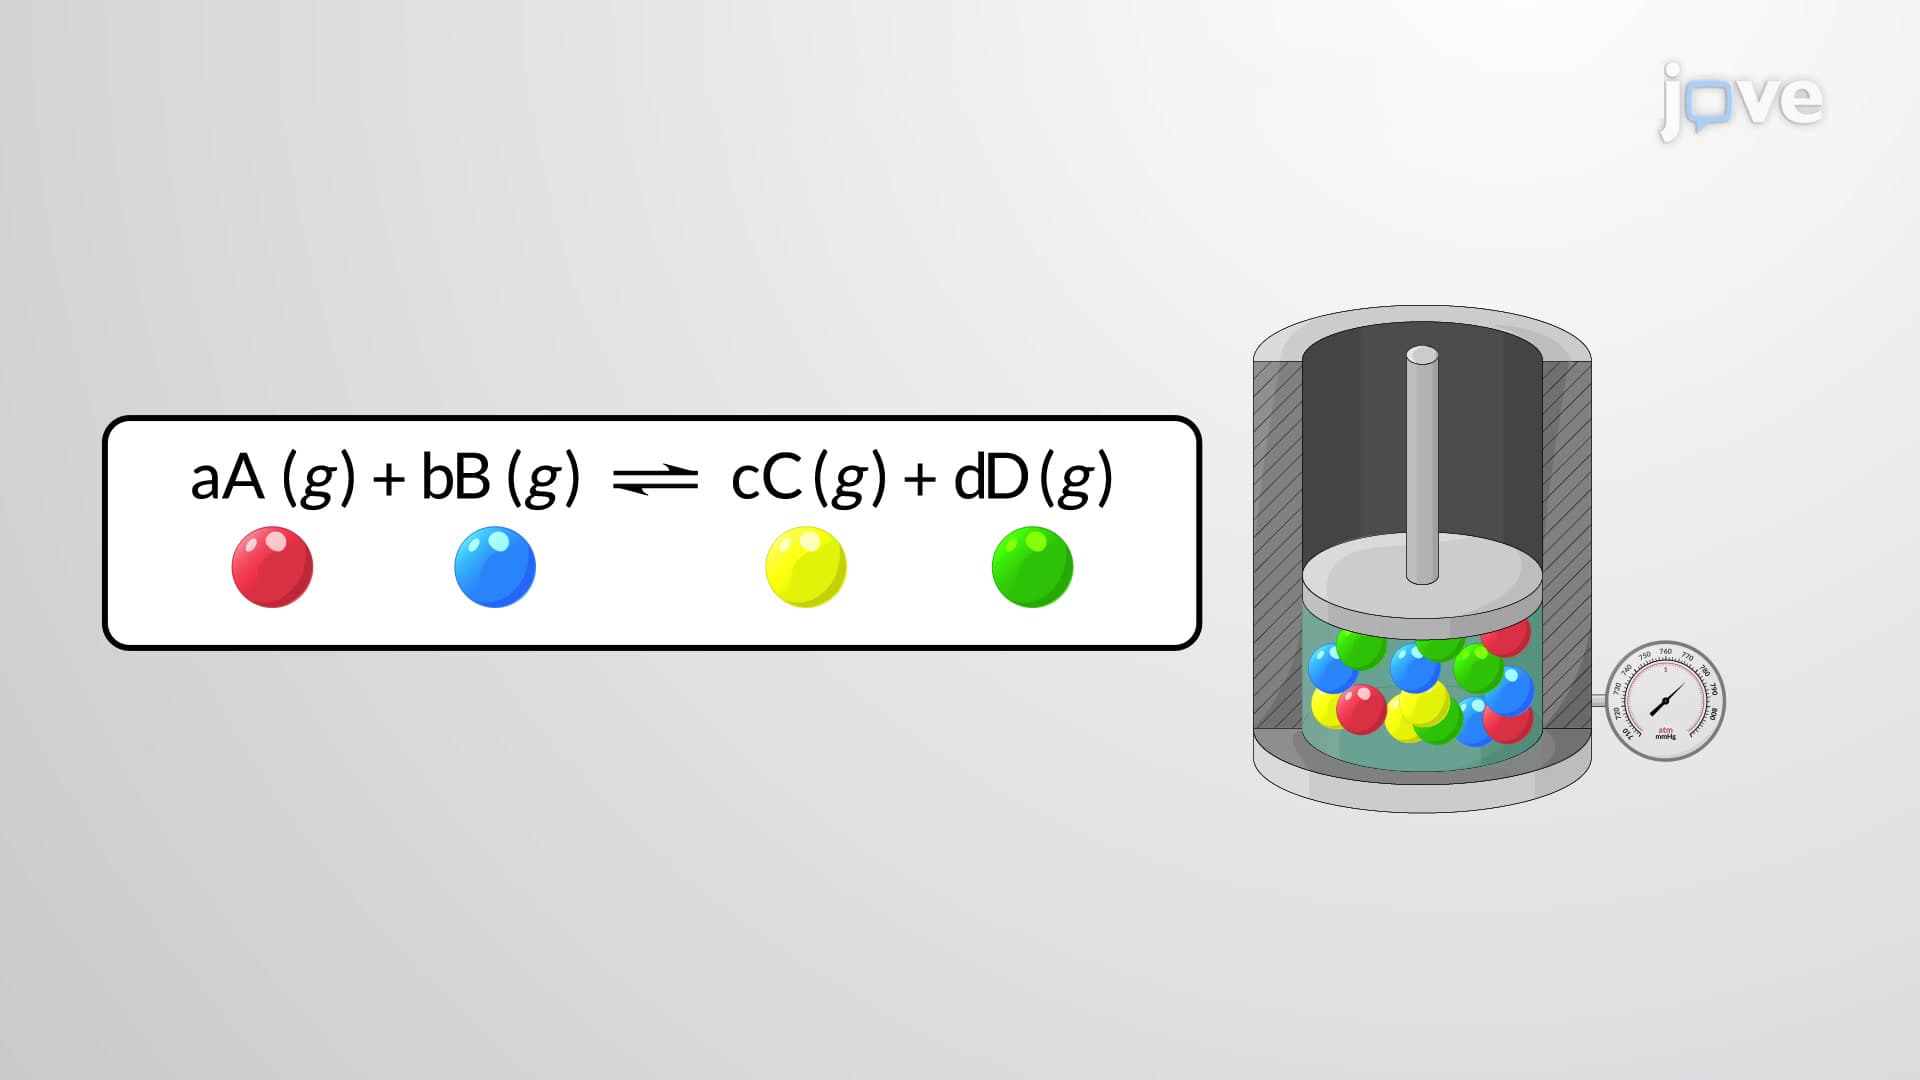 02:32
Le Chatelier's Principle: Changing Volume (Pressure)
 01:23
Guidelines for Sketching a Curve
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...