Related Experiment Video
Updated: Feb 13, 2026


Predicting Amputation using Local Circulating Mononuclear Progenitor Cells in Angioplasty-treated Patients with Critical Limb Ischemia
Published on: September 22, 2020
Ethnic minorities with critical limb ischemia derive equal amputation risk reduction from autologous cell therapy
S Keisin Wang1, Linden A Green1, Ashley R Gutwein1
1Division of Vascular Surgery, Indiana University School of Medicine, Indianapolis, Ind.

Objective:
Ethnic minorities (nonwhites) with critical limb ischemia (CLI) have historically performed worse compared with whites with regard to major amputation risk reduction and amputation-free survival (AFS) after peripheral vascular intervention. This post hoc analysis was completed to determine whether this precedent also extended to treatment of CLI without a suitable revascularization option with intramuscular injections of concentrated bone marrow aspirate (cBMA).
Methods:
The treatment arm of the randomized, double-blind, multicenter MarrowStim PAD Kit for the Treatment of Critical Limb Ischemia in Subjects with Severe Peripheral Arterial Disease (MOBILE) trial was stratified by ethnicity and evaluated for demographics, comorbidities, and outcomes. The primary and therapeutic end point was 1-year AFS and major amputation, respectively. Noninferiority analysis was performed with the margin set at historically reported hazard ratios.
Results:
Thirty-seven minority (African American, Hispanic, other) CLI patients (9 placebo, 28 cBMA) with no suitable revascularization option were randomized to cBMA or placebo at a 3:1 ratio during the MOBILE trial. At 1-year follow-up for the treatment group, overall AFS was 80%. Of the 28 minority patients randomized to cBMA intervention, an 89% AFS rate was observed compared with 77% in whites. Specifically, 22 of 24 (92%) African Americans survived amputation free at 1-year follow-up. Noninferiority testing confirmed no difference between whites and the ethnic minority treated with cBMA with respect to major amputation reduction; however, noninferiority could not be confirmed with regard to AFS. No significant differences favoring whites treated with cBMA were noted in the secondary end points of vascular quality of life, limb pain, ankle-brachial index, toe-brachial index, transcutaneous oximetry, and 6-minute walk testing.
Conclusions:
This post hoc analysis of the MOBILE trial demonstrates noninferiority of cBMA intervention in minorities with no-option CLI for the therapeutic end point of major amputation prevention. cBMA represents a novel treatment paradigm and should be explored for minorities with poor revascularization options who face impending amputation secondary to progressive CLI.
Related Concept Videos
 01:25
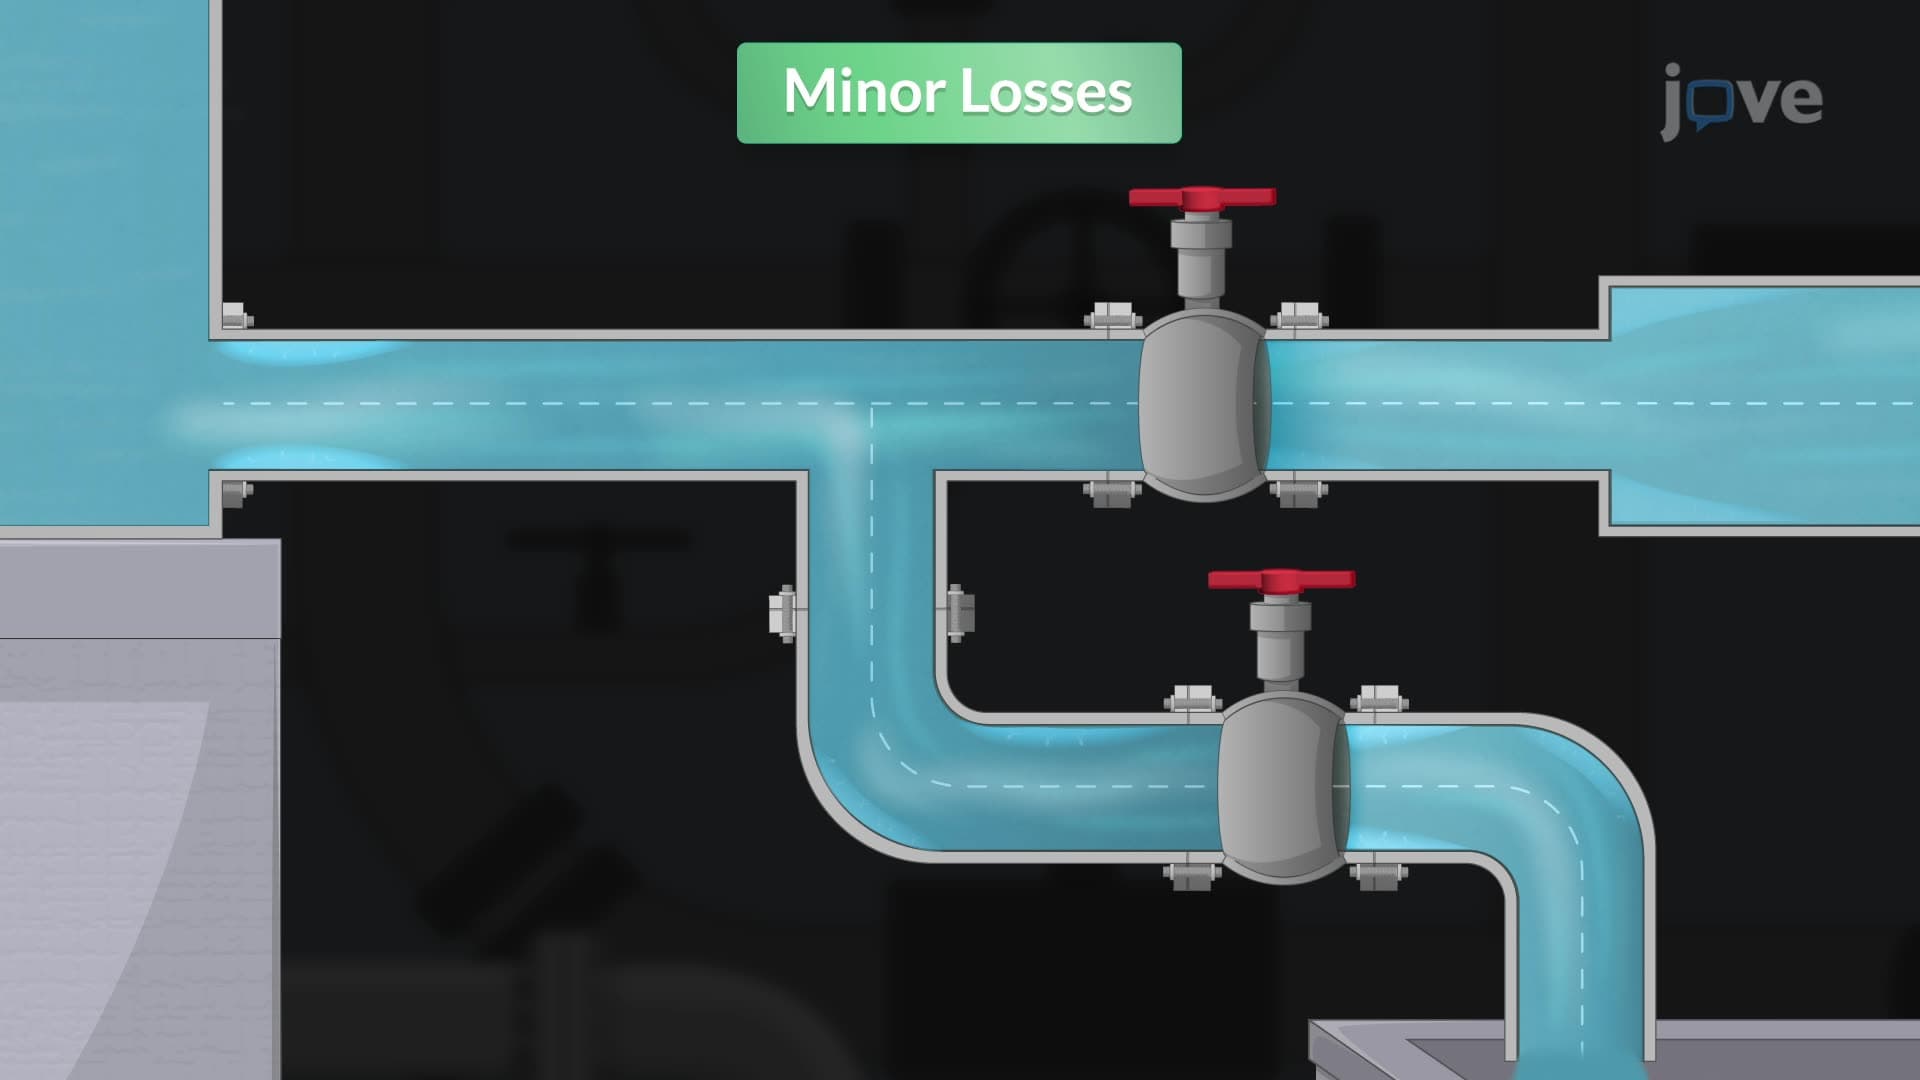
Minor Losses in Pipes
Valves play a significant role in generating minor losses by obstructing or redirecting the fluid flow. When a valve is closed or partially closed, it restricts the flow...
 01:15
One-Way ANOVA: Equal Sample Sizes
Different sample means can result in different values for the variance estimate: variance between samples. This is because the variance between samples is calculated as the product of the sample size and the variance between the...
 01:27
Ethnic Identity within a Larger Culture
 01:30
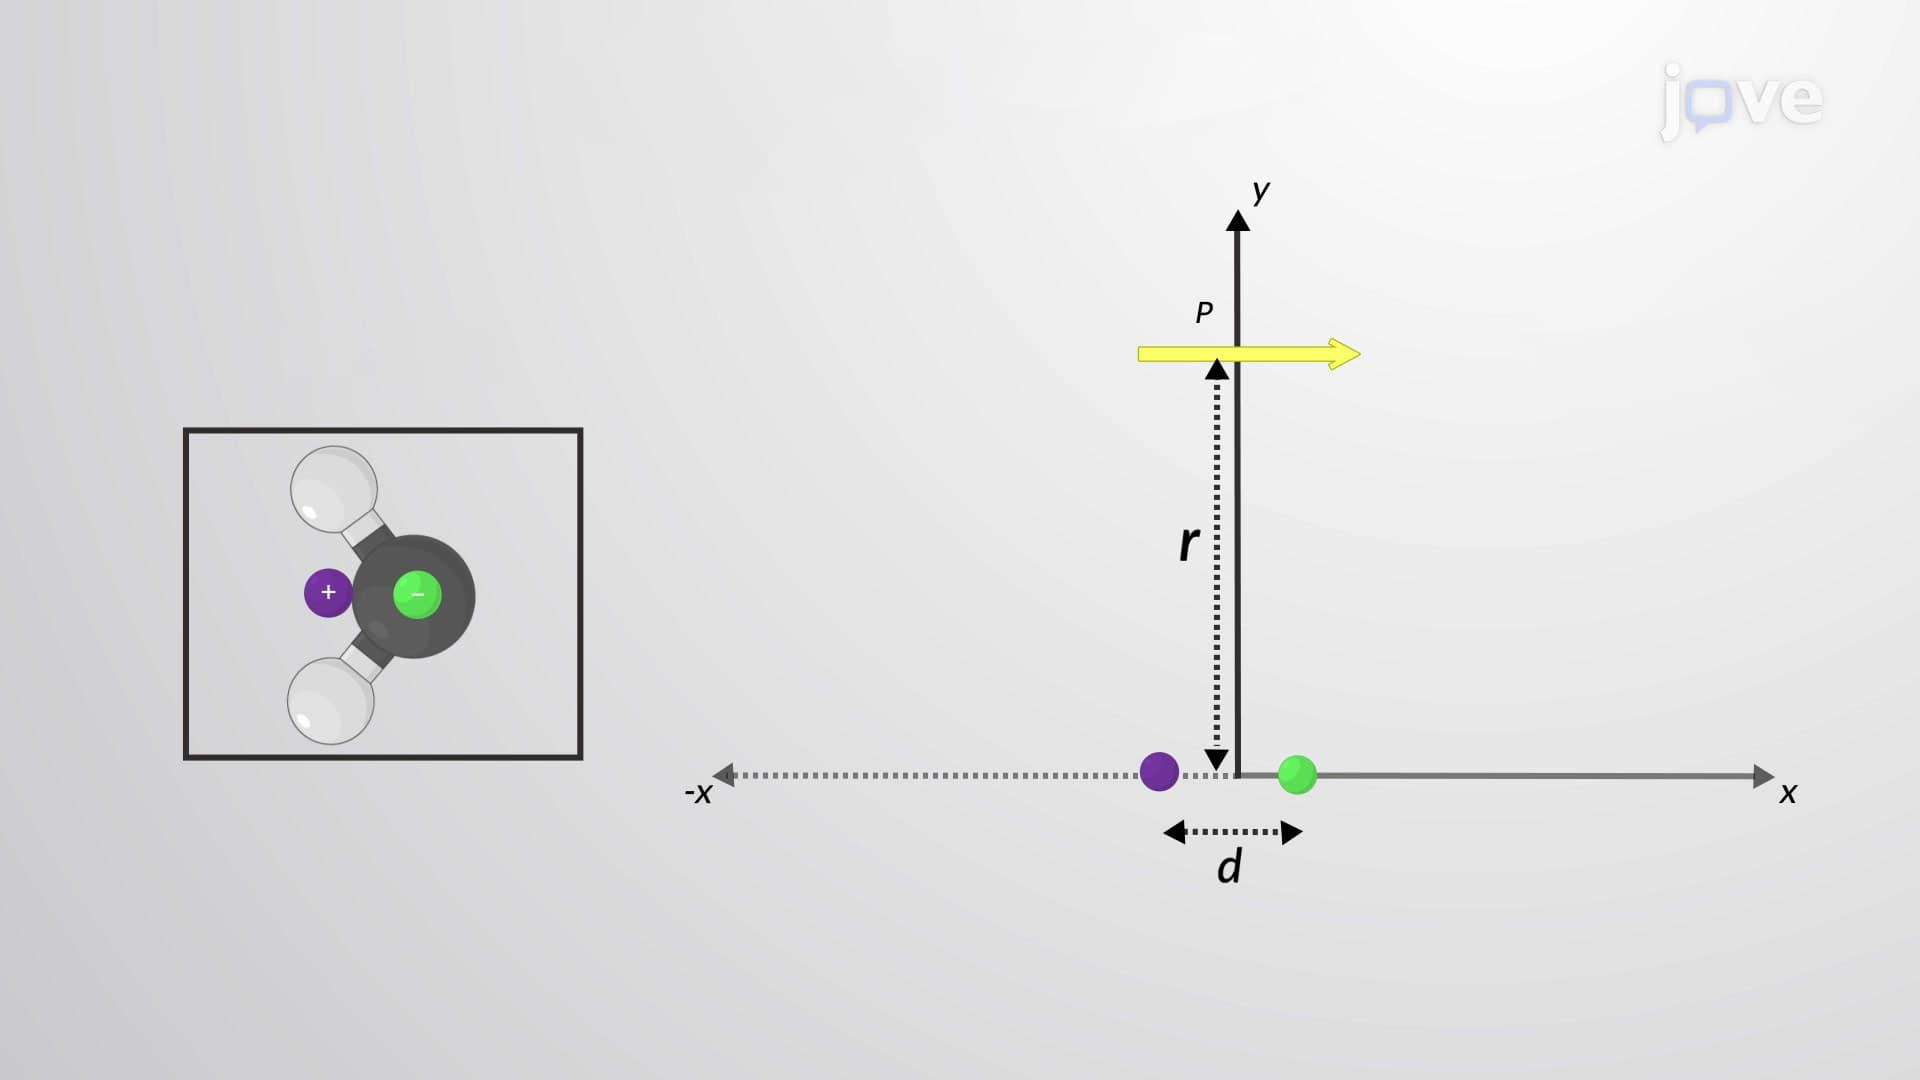
Electric Field of Two Equal and Opposite Charges
A separation of the positive and negative charges can lead to a weak, remnant effect of the positive and negative charges. The expectation is that the more the distance between the positive and...
 03:11
Oxidation-Reduction Reactions
 01:16
Critical Region, Critical Values and Significance Level
In hypothesis testing, a sample statistic is converted to a test statistic using z, t, or chi-square distribution. A critical region is an area under the curve in probability distributions demarcated by the critical value. When the test statistic falls in this region, it suggests that the null hypothesis must be rejected. As this region contains all those values of the...