Related Experiment Video
Updated: Feb 13, 2026

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Reconstruction of diabetic lower leg and foot soft tissue defects using thoracodorsal artery perforator chimeric
Il Hoon Sung1, Dong Woo Jang2, Se Wan Kim3
1Department of Orthopaedic Surgery, College of Medicine, Hanyang University, Seoul, Korea.

Background:
Reconstruction of complicated diabetic lower leg and foot defects involving multiple tissue components remains a challenge. The purpose of this report is to introduce thoracodorsal artery perforator (TDAP) chimeric flaps for reconstructing diabetic lower leg and foot soft tissue defects.
Patients And Methods:
Between April 2010 and August 2016, 17 patients with multiple diabetic lower leg and foot defects underwent reconstruction with TDAP chimeric flaps. Nine were women and the mean age of the patients was 57.7 years (range 35-73 years). One patient had 3 separate defects, 14 patients had 2 separate defects, and 2 patients had defects with dead space. The size of the defects ranged from 5 × 3 cm to 20 × 10 cm.
Results:
Fifteen patients received TDAP chimeric flaps with two components (skin and muscle components), and two received three components (skin, latissimus dorsi (LD), and serratus anterior [SA] components). The skin paddle ranged from 10 × 3 cm to 25 × 14 cm. The LD components ranged from 3 × 5 cm to 20 × 10 cm and SA components ranged from 5 × 2 cm to 8 × 7 cm. All flaps survived except for partial loss of one muscle component. Four patients suffered postoperative complications including wound disruption and infection, all of which healed conservatively. The mean follow-up was 31.3 months (range 8-60 months). Fifteen patients were able to walk, one patient walked with walker, and one patient who had amputation due to Charcot joint infection walked with prosthesis.
Conclusions:
The TDAP chimeric flap may be another option for the complicated and complex wound coverage required to reconstruct diabetic lower leg and foot soft tissue defects.
Related Concept Videos
 01:28
Muscles of the Leg that Move the Foot and Toes
Anterior Compartment
The anterior compartment includes muscles that contribute to the dorsiflexion of the foot. This compartment houses the tibialis anterior, extensor hallucis longus, and extensor digitorum longus muscles....
 01:23
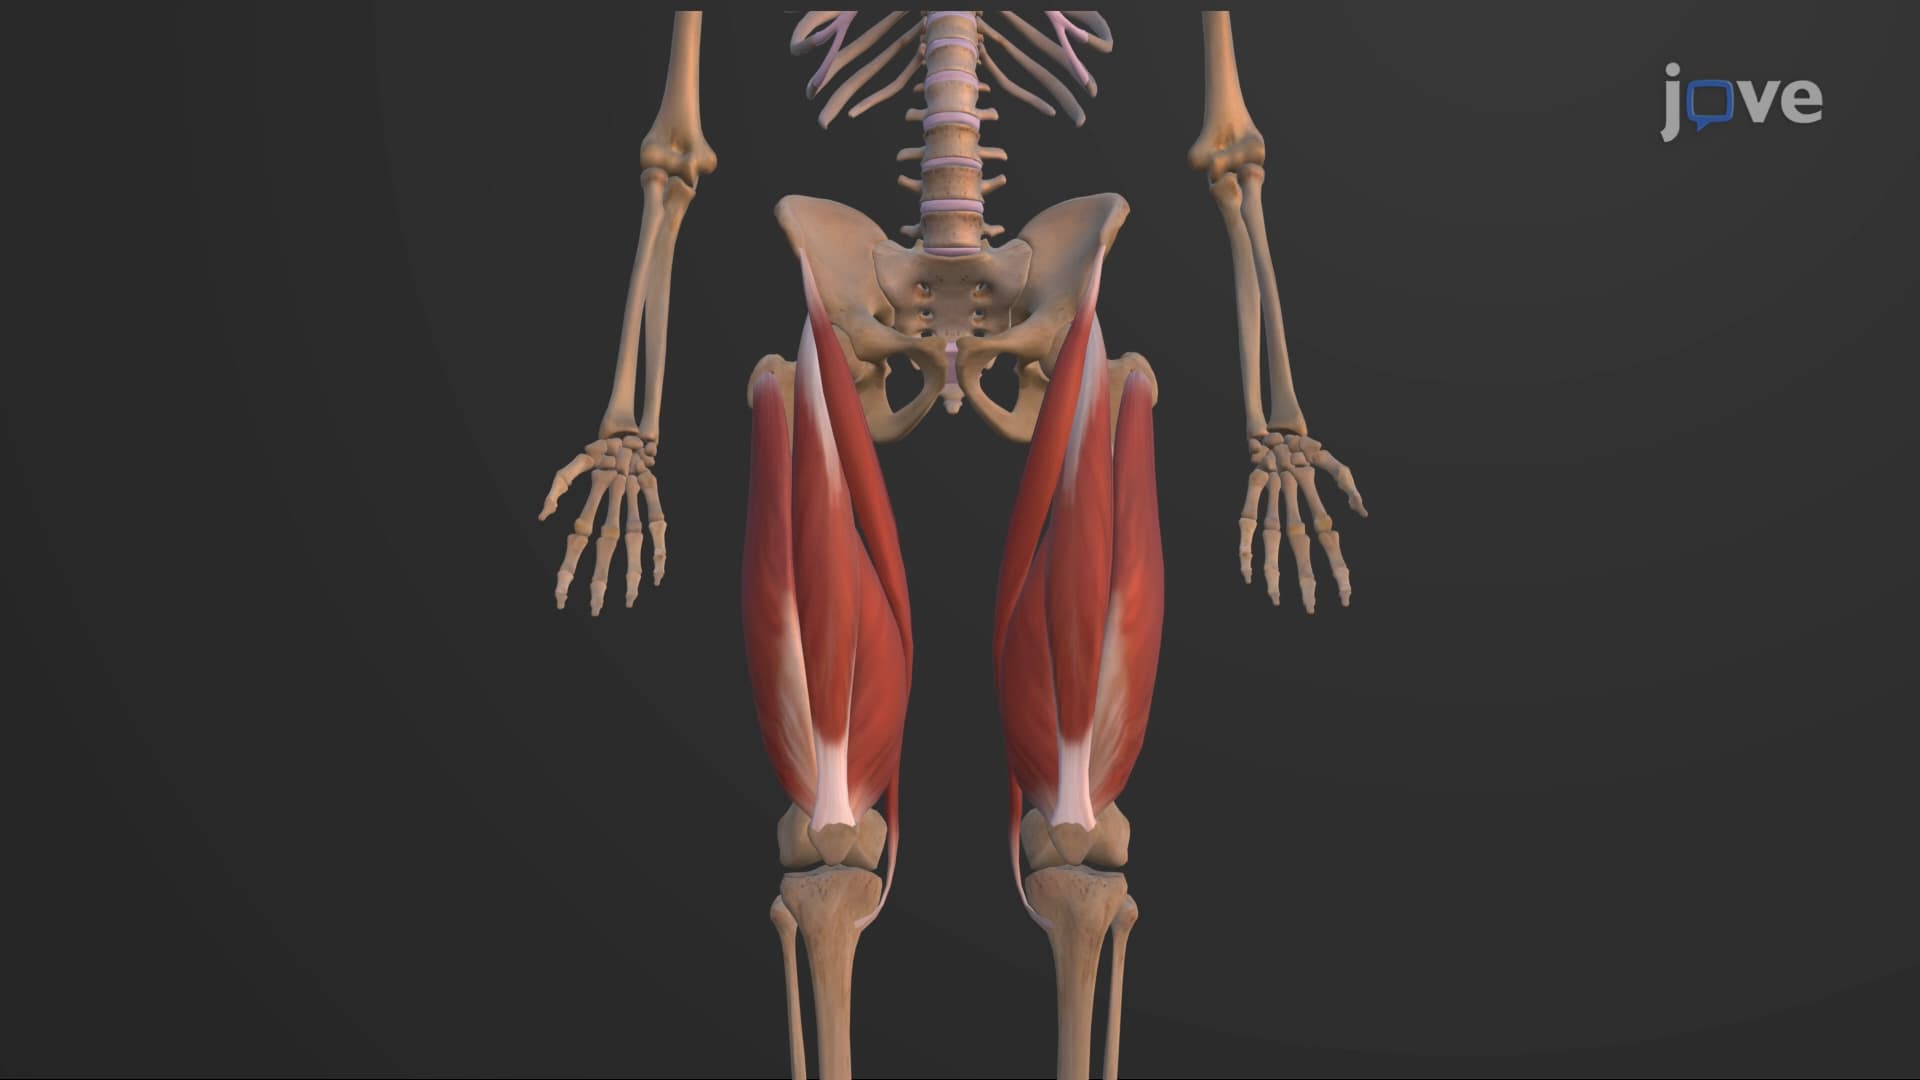
Muscles that Move the Leg
Anterior Compartment
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed...
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:23
Lumber Defects
Shakes are minor fractures that run along or across the wood's annual rings, while wane is...
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: