Related Experiment Video
Updated: Feb 13, 2026

Analyzing Oxygen Consumption Rate in Primary Cultured Mouse Neonatal Cardiomyocytes Using an Extracellular Flux Analyzer
Published on: February 13, 2019
A Device for the Quantification of Oxygen Consumption and Caloric Expenditure in the Neonatal Range
Einav Nachman1, Peter Clemensen1,2, Katheryn Santos1
1From the Department of Cardiology, Boston Children's Hospital, Boston, Massachusetts.

Insights
A new device accurately measures oxygen consumption (VO2) and energy expenditure (EE) in infants, overcoming limitations of current methods for critical care. This innovation aids in optimizing treatment for neonates and children.
Area of Science:
- Medical Devices
- Physiology
- Critical Care Medicine
Background:
- Accurate measurement of oxygen consumption (VO2) and energy expenditure (EE) is crucial for optimizing critical care, especially in infants.
- Current methods struggle to quantify VO2 and EE in infants due to physiological factors like low tidal volume and rapid respiratory rates.
Purpose of the Study:
- To describe and validate a novel device designed for accurate VO2, VCO2, and EE measurements in infants.
- To address the limitations of existing technologies in pediatric critical care settings.
Main Methods:
- A customized device was developed, quantifying inspiratory volume and gas concentrations (O2, CO2) with a specialized algorithm for precise time alignment.
- Validation involved in vitro testing with a certified gas mixture, in vivo studies in ventilated rats, and clinical evaluation in 14 intubated neonates and infants.
- Measurements were compared against reference standards (simulated data, Douglas bag collections) using linear regression and Bland-Altman analysis.
Main Results:
- In vitro and rodent studies demonstrated high accuracy for VO2, VCO2, and EE measurements.
- Clinical validation in infants showed the device accurately measured VO2 (bias +0.22 ± 0.87 mL/kg/min) and VCO2 (bias +0.33 ± 0.82 mL/kg/min) compared to the Douglas method.
- Measurement errors were within acceptable clinical limits, with minimal deviations even in challenging conditions like tachypnea or hyperoxia.
Conclusions:
- The developed device provides accurate VO2, VCO2, and EE measurements suitable for clinical decision-making in neonates and infants.
- It overcomes previous technological limitations, enabling better patient management in pediatric critical care.
- The device's accuracy is maintained even with rapid respiratory rates and varying oxygen concentrations.
Background:
The accurate measurement of oxygen consumption (VO2) and energy expenditure (EE) may be helpful to optimize the treatment of critically ill patients. However, current techniques are limited in their ability to accurately quantify these end points in infants due to a low VO2, low tidal volume, and rapid respiratory rate. This study describes and validates a new device intended to perform in this size range.
Methods:
We created a customized device that quantifies inspiratory volume using a pneumotachometer and concentrations of oxygen and carbon dioxide gas in the inspiratory and expiratory limbs. We created a customized algorithm to achieve precise time alignment of these measures, incorporating bias flow and compliance factors. The device was validated in 3 ways. First, we infused a certified gas mixture (50% oxygen/50% carbon dioxide) into an artificial lung circuit, comparing measured with simulated VO2 and carbon dioxide production (VCO2) within a matrix of varying tidal volume (4-20 mL), respiratory rate (20-80 bpm), and fraction of inspired oxygen (0.21-0.8). Second, VO2, VCO2, and EE were measured in Sprague Dawley rats under mechanical ventilation and were compared to simultaneous Douglas bag collections. Third, the device was studied on n = 14 intubated, spontaneously breathing neonates and infants, comparing measured values to Douglas measurements. In all cases, we assessed for difference between the device and reference standard by linear regression and Bland-Altman analysis.
Results:
In vitro, the mean ± standard deviation difference between the measured and reference standard VO2 was +0.04 ± 1.10 (95% limits of agreement, -2.11 to +2.20) mL/min and VCO2 was +0.26 ± 0.31 (-0.36 to +0.89) mL/min; differences were similar at each respiratory rate and tidal volume measured, but higher at fraction of inspired oxygen of 0.8 than at 0.7 or lower. In rodents, the mean difference was -0.20 ± 0.55 (-1.28 to +0.89) mL/min for VO2, +0.16 ± 0.25 (-0.32 to +0.65) mL/min for VCO2, and -0.84 ± 3.29 (-7.30 to +5.61) kcal/d for EE. In infants, the mean VO2 was 9.0 ± 2.5 mL/kg/min by Douglas method and was accurately measured by the device (bias, +0.22 ± 0.87 [-1.49 to +1.93] mL/kg/min). The average VCO2 was 8.1 ± 2.3 mL/kg/min, and the device exhibited a bias of +0.33 ± 0.82 (-1.27 to +1.94) mL/kg/min. Mean bias was +2.56% ± 11.60% of the reading for VO2 and +4.25% ± 11.20% of the reading for VCO2; among 56 replicates, 6 measurements fell outside of the 20% error range, and no patient had >1 of 4 replicates with a >20% error in either VO2 or VCO2.
Conclusions:
This device can measure VO2, VCO2, and EE with sufficient accuracy for clinical decision-making within the neonatal and pediatric size range, including in the setting of tachypnea or hyperoxia.


Related Concept Videos
 00:59
Range
15.9; 16.1; 15.2; 14.8; 15.8; 15.9; 16.0; 15.5
Measurements of the amount of soda in a 16-ounce can vary since different subjects record these measurements or since the exact amount - 16 ounces of liquid, was not...
 01:27
¹H NMR: Long-Range Coupling
In alkenes, spin information is communicated via σ–π overlap, as seen in allylic (four-bond) and homoallylic (five-bond) couplings. These coupling interactions are stronger when the σ bond is parallel to the alkene...
 02:32
Variation: Normal Distribution, Range, and Standard Deviation
 01:13
Angle of Twist - Elastic Range
 01:13
Range Rule of Thumb to Interpret Standard Deviation
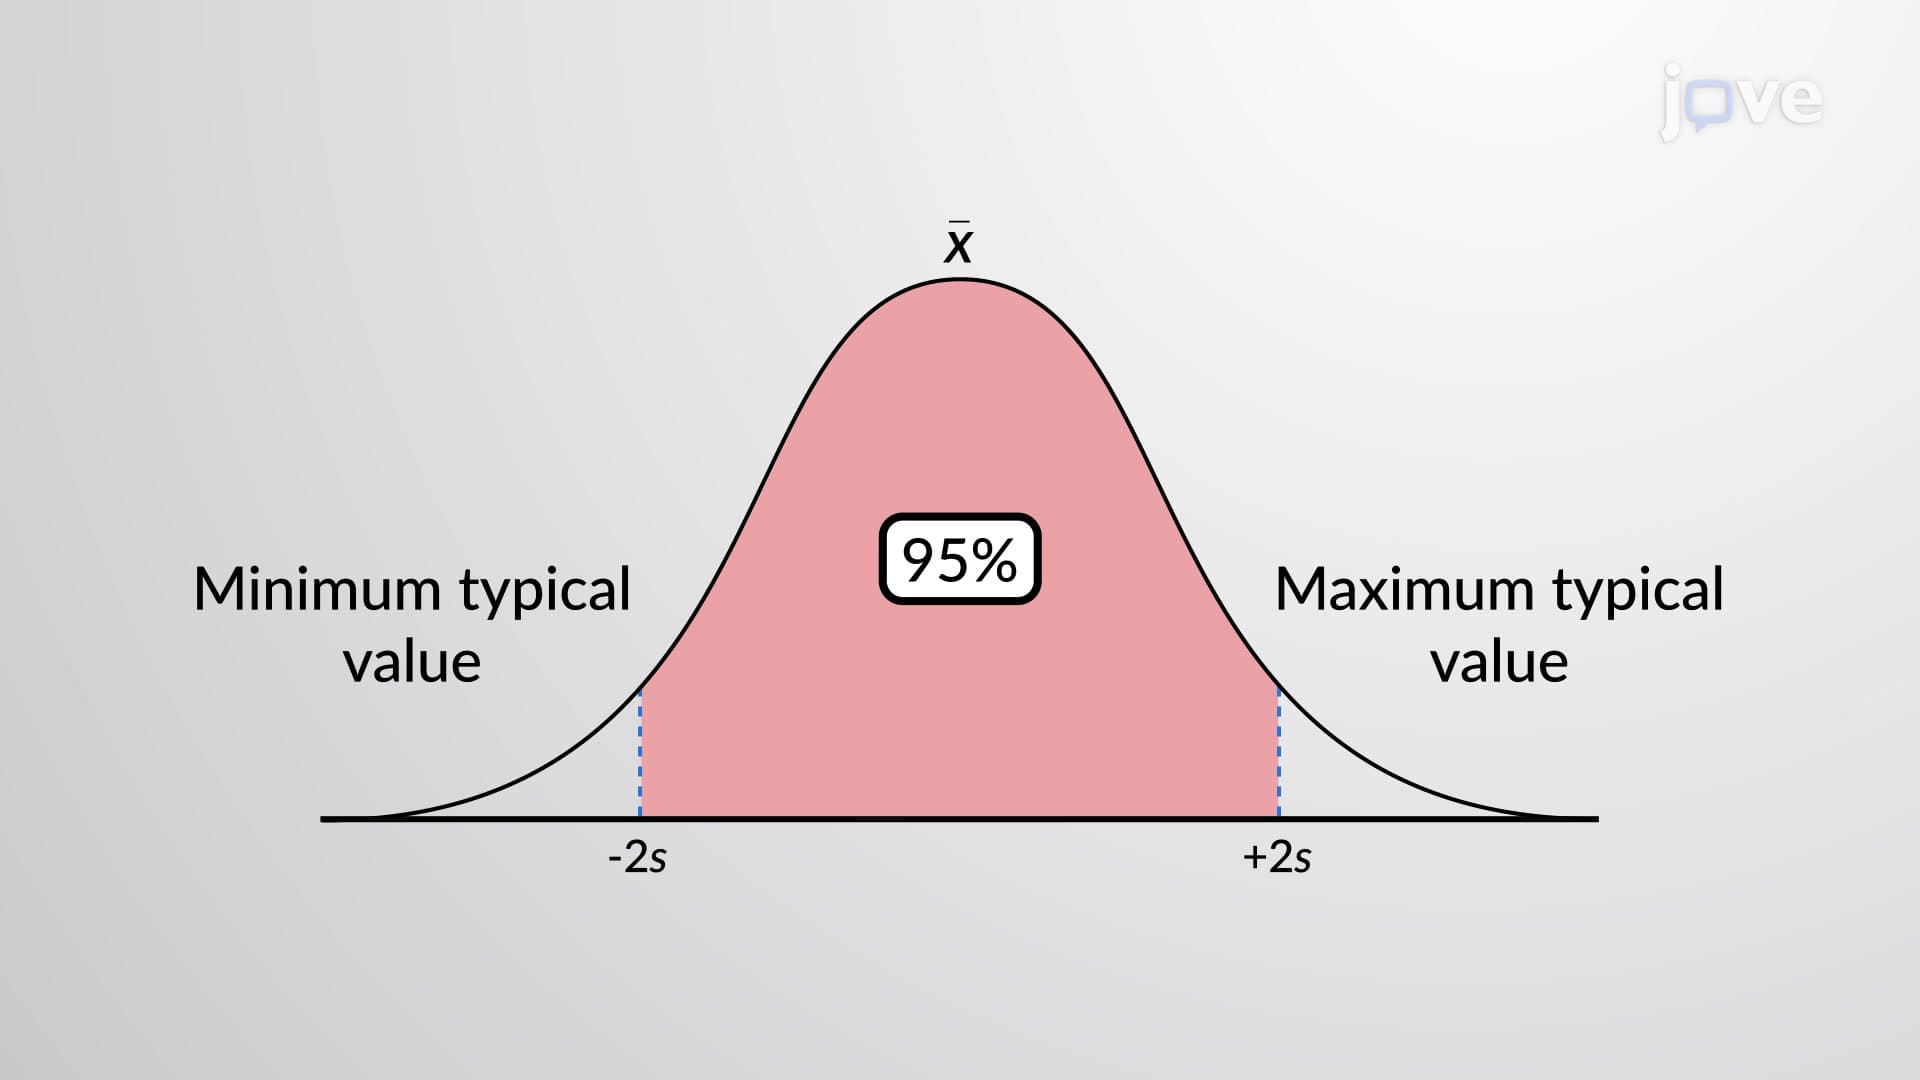
For instance, the range rule of thumb can be used to find the tallest and the shortest student in a class, given the mean student height and standard deviation. If the mean student height is 1.6 m and the standard deviation, s is 0.05 m, the height...
 01:27
Oxygen Transport in the Blood