Related Experiment Video
Updated: Feb 13, 2026
Surgical Closure of Equine Abdomen, Prevention, and Management of Incisional Complications
Published on: May 10, 2024
Alpha-2 adrenergic agonists for the prevention of cardiac complications among adults undergoing surgery
Dallas Duncan1, Ashwin Sankar, W Scott Beattie
1Department of Anesthesia, University of Toronto, 123 Edward Street, 12th Floor, Toronto, ON, Canada, M5G 1E2.

Background:
The surgical stress response plays an important role on the pathogenesis of perioperative cardiac complications. Alpha-2 adrenergic agonists attenuate this response and may help prevent postoperative cardiac complications.
Objectives:
To determine the efficacy and safety of α-2 adrenergic agonists for reducing mortality and cardiac complications in adults undergoing cardiac surgery and non-cardiac surgery.
Search Methods:
We searched CENTRAL (2017, Issue 4), MEDLINE (1950 to April Week 4, 2017), Embase (1980 to May 2017), the Science Citation Index, clinical trial registries, and reference lists of included articles.
Selection Criteria:
We included randomized controlled trials that compared α-2 adrenergic agonists (i.e. clonidine, dexmedetomidine or mivazerol) against placebo or non-α-2 adrenergic agonists. Included trials had to evaluate the efficacy and safety of α-2 adrenergic agonists for preventing perioperative mortality or cardiac complications (or both), or measure one or more relevant outcomes (i.e. death, myocardial infarction, heart failure, acute stroke, supraventricular tachyarrhythmia and myocardial ischaemia).
Data Collection And Analysis:
Two authors independently assessed trial quality, extracted data and independently performed computer entry of abstracted data. We contacted study authors for additional information. Adverse event data were gathered from the trials. We evaluated included studies using the Cochrane 'Risk of bias' tool, and the quality of the evidence underlying pooled treatment effects using GRADE methodology. Given the clinical heterogeneity between cardiac and non-cardiac surgery, we analysed these subgroups separately. We expressed treatment effects as pooled risk ratios (RR) with 95% confidence intervals (CI).
Main Results:
We included 47 trials with 17,039 participants. Of these studies, 24 trials only included participants undergoing cardiac surgery, 23 only included participants undergoing non-cardiac surgery and eight only included participants undergoing vascular surgery. The α-2 adrenergic agonist studied was clonidine in 21 trials, dexmedetomidine in 24 trials and mivazerol in two trials.In non-cardiac surgery, there was high quality evidence that α-2 adrenergic agonists led to a similar risk of all-cause mortality compared with control groups (1.3% with α-2 adrenergic agonists versus 1.7% with control; RR 0.80, 95% CI 0.61 to 1.04; participants = 14,081; studies = 16). Additionally, the risk of cardiac mortality was similar between treatment groups (0.8% with α-2 adrenergic agonists versus 1.0% with control; RR 0.86, 95% CI 0.60 to 1.23; participants = 12,525; studies = 5, high quality evidence). The risk of myocardial infarction was probably similar between treatment groups (RR 0.94, 95% CI 0.69 to 1.27; participants = 13,907; studies = 12, moderate quality evidence). There was no associated effect on the risk of stroke (RR 0.93, 95% CI 0.55 to 1.56; participants = 11,542; studies = 7; high quality evidence). Conversely, α-2 adrenergic agonists probably increase the risks of clinically significant bradycardia (RR 1.59, 95% CI 1.18 to 2.13; participants = 14,035; studies = 16) and hypotension (RR 1.24, 95% CI 1.03 to 1.48; participants = 13,738; studies = 15), based on moderate quality evidence.There was insufficient evidence to determine the effect of α-2 adrenergic agonists on all-cause mortality in cardiac surgery (RR 0.52, 95% CI 0.26 to 1.04; participants = 1947; studies = 16) and myocardial infarction (RR 1.01, 95% CI 0.43 to 2.40; participants = 782; studies = 8), based on moderate quality evidence. There was one cardiac death in the clonidine arm of a study of 22 participants. Based on very limited data, α-2 adrenergic agonists may have reduced the risk of stroke (RR 0.37, 95% CI 0.15 to 0.93; participants = 1175; studies = 7; outcome events = 18; low quality evidence). Conversely, α-2 adrenergic agonists increased the risk of bradycardia from 6.4% to 12.0% (RR 1.88, 95% CI 1.35 to 2.62; participants = 1477; studies = 10; moderate quality evidence), but their effect on hypotension was uncertain (RR 1.19, 95% CI 0.87 to 1.64; participants = 1413; studies = 9; low quality evidence).These results were qualitatively unchanged in subgroup analyses and sensitivity analyses.
Authors' Conclusions:
Our review concludes that prophylactic α-2 adrenergic agonists generally do not prevent perioperative death or major cardiac complications. For non-cardiac surgery, there is moderate-to-high quality evidence that these agents do not prevent death, myocardial infarction or stroke. Conversely, there is moderate quality evidence that these agents have important adverse effects, namely increased risks of hypotension and bradycardia. For cardiac surgery, there is moderate quality evidence that α-2 adrenergic agonists have no effect on the risk of mortality or myocardial infarction, and that they increase the risk of bradycardia. The quality of evidence was inadequate to draw conclusions regarding the effects of alpha-2 agonists on stroke or hypotension during cardiac surgery.
Insights
Alpha-2 adrenergic agonists do not prevent perioperative death or cardiac complications in non-cardiac surgery, but increase risks of bradycardia and hypotension. Evidence for cardiac surgery is insufficient, though bradycardia risk increases.
Area of Science:
- Anesthesiology
- Cardiology
- Critical Care Medicine
Background:
- The surgical stress response contributes to perioperative cardiac complications.
- Alpha-2 adrenergic agonists may mitigate this response and prevent such complications.
Purpose of the Study:
- To evaluate the efficacy and safety of alpha-2 adrenergic agonists (clonidine, dexmedetomidine, mivazerol) in reducing mortality and cardiac complications.
- The study focused on adult patients undergoing both cardiac and non-cardiac surgery.
Main Methods:
- A systematic review and meta-analysis of 47 randomized controlled trials involving 17,039 participants.
- Data were extracted and analyzed for outcomes including mortality, myocardial infarction, stroke, bradycardia, and hypotension.
- Evidence quality was assessed using GRADE methodology, with subgroup analyses for cardiac and non-cardiac surgery.
Main Results:
- In non-cardiac surgery, alpha-2 adrenergic agonists showed no significant effect on all-cause mortality, cardiac mortality, myocardial infarction, or stroke (high-quality evidence).
- However, these agents significantly increased the risk of bradycardia and hypotension (moderate-quality evidence).
- In cardiac surgery, evidence was insufficient to determine effects on mortality or myocardial infarction, but bradycardia risk was increased (moderate-quality evidence).
Conclusions:
- Prophylactic alpha-2 adrenergic agonists do not generally prevent perioperative death or major cardiac complications.
- For non-cardiac surgery, moderate-to-high quality evidence indicates no benefit for mortality or major cardiac events, with increased risks of hypotension and bradycardia.
- For cardiac surgery, evidence is insufficient to conclude benefits, with increased bradycardia risk noted.

Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 01:18
Adrenergic Agonists: Therapeutic Classification
Vasopressor or pressor agents: They increase blood pressure and function as cardiac stimulants. Examples include endogenous catecholamines (norepinephrine and dopamine) and synthetic agents (phenylephrine).
Bronchodilators: β2-agonists can relax bronchial muscles and widen airways. They are commonly used for treating obstructive pulmonary...
 01:30
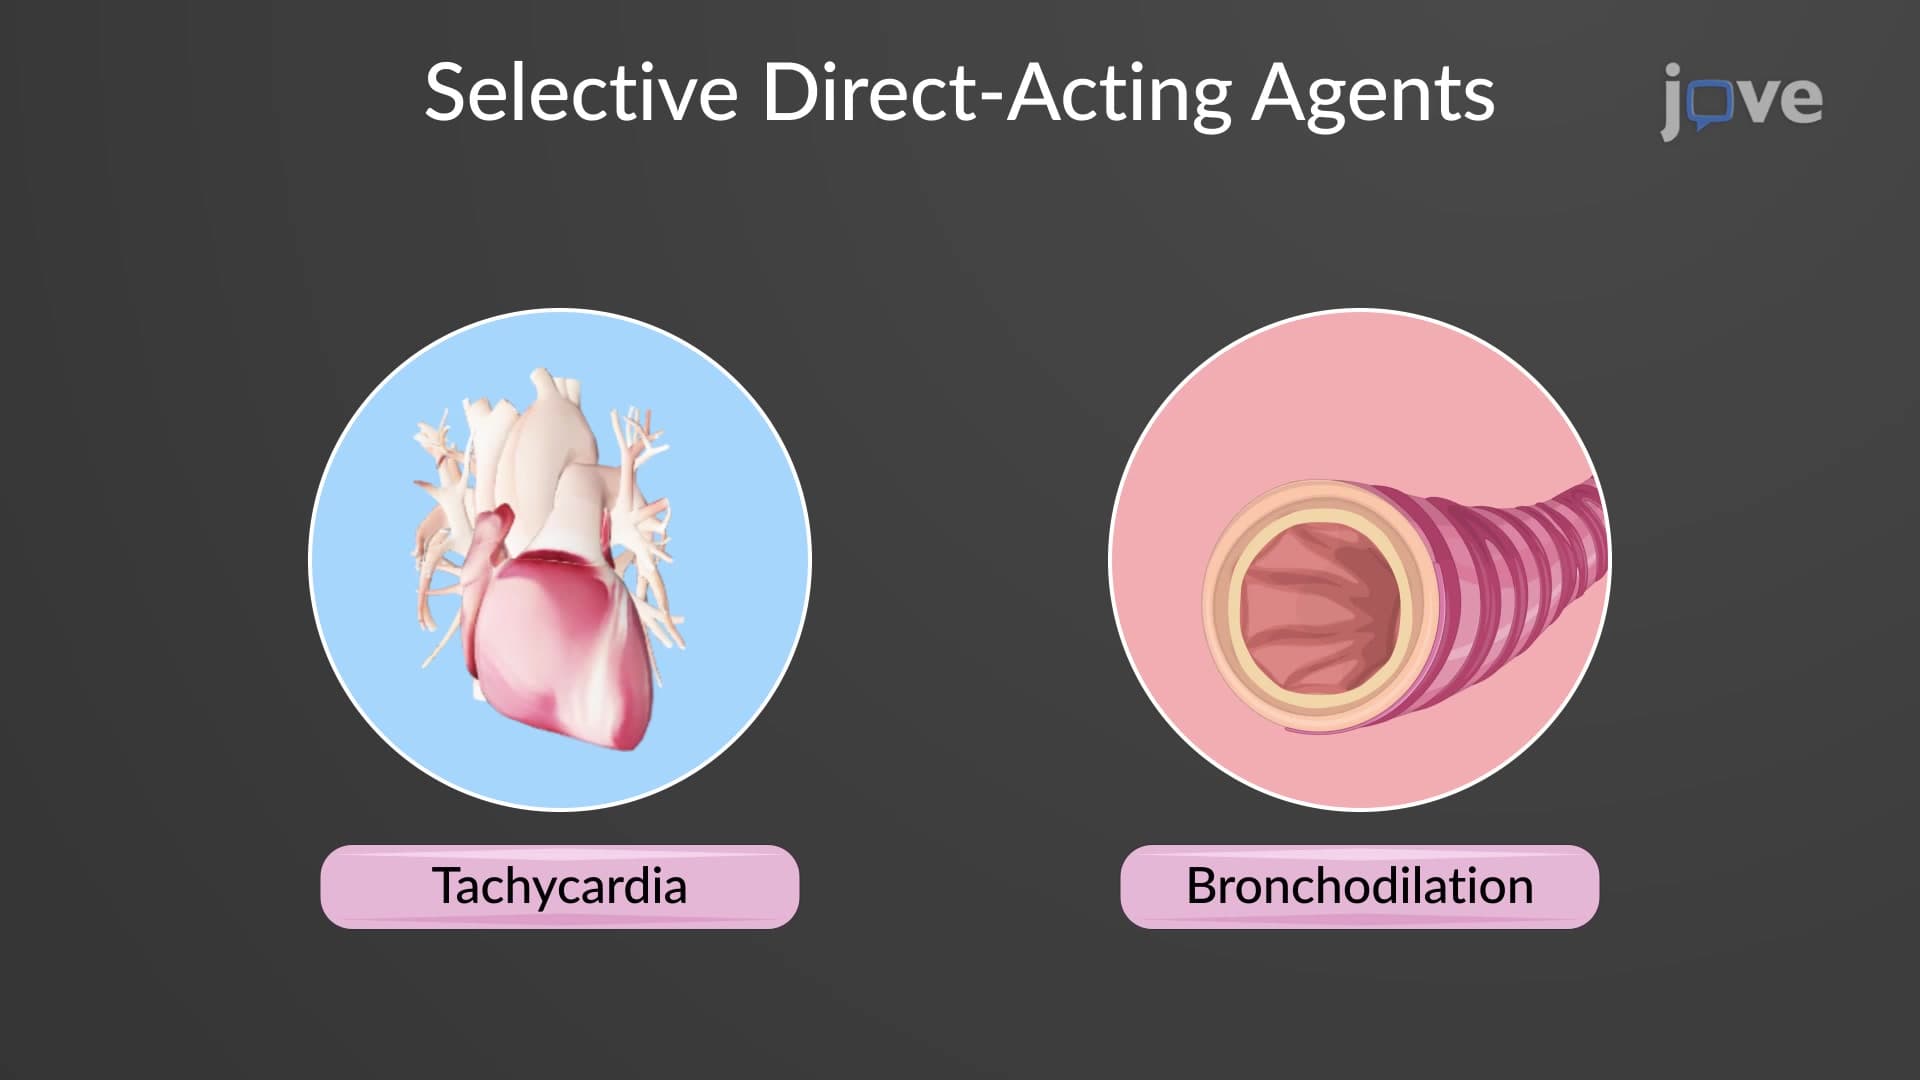
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:25
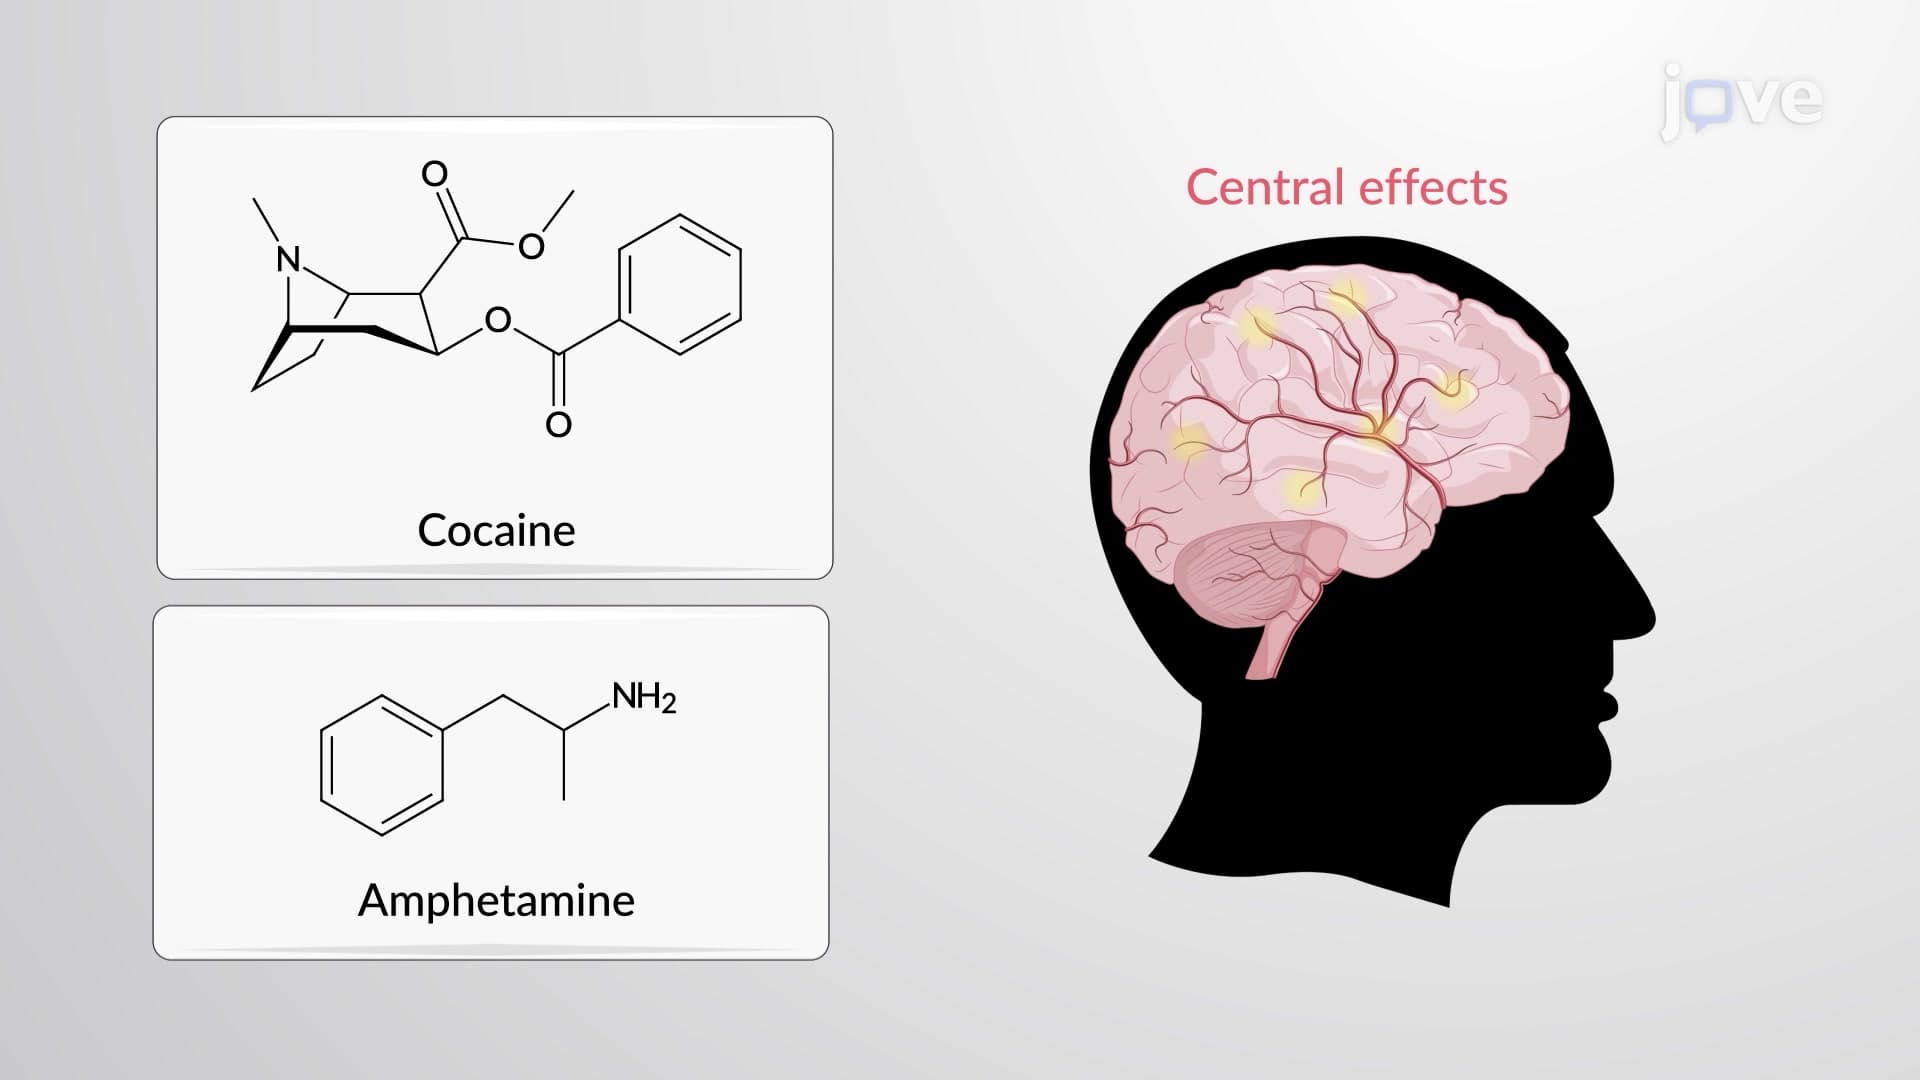
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral...
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
 01:16
Adrenergic Agonists: Chemistry and Structure-Activity Relationship
Aromatic ring substitutions: Substituting the aromatic ring with –OH groups at positions 3 and 4 yields catecholamines (e.g., epinephrine), which have a high affinity for adrenoceptors. Hydrogen bonding between –OH groups and receptors enhances adrenergic activity.
Separation of...