Related Experiment Video
Updated: Feb 13, 2026

Focused Assessment with Sonography for Trauma FAST Exam: Image Acquisition
Published on: September 22, 2023
Imaging of Combat-Related Thoracic Trauma - Blunt Trauma and Blast Lung Injury
John P Lichtenberger1, Andrew M Kim1, Dane Fisher1
1Department of Radiology and Radiological Sciences, Uniformed Services University of the Health Sciences, 4301 Jones Bridge Road, Bethesda, MD 20814.

Introduction:
Combat-related thoracic trauma (CRTT) is a significant contributor to morbidity and mortality of the casualties from Operation Enduring Freedom (OEF) and Operation Iraqi Freedom (OIF). Penetrating, blunt, and blast injuries are the most common mechanisms of trauma to the chest. Imaging plays a key role in the battlefield management of CRTT casualties. This work discusses the imaging manifestations of thoracic injuries from blunt trauma and blast injury, emphasizing epidemiology and diagnostic clues seen during OEF and OIF.
Materials And Methods:
The assessment of radiologic findings in patients who suffer from combat-related blunt thoracic trauma and blast injury is the basis of this work. The imaging modalities for this work include multi-detector computed tomography (MDCT) and chest radiography.
Results:
Multiple imaging modalities are available to imagers on or near the battlefront, including radiography, fluoroscopy, and MDCT. MDCT with multi-planar reconstructions is the most sensitive imaging modality available in combat hospitals for the evaluation of CRTT. In modern combat, blunt and blast injuries account for a significant portion of CRTT. Individual body armor converts penetrating trauma to blunt trauma, leading to pulmonary contusion that accounted for 50.2% of thoracic injuries during OIF and OEF. Flail chest, a subset of blunt chest injury, is caused by significant blunt force to the chest and occurs four times as frequently in combat casualties when compared with the civilian population. Imaging features of CRTT have significant diagnostic and prognostic value. Pulmonary contusions on chest radiography appear as patchy consolidations in the acute setting with ill-defined and non-segmental borders. MDCT of the chest is a superior imaging modality in diagnosing and evaluating pulmonary contusion. Contusions on MDCT appear as crescentic ground-glass opacities (opacities through which lung interstitium and vasculature are still visible) and areas of consolidation that often do not respect the anatomic boundaries of the affected lobes. Additionally, small pulmonary contusions may exhibit sub-pleural sparing and may distinguish contusion from pneumonia or other lung pathology. Although pulmonary laceration is typically the result of penetrating trauma, laceration may also be caused by displaced rib fractures or significant shearing forces on the lung without penetrating injury. Because of elastic recoil of the normal pulmonary parenchyma surrounding the injury, pulmonary lacerations may present as late as 48-72 h after injury. Pulmonary lacerations may appear similar to pulmonary contusions on chest radiography initially and will require MDCT for definitive diagnosis. Blast injury is a defining injury of modern combat. Blast lung injury is initially diagnosed with chest radiography, where the pattern of lung opacities has previously been described by clinicians as "batwing" or "butterfly" because of its central appearance in the lung. "Peribronchovascular" may be a more accurate description of primary blast lung based on its appearance on MDCT. This pattern may differentiate primary blast lung injury from other causes of thoracic trauma.
Conclusion:
CRTT continues to be a significant contributor to the morbidity and mortality of those injured during OEF and OIF. The distinct injury patterns and atypical imaging manifestations of blunt trauma and blast lung injury are important to recognize early because of the acuity of this patient population and the influence of accurate diagnosis on clinical management.
Related Concept Videos
 01:15
Thoracic Aorta
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal...
 01:47
Lung Capacity
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
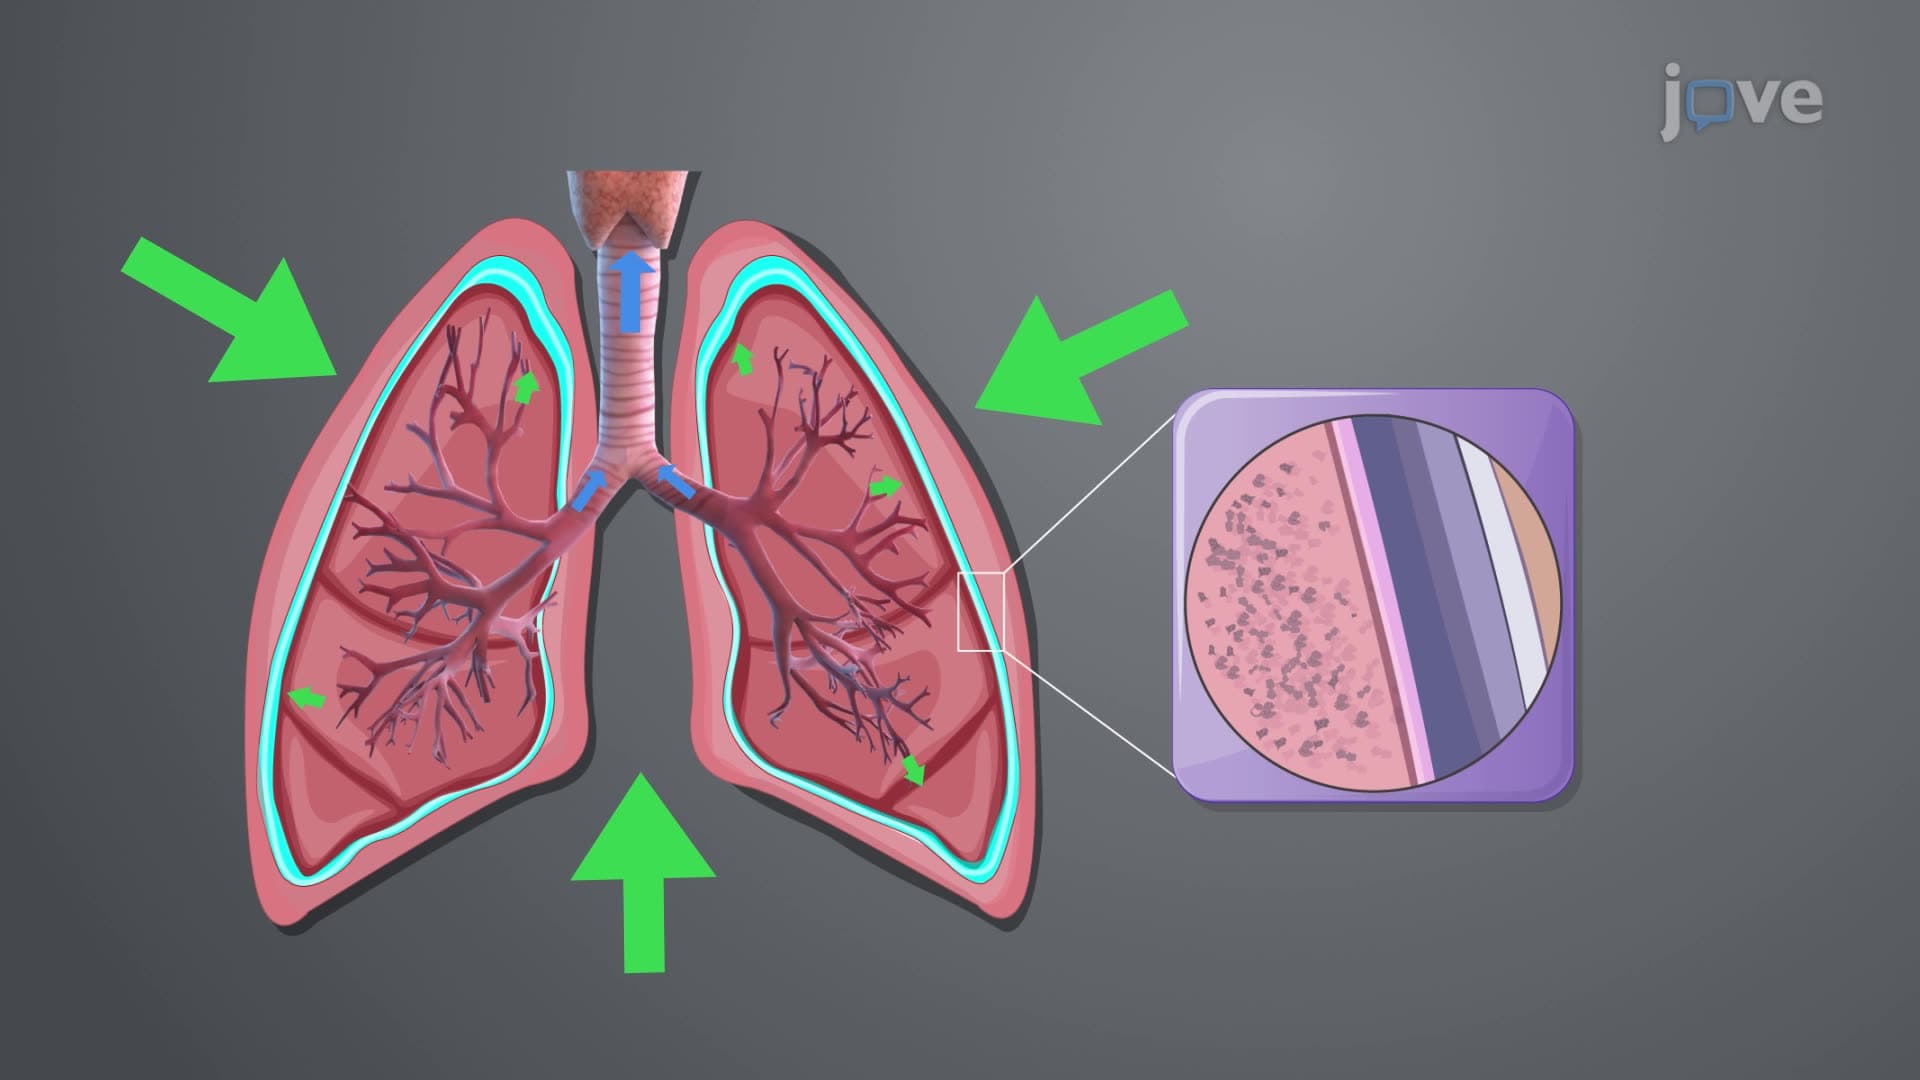
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:13
Pleura of the Lungs