Related Experiment Video
Updated: Feb 13, 2026
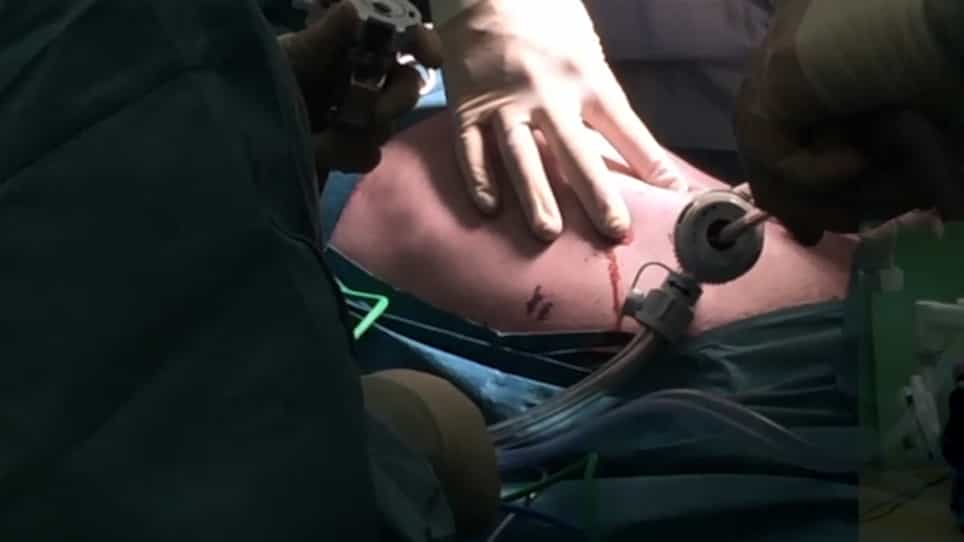

Robotic Lateral Pancreaticojejunostomy for Chronic Pancreatitis
Published on: December 14, 2019
Association between chronic pancreatitis and urolithiasis: A population-based cohort study
Chien-Hua Chen1,2,3,4, Cheng-Li Lin5,6, Long-Bin Jeng7,8
1Digestive Disease Center, Show-Chwan Memorial Hospital, Changhua, Taiwan.

Purpose:
Chronic pancreatitis (CP) can cause fat or bile acid malabsorption due to exocrine insufficiency. Fat or bile acid malabsorption has been reported to increase the risk of urolithiasis through increased intestinal oxalate absorption. However, no studies have reported an association between CP and urolithiasis.
Methods:
We identified 15,848 patients (age: ≥20 years) diagnosed as having CP between 2000 and 2010 from the National Health Insurance Research Database as the study cohort. Beneficiaries without a history of CP were randomly selected and propensity-matched with the study cohort in a 1:4 ratio according to age; sex; comorbidities of hyperlipidemia, diabetes, obesity, hypertension, chronic obstructive pulmonary disease, alcohol-related illness, stroke, and coronary artery disease; and the index date. The prevalence of inflammatory bowel disease (0.44%), hyperparathyroidism (0.10%), or end stage renal disease (1.55%) in CP patients was low, but these comorbidities were also considered in the analysis. All patients were followed until the end of 2011 or withdrawal from the National Health Insurance program to determine the incidence of urolithiasis.
Results:
The cumulative incidence of urolithiasis was higher in the CP cohort than that in the non-CP cohort (log-rank test, P < 0.001) with a 1.89-fold risk of urolithiasis (95% confidence interval [CI] = 1.74-2.06). The prevalence of CP was higher in men (81.9%) and in patients younger than 49 years (63.5%; mean age: 48.5 ± 15.3 years). CP was associated with the development of urolithiasis in each age group (≤49 years: aHR = 2.00, 95% CI = 1.81-2.22; 50-64 years: aHR = 1.71, 95% CI = 1.40-2.09; ≥65 years: aHR = 1.54, 95% CI = 1.20-1.98) and each sex (women: aHR = 2.10, 95% CI = 1.67-2.66; men; aHR = 1.86, 95% CI = 1.70-2.04). Among the patients without comorbidities, the rate of urolithiasis increased from 2.93/1,000 person-years in non-CP patients to 8.28/1,000 person-years in CP patients. Among the patients with comorbidities, the rate of urolithiasis increased from 6.12/1,000 person-years in non-CP patients to 10.9/1,000 person-years in CP patients. The contribution of CP to the relative risk of urolithiasis was greater in patients without comorbidities (without comorbidities: aHR = 2.81, 95% CI = 2.30-3.44) than in those with comorbidities (aHR = 1.76, 95% CI = 1.61-1.94).
Conclusion:
CP is associated with urolithiasis in this population-based cohort study. The contribution of CP to the relative risk of urolithiasis was even greater in patients with a lower risk of urolithiasis, such as those without other comorbidities. Our findings warrant a survey and education on urolithiasis for patients with CP.
Related Concept Videos
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:11
Genome-wide Association Studies-GWAS
GWAS does not require the identification of the target gene involved in...
 01:25
What is Population Genetics?
 00:30
What are Populations and Communities?
 02:04
Conservation of Small Populations