Related Experiment Video
Updated: Feb 13, 2026
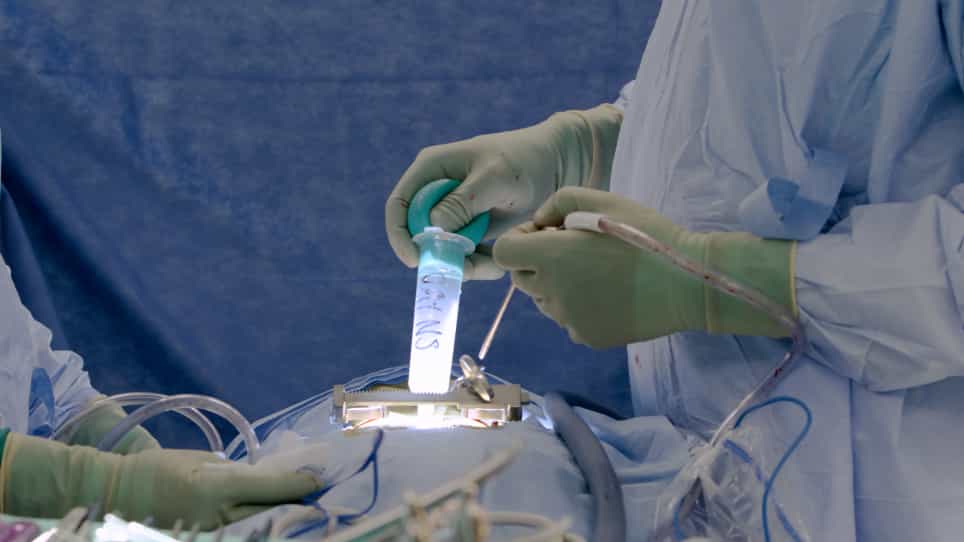
Intraoperative Ultrasound in Spinal Surgery
Published on: August 17, 2022
Preoperative embolization and local hemostatic agents in palliative decompression surgery for spinal metastases of
Nikita Zaborovskii1, Dmitrii Ptashnikov2,3, Dmitrii Mikaylov2
1Spine Surgery and Oncology Service, R.R. Vreden Russian Research Institute of Traumatology and Orthopedics, St. A. Baykova, 8, Saint-Petersburg, Russia, 195427. n.zaborovskii@yandex.ru.

Background:
Intraoperative hemorrhage can sometimes be massive in patients with spinal metastasis of renal cell carcinoma (MRCC). Preoperative embolization and local hemostatic agents are routinely use in spinal tumor surgery, but there have been no comparisons between these methods. This report compares the efficiency of various methods of bleeding control and their influence on outcome and survival after decompression procedures for MRCC.
Materials And Methods:
This was a retrospective case-control study of 54 patients with hypervascular extraosseous MRCC. All patients underwent palliative decompression procedures. We compared two groups of patients stratified by methods of bleeding control. The first group (EMB) included 32 patients who underwent preoperative embolization of a tumor. The second group (HEM) consisted of 22 patients, treated surgically using intraoperative local hemostatic agents. The parameters under evaluation were blood loss volume, drainage loss, possible complications, time of hospital stay and survival.
Results:
The median intraoperative blood loss for EMB group [1275 (95% CI 1175-1500) mL] was slightly less than the median in HEM group [1400 (95% CI 1050-1725) mL] without significant differences (p = 0.681). The postoperative drainage loss in HEM group [250 (95% CI 140-325) mL] was significantly less than that in EMB group [500 (95% CI 425-550) mL] (p = 0.013). The complication rate (infections, hematomas, neurological deficit) was nearly equal in all groups. No statistically significant difference in overall survival was found between groups: EMB-26 months (1 year-93.3%, 3 years-26.7%) and HEM-24 months (1 year-95.2%, 3 years-16.3%) (p = 0.360).
Conclusion:
Our results suggest that not all patients with MRCC require preoperative embolization, because usage of modern hemostatic agents can be an alternative bleeding control method.
More Related Videos

Related Concept Videos
 01:23
Local Anesthetics: Common Agents and Their Applications
Cocaine is an ester of benzoic acid and methylecgogine. It is used to anesthetize and vasoconstrict locally. Currently, it is used primarily for topical applications. It is beneficial for surgeries on the upper respiratory tract, providing anesthesia and shrinking the mucosa. Cocaine in the form of cocaine hydrochloride is...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:29
Pulmonary Embolism I: Introduction
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:27
Pulmonary Embolism III: Nursing Management
 01:20
Renal Corpuscle
Glomerulus: Structure and Function
The glomerulus is a tiny, intricate network of capillaries located at the beginning of the nephron. It's enveloped by the Bowman's capsule and receives its blood supply from an afferent arteriole, which divides into numerous...