Related Experiment Video
Updated: Feb 13, 2026


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Physiologic response to pre-arrest bolus dilute epinephrine in the pediatric intensive care unit
Catherine E Ross1, Lisa A Asaro2, David Wypij3
1Division of Medicine Critical Care, Department of Medicine, Boston Children's Hospital and Harvard Medical School, 333 Longwood Avenue, Boston, MA, 02115, USA.

Aim:
To quantify the physiologic effects of pre-arrest bolus dilute epinephrine in the pediatric intensive care unit.
Methods:
Patients <18 years old and ≥37 weeks gestation who received an intravenous bolus of dilute epinephrine (10 mcg/mL) in the pediatric intensive care units at our institution from January 2011 to March 2017 were retrospectively identified. Patients were excluded if doses exceeded 20 mcg/kg, or under the following circumstances: orders limiting resuscitation, extracorporeal membrane oxygenation, active chest compressions, simultaneous administration of other blood pressure-altering interventions or documented normotension prior to epinephrine. The primary outcome was change in systolic blood pressure within 5 min of epinephrine. Patients were categorized as non-responders if the change in systolic blood pressure was ≤10 mmHg.
Results:
One hundred forty-four patients were analyzed. The median index dose was 0.7 mcg/kg (IQR, 0.3-2.0), and the mean increase in systolic blood pressure was 31 mmHg (95% CI, 25-36; P < 0.001). Thirty-nine (27%) patients were classified as non-responders. Compared to responders, non-responders had higher rates of cardiac arrest or extracorporeal membrane oxygenation within 6 h (26% vs 10%; relative risk, 2.69; 95% CI, 1.21-5.97; P = 0.03), and had higher in-hospital mortality (51% vs 21%; relative risk, 2.45; 95% CI, 1.51-3.96; P < 0.001).
Conclusions:
In the majority of pre-arrest pediatric patients, bolus dilute epinephrine resulted in an increase in systolic blood pressure, and lack of blood pressure response was associated with poor outcomes. Optimal dosing of dilute epinephrine remains unclear.


Related Concept Videos
 01:20
Physiology of the Genitourinary System III: Urine Concentration and Dilution
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 02:59
Solution Concentration and Dilution
 03:02
Measurement: Derived Units
 03:38
Measurement: Standard Units
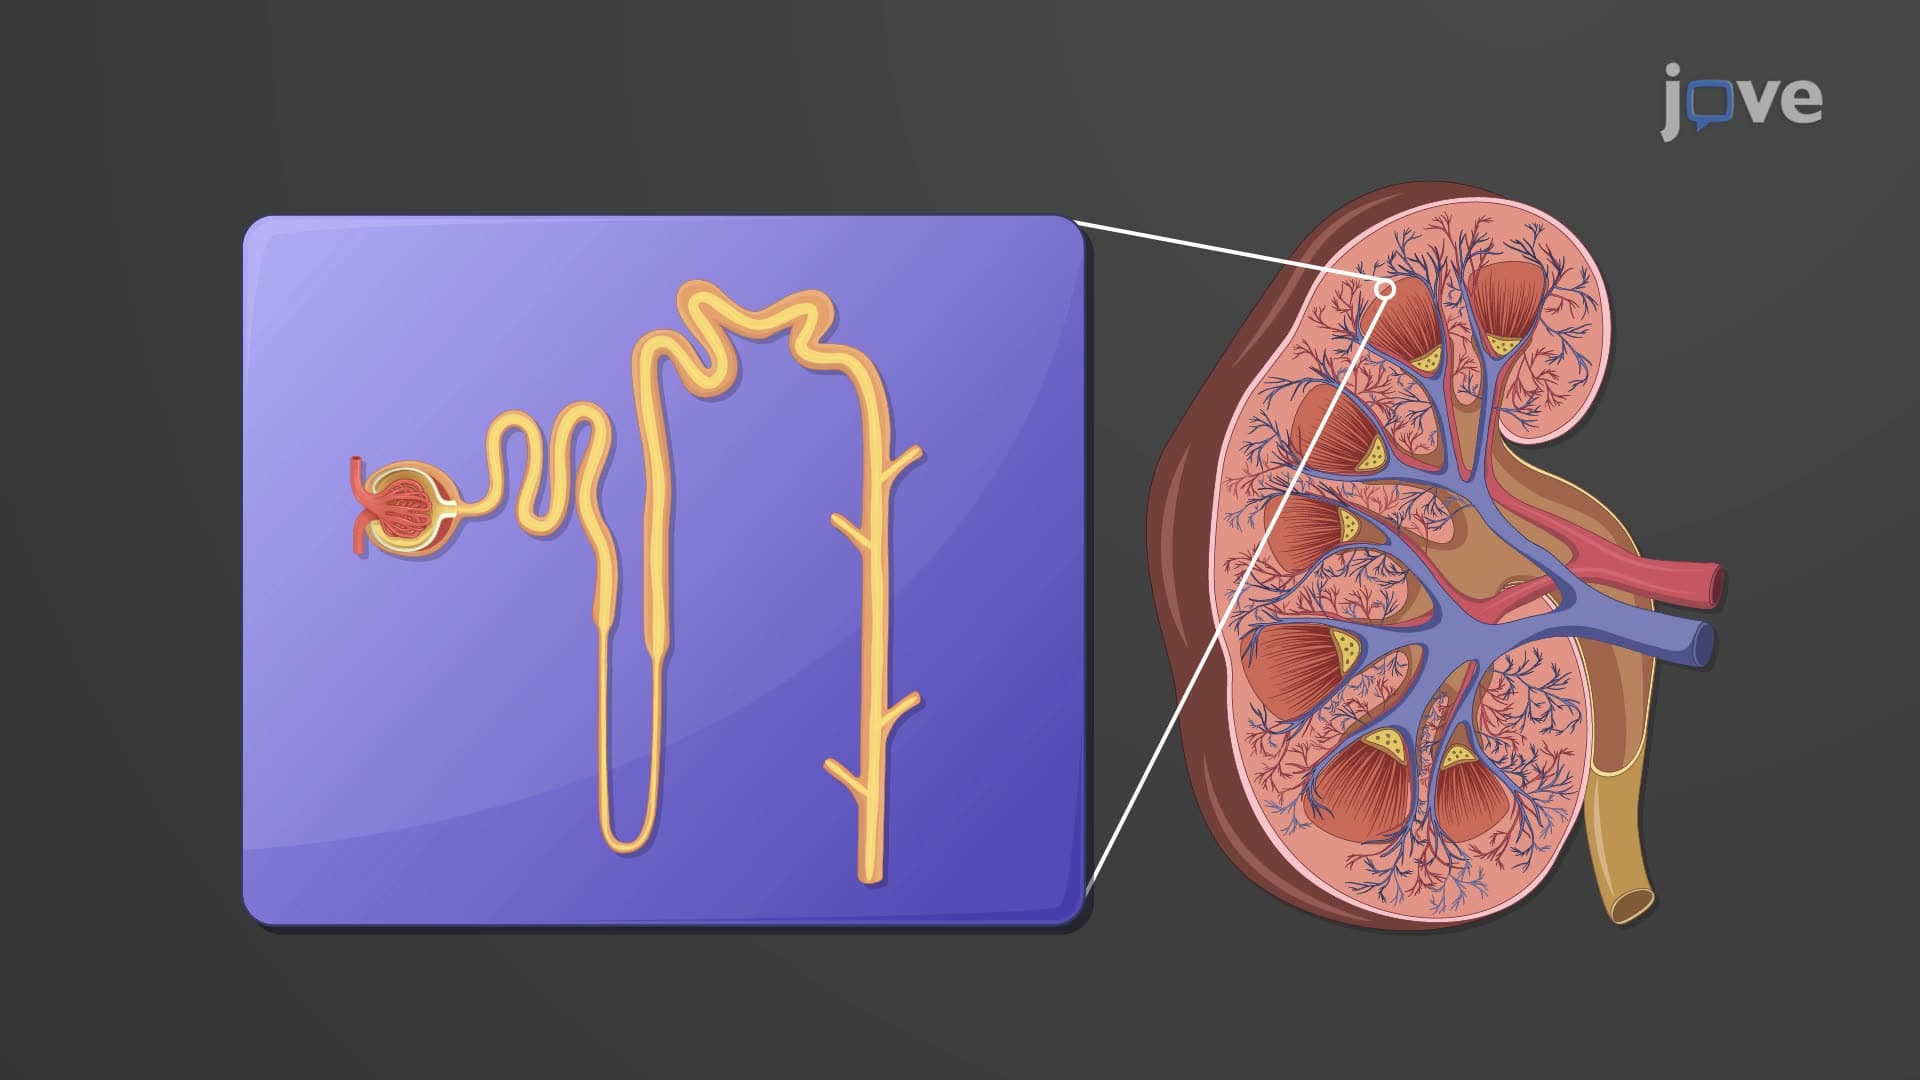 01:20
Formation of Dilute Urine
Filtrate Osmolarity in the PCT
Initially, as the filtrate passes through the proximal convoluted tubule (PCT), its...