Related Experiment Video
Updated: Feb 13, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Factors affecting outcomes following pelvic exenteration for locally recurrent rectal cancer

Background:
Pelvic exenteration for locally recurrent rectal cancer (LRRC) is associated with variable outcomes, with the majority of data from single-centre series. This study analysed data from an international collaboration to determine robust parameters that could inform clinical decision-making.
Methods:
Anonymized data on patients who had pelvic exenteration for LRRC between 2004 and 2014 were accrued from 27 specialist centres. The primary endpoint was survival. The impact of resection margin, bone resection, node status and use of neoadjuvant therapy (before exenteration) was assessed.
Results:
Of 1184 patients, 614 (51·9 per cent) had neoadjuvant therapy. A clear resection margin (R0 resection) was achieved in 55·4 per cent of operations. Twenty-one patients (1·8 per cent) died within 30 days and 380 (32·1 per cent) experienced a major complication. Median overall survival was 36 months following R0 resection, 27 months after R1 resection and 16 months following R2 resection (P < 0·001). Patients who received neoadjuvant therapy had more postoperative complications (unadjusted odds ratio (OR) 1·53), readmissions (unadjusted OR 2·33) and radiological reinterventions (unadjusted OR 2·12). Three-year survival rates were 48·1 per cent, 33·9 per cent and 15 per cent respectively. Bone resection (when required) was associated with a longer median survival (36 versus 29 months; P < 0·001). Node-positive patients had a shorter median overall survival than those with node-negative disease (22 versus 29 months respectively). Multivariable analysis identified margin status and bone resection as significant determinants of long-term survival.
Conclusion:
Negative margins and bone resection (where needed) were identified as the most important factors influencing overall survival. Neoadjuvant therapy before pelvic exenteration did not affect survival, but was associated with higher rates of readmission, complications and radiological reintervention.
More Related Videos
 04:04
Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
 02:41
Author Spotlight: Enhancing Women's Chronic Pelvic Pain Management Through Acupoint Catgut Embedding
Published on: May 3, 2024
Related Concept Videos
 01:27
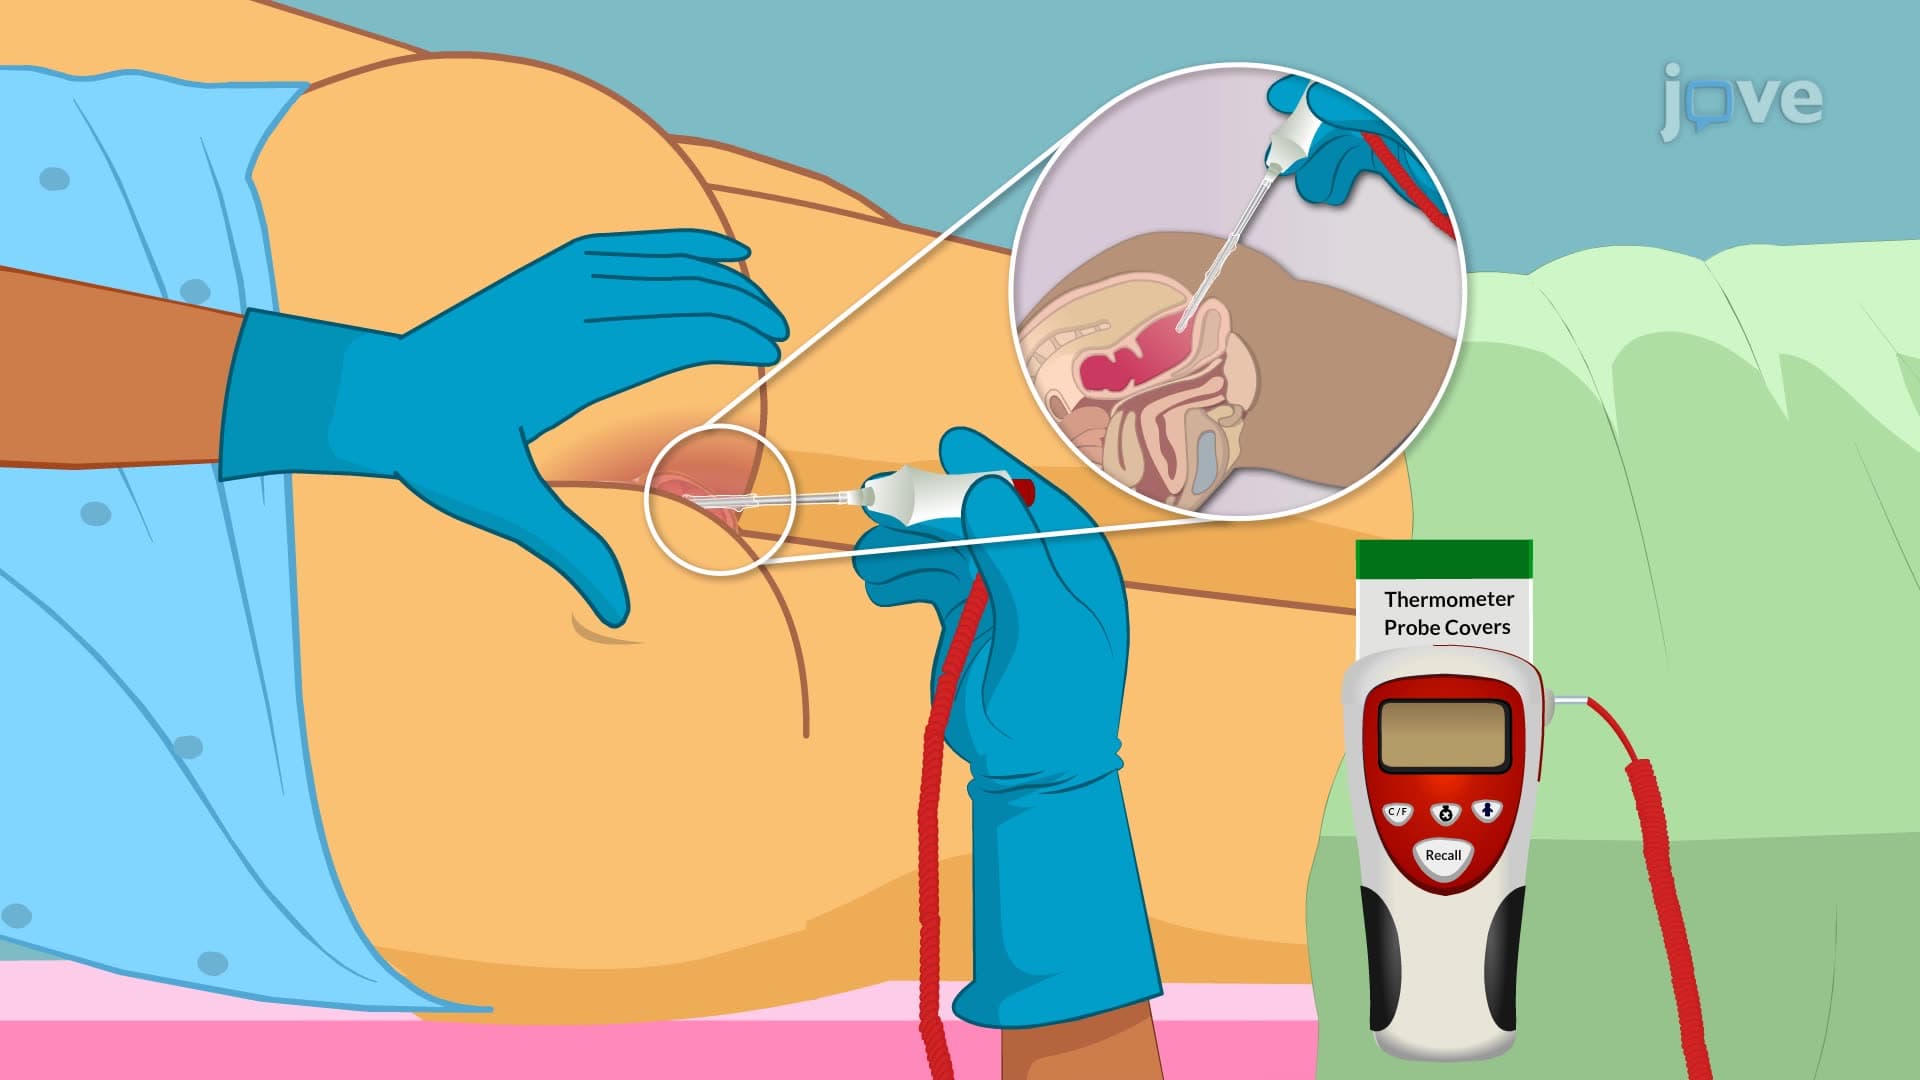
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 02:24
Predicting Reaction Outcomes
 01:26
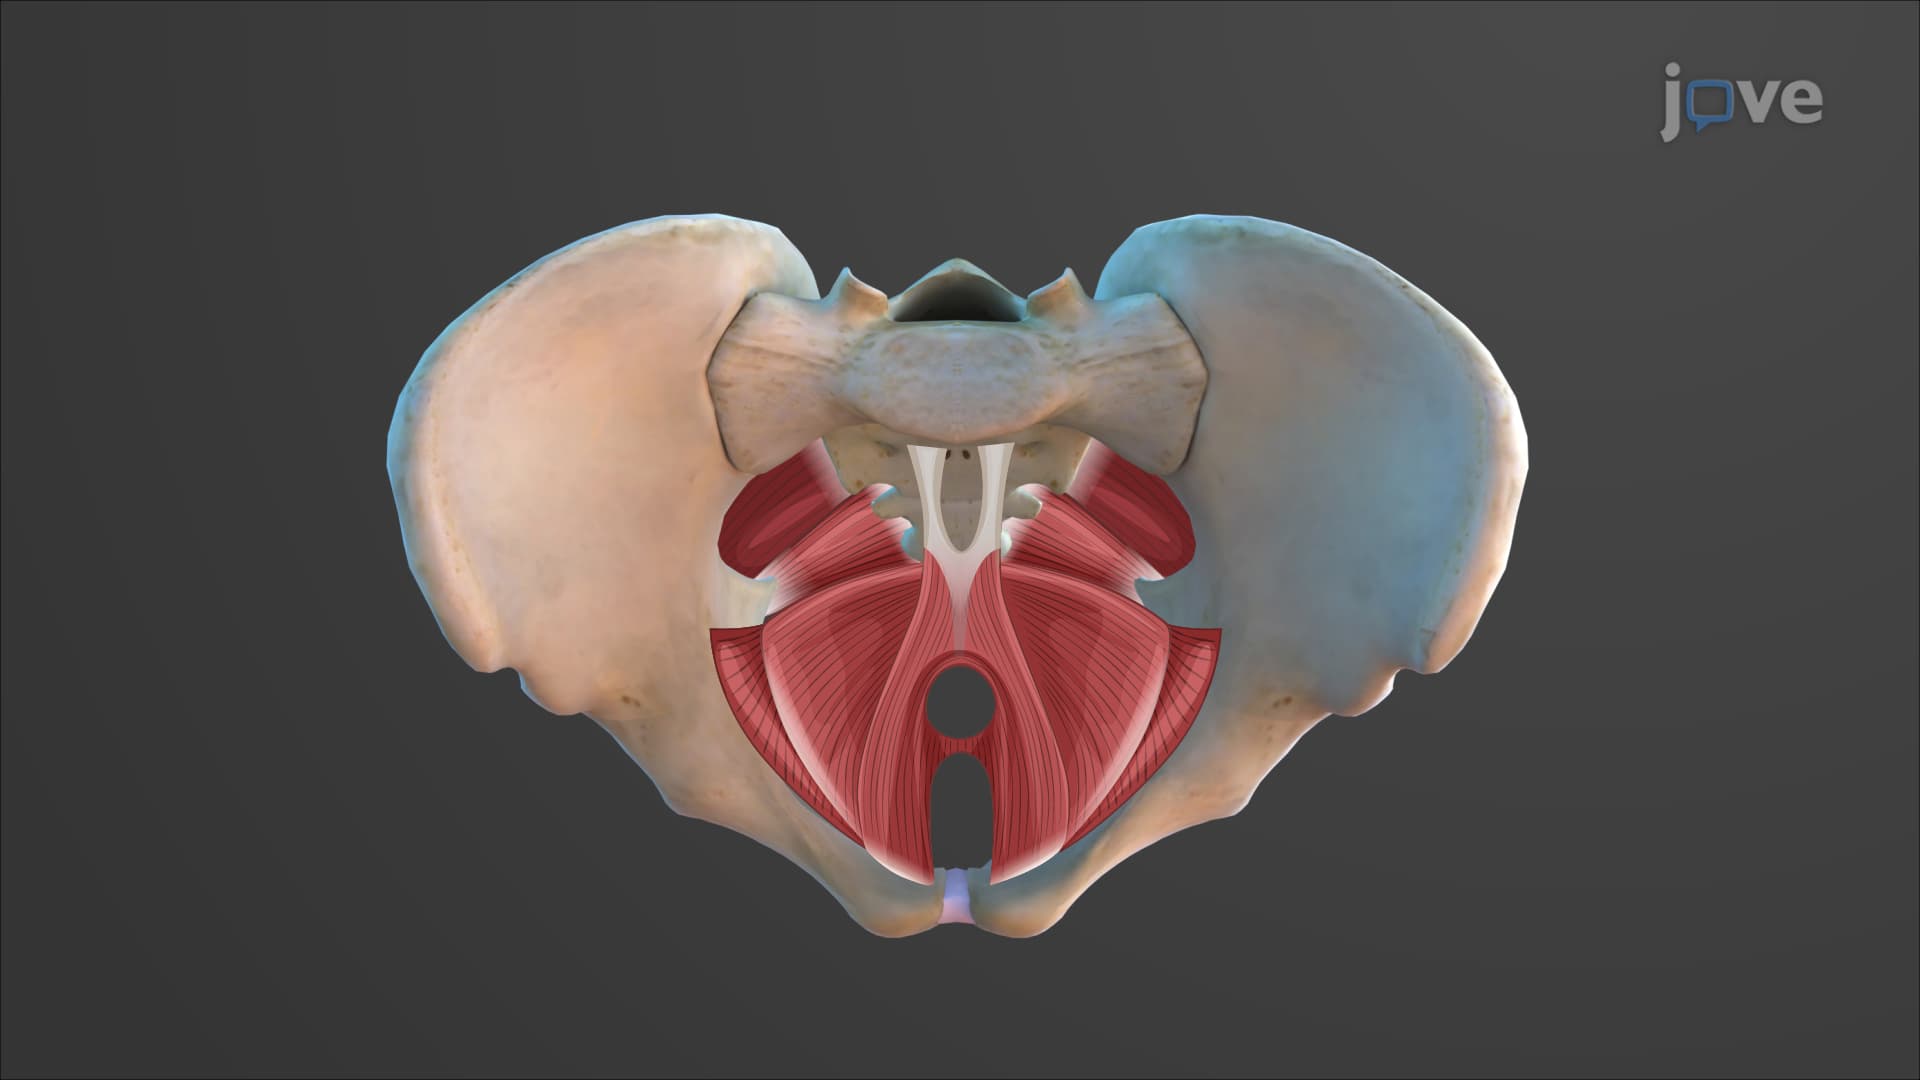
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...
 01:11
Guidelines for Writing Outcome
Patient outcomes reflect the patient's response to the goal rather than what the nurse aims to achieve. Terminology should be observable and measurable to avoid the reader's interpretation. The desired outcome should be realistic and achievable in the designated care timeframe. Expected outcomes should align with adjunctive therapies. The outcome should enhance care...
 02:16
Transcription Factors