Related Experiment Video
Updated: Feb 13, 2026
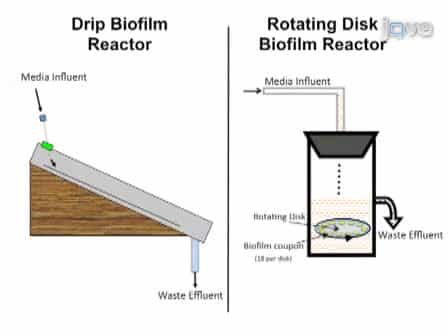

The Use of Drip Flow and Rotating Disk Reactors for Staphylococcus aureus Biofilm Analysis
Published on: December 27, 2010
Clinical and Genetic Risk Factors for Biofilm-Forming Staphylococcus aureus
Megan K Luther1,2,3, Diane M Parente1,2, Aisling R Caffrey1,2,3,4
1Rhode Island Infectious Diseases Research Program, Veterans Affairs Medical Center, Providence, Rhode Island, USA.

Abstract:
The molecular and clinical factors associated with biofilm-forming methicillin-resistant Staphylococcus aureus (MRSA) are incompletely understood. Biofilm production for 182 MRSA isolates obtained from clinical culture sites (2004 to 2013) was quantified. Microbiological toxins, pigmentation, and genotypes were evaluated, and patient demographics were collected. Logistic regression was used to quantify the effect of strong biofilm production (versus weak biofilm production) on clinical outcomes and independent predictors of a strong biofilm. Of the isolates evaluated, 25.8% (47/182) produced strong biofilms and 40.7% (74/182) produced weak biofilms. Strong biofilm-producing isolates were more likely to be from multilocus sequence typing (MLST) clonal complex 8 (CC8) (34.0% versus 14.9%; P = 0.01) but less likely to be from MLST CC5 (48.9% versus 73.0%; P = 0.007). Predictors for strong biofilms were spa type t008 (adjusted odds ratio [aOR], 4.54; 95% confidence interval [CI], 1.21 to 17.1) and receipt of chemotherapy or immunosuppressants in the previous 90 days (aOR, 33.6; 95% CI, 1.68 to 673). Conversely, patients with high serum creatinine concentrations (aOR, 0.33; 95% CI, 0.15 to 0.72) or who previously received vancomycin (aOR, 0.03; 95% CI, 0.002 to 0.39) were less likely to harbor strong biofilm-producing MRSA. Beta-toxin-producing isolates (aOR, 0.31; 95% CI, 0.11 to 0.89) and isolates with spa type t895 (aOR, 0.02 95% CI, <0.001 to 0.47) were less likely to produce strong biofilms. Patient outcomes also varied between the two groups. Specifically, patients with strong biofilm-forming MRSA were significantly more likely to be readmitted within 90 days (aOR, 5.43; 95% CI, 1.69 to 17.4) but tended to have decreased 90-day mortality (aOR, 0.36; 95% CI, 0.12 to 1.06). Patients that harbored t008 and received immunosuppressants were more likely to have strong biofilm-producing MRSA isolates. Clinically, patients with strong biofilm-forming MRSA were less likely to die at 90 days but five times more likely to be readmitted.
More Related Videos


Related Concept Videos
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:24
Drug Toxicity: Risk factors
 01:29
Biofilms
 01:12
Relative Risk
 02:16
Transcription Factors
 02:16
Genetics of Speciation