Related Experiment Video
Updated: Feb 13, 2026
Microfluidic Flow Chambers Using Reconstituted Blood to Model Hemostasis and Platelet Transfusion In Vitro
Published on: March 19, 2016
Multicenter study of crystalloid boluses and transfusion in pediatric trauma-When to go to blood?
Stephanie F Polites1, Rachel M Nygaard, Pooja N Reddy
1From the Department of Surgery (S.F.P., P.N.R., M.D.Z., T.A.E., D.D.P., D.B.K., C.R.M.), Mayo Clinic, Rochester; Department of Surgery (R.M.N., C.J.R., B.M.P., S.M.), Hennepin County Medical Center, Minneapolis, MN.

Background:
The 9th edition of Advanced Trauma Life Support recommends up to three crystalloid boluses in pediatric trauma patients with consideration of transfusion after the second bolus; however, this approach is debated. We aimed to determine if requirement of more than one fluid bolus predicts the need for transfusion.
Methods:
The 2010 to 2016 highest tier activation patients younger than 15 years from two ACS Level I pediatric trauma centers were identified from prospectively maintained trauma databases. Those with a shock index (heart rate/systolic blood pressure) greater than 0.9 were included. Crystalloid boluses (20 ± 10 mL/kg) and transfusions administered prehospital and within 12 hours of hospital arrival were determined. Univariate and multivariable analyses were conducted to determine association between crystalloid volume and transfusion.
Results:
Among 208 patients, the mean age was 5 ± 4 years (60% male), 91% sustained blunt injuries, and median (interquartile range) Injury Severity Score was 11 (6,25). Twenty-nine percent received one bolus, 17% received two, and 10% received at least three. Transfusion of any blood product occurred in 50 (24%) patients; mean (range) red blood cells was 23 (0-89) mL/kg, plasma 8 (0-69), and platelets 1 (0-18). The likelihood of transfusion increased logarithmically from 11% to 43% for those requiring 2 or more boluses (Fig. 1). This relationship persisted on multivariable analysis that adjusted for institution, age, and shock index with good discrimination (Area under the Receiver Operating Characteristic, 0.84). Shock index was also strongly associated with transfusion.
Conclusion:
Almost half of pediatric trauma patients with elevated shock index require transfusion following two crystalloid boluses and the odds of requiring a transfusion plateau at this point in resuscitation. This supports consideration of blood with the second bolus in conjunction with shock index though prospective studies are needed to confirm this and its impact on outcomes.
Level Of Evidence:
Therapeutic study, level IV.

Related Concept Videos
 01:15
Blood Transfusion
Blood Transfusion Overview
A blood transfusion is a medical procedure used to replace blood lost due to injury, surgery, or to treat conditions such as anemia or cancer. During a transfusion, donor blood is...
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...
 01:26
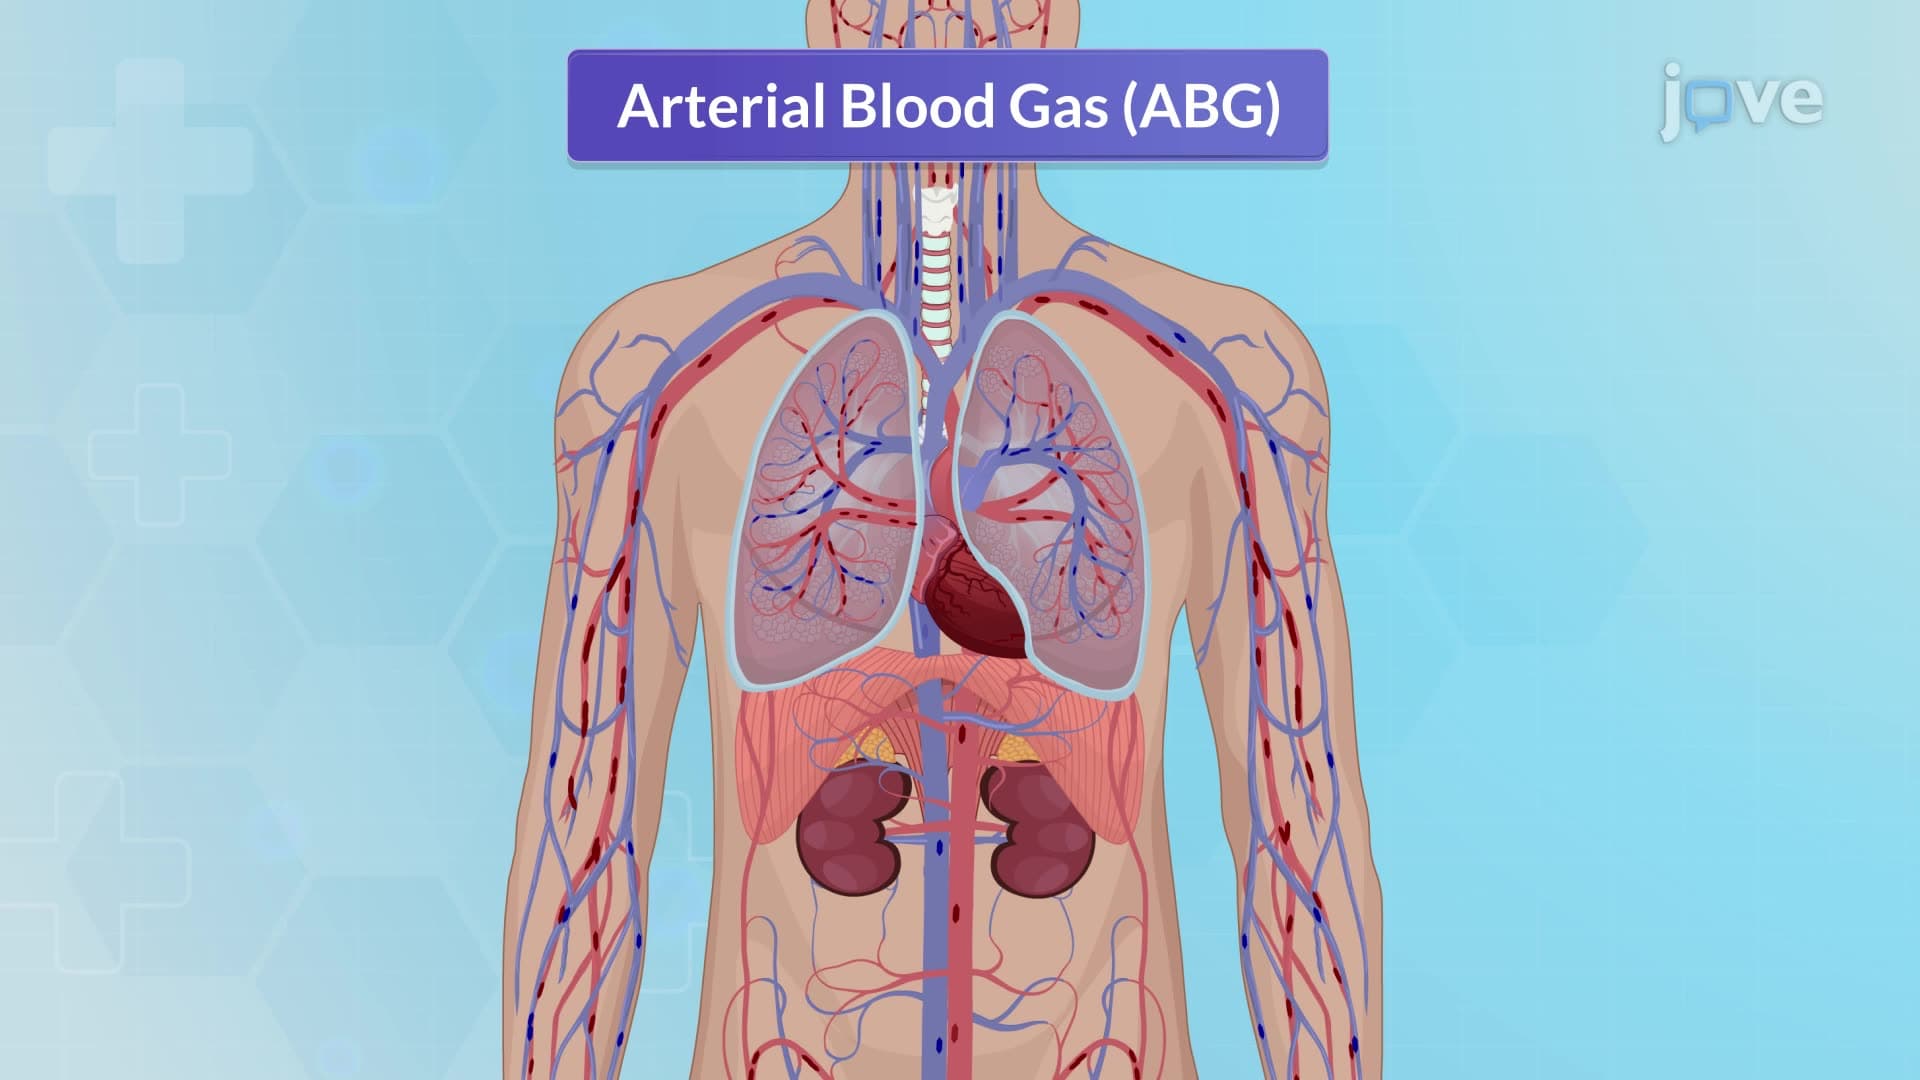
Blood Studies I: ABG and VBG
Arterial Blood Gas (ABG)
Arterial Blood Gas (ABG) studies are crucial for assessing the lungs' ability to supply oxygen and remove carbon dioxide, reflecting the patient's ventilation status. They also help understand the kidneys' capacity to...
 01:18
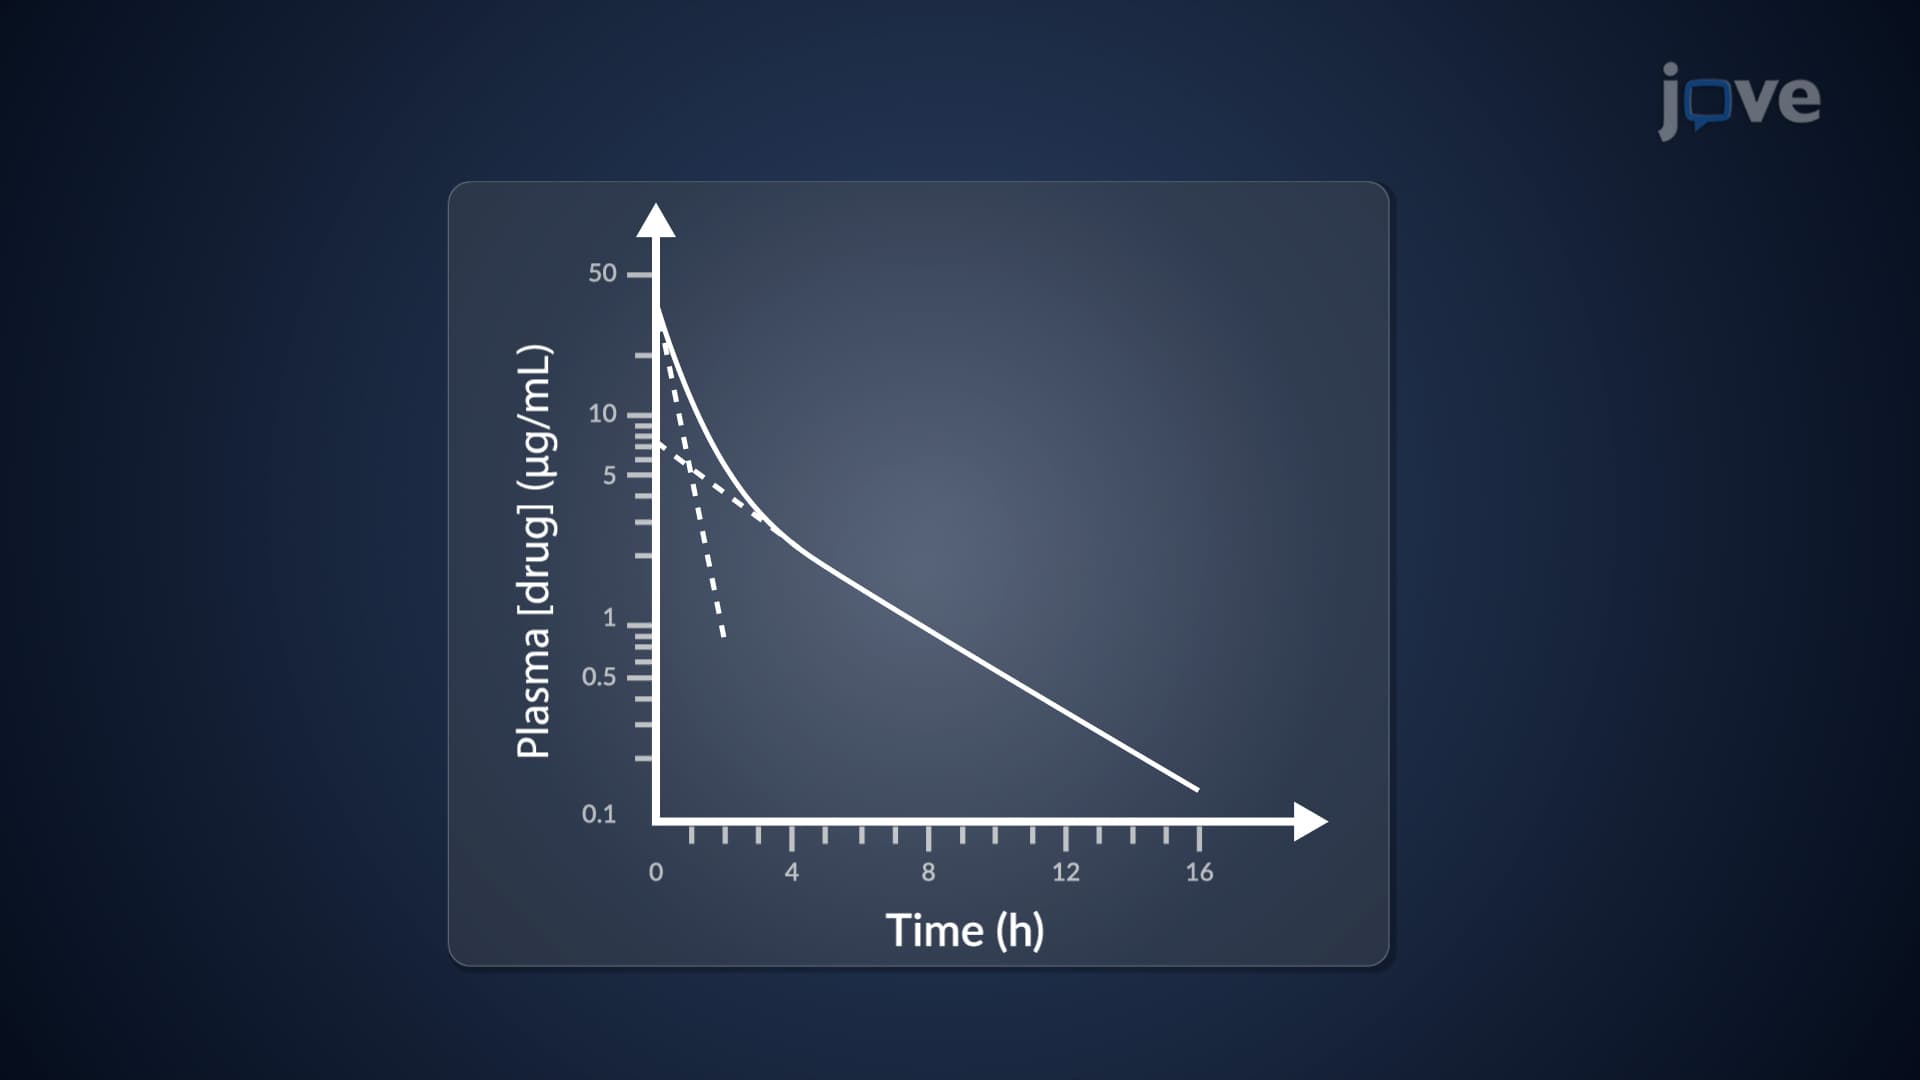
Two-Compartment Open Model: IV Bolus Administration
The disparity between drug input and the sum of drug transfer rates between...
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:19
One-Compartment Open Model for IV Bolus Administration: General Considerations
The drug's presence in the body is defined by an equation representing the difference between the rates of drug entry and exit. Key parameters—elimination rate constant,...