Related Experiment Video
Updated: Feb 13, 2026


A New Single Chamber Implantable Defibrillator with Atrial Sensing: A Practical Demonstration of Sensing and Ease of Implantation
Published on: February 28, 2012
Device complications with addition of defibrillation to cardiac resynchronisation therapy for primary prevention
Sérgio Barra1, Rui Providência2, Serge Boveda3
1Cardiology Department, Papworth Hospital NHS Foundation Trust, Cambridge, UK.

Insights
Choosing between cardiac resynchronisation therapy-pacemaker (CRT-P) and cardiac resynchronisation therapy-defibrillator (CRT-D) involves weighing risks. CRT-D shows similar acute complication rates but a higher risk of long-term issues, primarily infection, compared to CRT-P.
Area of Science:
- Cardiology
- Medical Devices
- Clinical Research
Background:
- The selection between cardiac resynchronisation therapy-pacemaker (CRT-P) and cardiac resynchronisation therapy-defibrillator (CRT-D) is debated.
- Indications for CRT-D in primary prevention are not well-defined, and its impact on device-related complications requires further study.
Purpose of the Study:
- To compare the risks of acute and late device-related complications between CRT-P and CRT-D implants.
- To inform clinical decision-making regarding CRT device selection.
Main Methods:
- An observational multicentre European cohort study included 3008 patients undergoing CRT implantation.
- Patients received either CRT-D (n=1785) or CRT-P (n=1223).
- Propensity score and competing risk analyses assessed device-related complications requiring reintervention, excluding inappropriate shocks unless due to lead malfunction.
Main Results:
- Acute complications occurred in 4.9% of patients, with no significant difference between CRT-D and CRT-P groups.
- During a mean follow-up of 41.4 months, CRT-D was independently associated with an increased risk of late complications (HR=1.68).
- CRT-D significantly increased the risk of device-related infection compared to CRT-P (HR 2.10).
Conclusions:
- CRT-D implantation carries a similar risk of acute complications but a higher risk of long-term complications, particularly infection, compared to CRT-P.
- These findings highlight the importance of considering long-term risks when selecting between CRT-D and CRT-P.
- Device-related infection risk is a key factor in CRT device selection.
Objective:
In patients indicated for cardiac resynchronisation therapy (CRT), the choice between a CRT-pacemaker (CRT-P) versus defibrillator (CRT-D) remains controversial and indications in this setting have not been well delineated. Apart from inappropriate therapies, which are inherent to the presence of a defibrillator, whether adding defibrillator to CRT in the primary prevention setting impacts risk of other acute and late device-related complications has not been well studied and may bear relevance for device selection.
Methods:
Observational multicentre European cohort study of 3008 consecutive patients with ischaemic or non-ischaemic dilated cardiomyopathy and no history of sustained ventricular arrhythmias, undergoing CRT implantation with (CRT-D, n=1785) or without (CRT-P, n=1223) defibrillator. Using propensity score and competing risk analyses, we assessed the risk of significant device-related complications requiring surgical reintervention. Inappropriate shocks were not considered except those due to lead malfunction requiring lead revision.
Results:
Acute complications occurred in 148 patients (4.9%), without significant difference between groups, even after considering potential confounders (OR=1.20, 95% CI 0.72 to 2.00, p=0.47). During a mean follow-up of 41.4±29 months, late complications occurred in 475 patients, giving an annual incidence rate of 26 (95% CI 9 to 43) and 15 (95% CI 6 to 24) per 1000 patient-years in CRT-D and CRT-P patients, respectively. CRT-D was independently associated with increased occurrence of late complications (HR=1.68, 95% CI 1.27 to 2.23, p=0.001). In particular, when compared with CRT-P, CRT-D was associated with an increased risk of device-related infection (HR 2.10, 95% CI 1.18 to 3.45, p=0.004). Acute complications did not predict overall late complications, but predicted device-related infection (HR 2.85, 95% CI 1.71 to 4.56, p<0.001).
Conclusions:
Compared with CRT-P, CRT-D is associated with a similar risk of periprocedural complications but increased risk of long-term complications, mainly infection. This needs to be considered in the decision of implanting CRT with or without a defibrillator.

Related Concept Videos
 01:27
Urinary Tract Calculi IV: Nutrition Therapy and Prevention
 01:27
Conjugate Addition (1,4-Addition) vs Direct Addition (1,2-Addition)
Conjugate addition results in a thermodynamically stable product. The reaction retains the stronger C=O bond at the expense of the weaker C=C π bond. The process is slow as the β carbon is less electrophilic than the carbonyl carbon.
Direct addition products are...
 01:24
Hemodialysis II: Procedure and Complications
 01:08
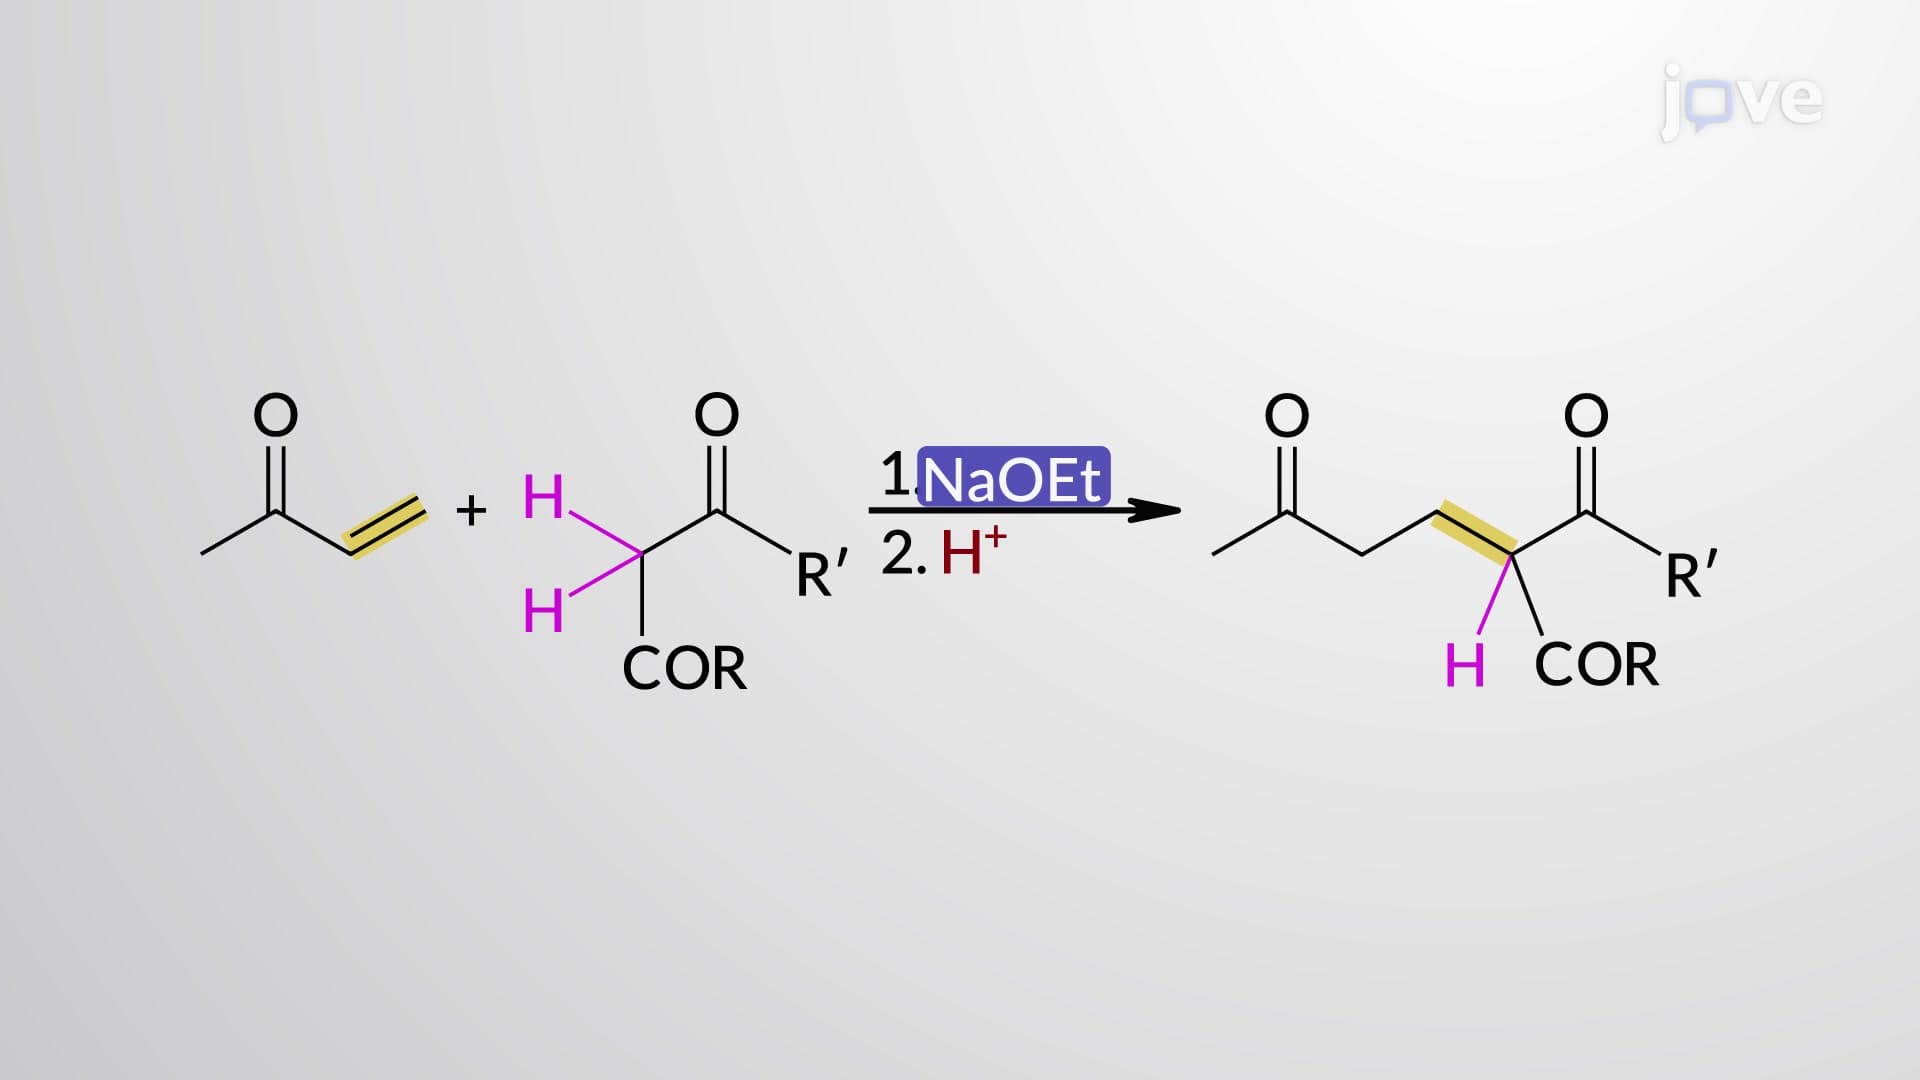
Conjugate Addition of Enolates: Michael Addition
 02:10
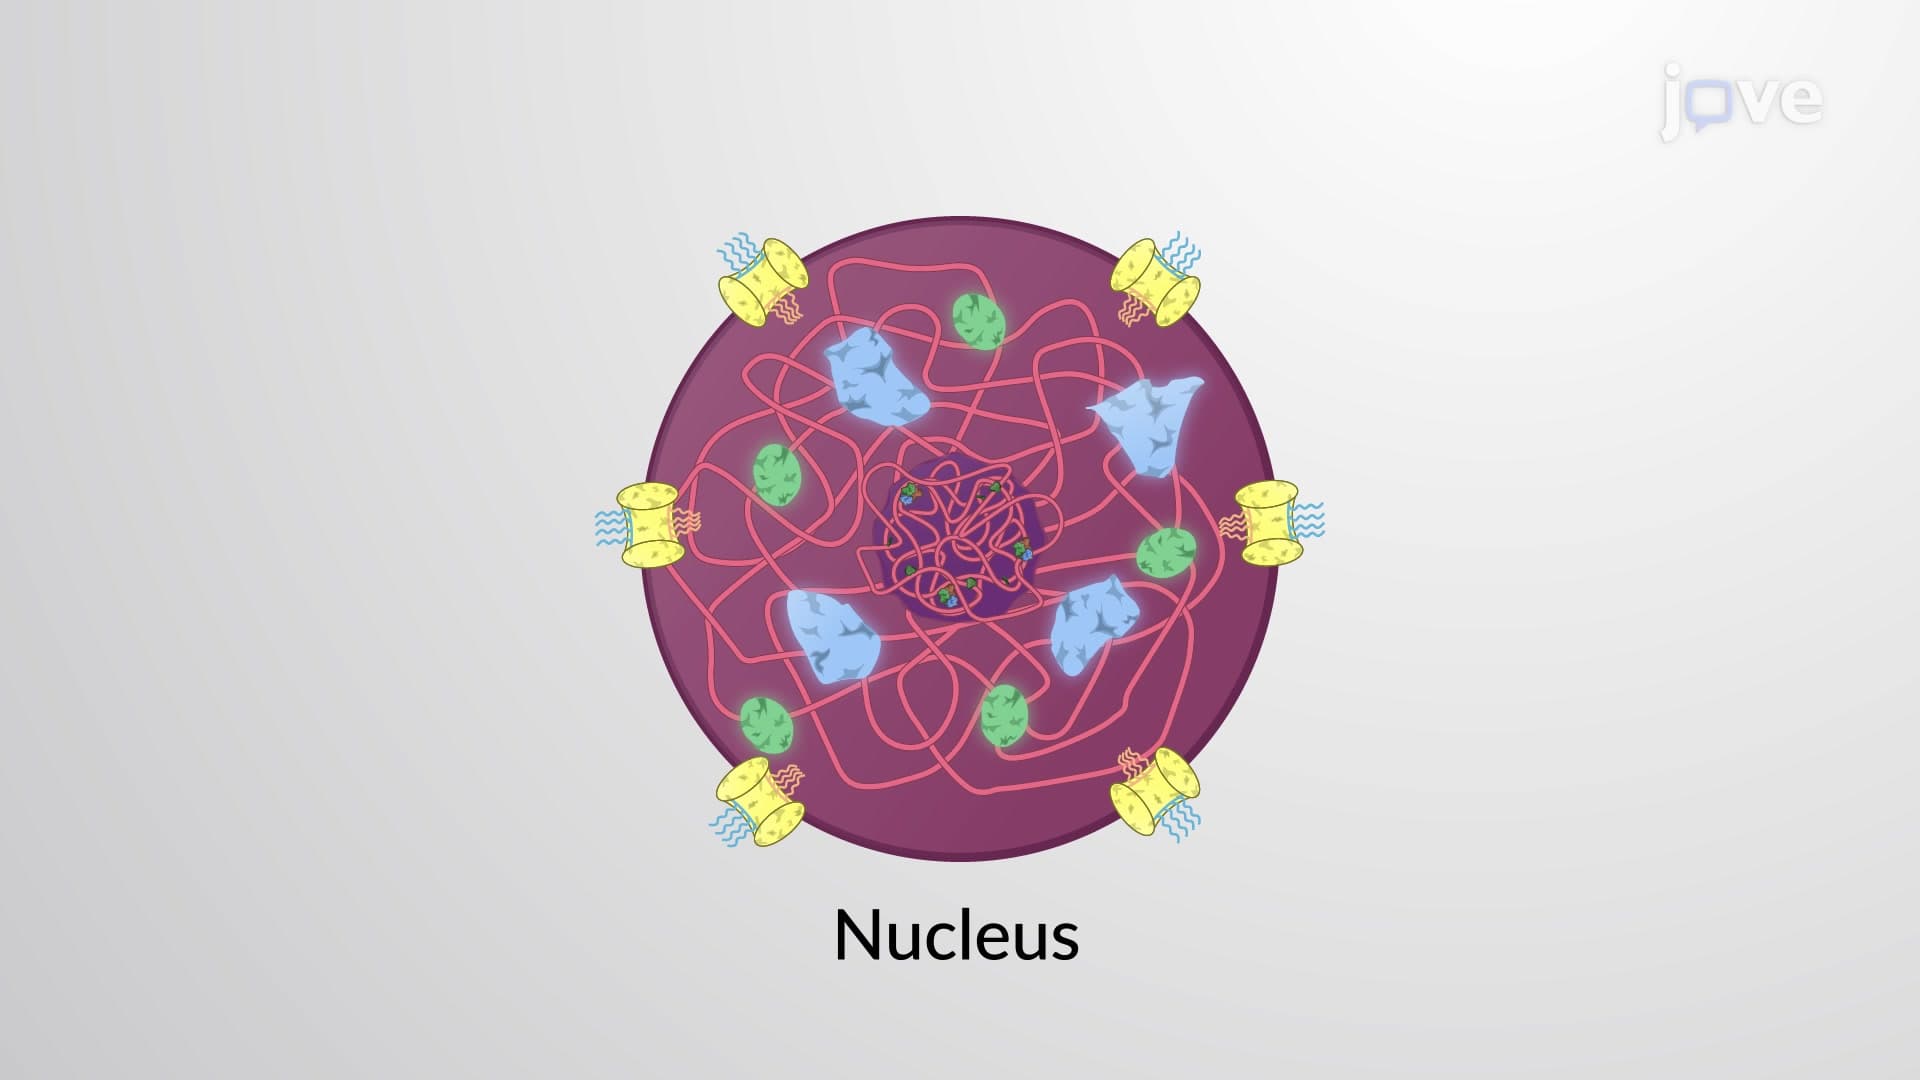
Additional Subnuclear Structures
The nucleus contains many membrane-less subnuclear organelles or nuclear bodies, such as nucleoli, Cajal bodies, speckles,...
 00:59
Gene Therapy