Related Experiment Video
Updated: Feb 13, 2026


A Multimodal Imaging Framework to Advance Phenotyping of Living Label-free Breast Cancer Cells
Published on: August 22, 2025
Durvalumab as third-line or later treatment for advanced non-small-cell lung cancer (ATLANTIC): an open-label,
Marina Chiara Garassino1, Byoung-Chul Cho2, Joo-Hang Kim3
1Fondazione IRCCS Istituto Nazionale dei Tumori, Milan, Italy.

Background:
Immune checkpoint inhibitors are a new standard of care for patients with advanced non-small-cell lung cancer (NSCLC) without EGFR tyrosine kinase or anaplastic lymphoma kinase (ALK) genetic aberrations (EGFR-/ALK-), but clinical benefit in patients with EGFR mutations or ALK rearrangements (EGFR+/ALK+) has not been shown. We assessed the effect of durvalumab (anti-PD-L1) treatment in three cohorts of patients with NSCLC defined by EGFR/ALK status and tumour expression of PD-L1.
Methods:
ATLANTIC is a phase 2, open-label, single-arm trial at 139 study centres in Asia, Europe, and North America. Eligible patients had advanced NSCLC with disease progression following at least two previous systemic regimens, including platinum-based chemotherapy (and tyrosine kinase inhibitor therapy if indicated); were aged 18 years or older; had a WHO performance status score of 0 or 1; and measurable disease per Response Evaluation Criteria in Solid Tumors (RECIST) version 1.1. Key exclusion criteria included mixed small-cell lung cancer and NSCLC histology; previous exposure to any anti-PD-1 or anti-PD-L1 antibody; and any previous grade 3 or worse immune-related adverse event while receiving any immunotherapy agent. Patients in cohort 1 had EGFR+/ALK+ NSCLC with at least 25%, or less than 25%, of tumour cells with PD-L1 expression. Patients in cohorts 2 and 3 had EGFR-/ALK- NSCLC; cohort 2 included patients with at least 25%, or less than 25%, of tumour cells with PD-L1 expression, and cohort 3 included patients with at least 90% of tumour cells with PD-L1 expression. Patients received durvalumab (10 mg/kg) every 2 weeks, via intravenous infusion, for up to 12 months. Retreatment was allowed for patients who benefited but then progressed after completing 12 months. The primary endpoint was the proportion of patients with increased tumour expression of PD-L1 (defined as ≥25% of tumour cells in cohorts 1 and 2, and ≥90% of tumour cells in cohort 3) who achieved an objective response, assessed in patients who were evaluable for response per independent central review according to RECIST version 1.1. Safety was assessed in all patients who received at least one dose of durvalumab and for whom any post-dose data were available. The trial is ongoing, but is no longer open to accrual, and is registered with ClinicalTrials.gov, number NCT02087423.
Findings:
Between Feb 25, 2014, and Dec 28, 2015, 444 patients were enrolled and received durvalumab: 111 in cohort 1, 265 in cohort 2, and 68 in cohort 3. Among patients with at least 25% of tumour cells expressing PD-L1 who were evaluable for objective response per independent central review, an objective response was achieved in 9 (12·2%, 95% CI 5·7-21·8) of 74 patients in cohort 1 and 24 (16·4%, 10·8-23·5) of 146 patients in cohort 2. In cohort 3, 21 (30·9%, 20·2-43·3) of 68 patients achieved an objective response. Grade 3 or 4 treatment-related adverse events occurred in 40 (9%) of 444 patients overall: six (5%) of 111 patients in cohort 1, 22 (8%) of 265 in cohort 2, and 12 (18%) of 68 in cohort 3. The most common treatment-related grade 3 or 4 adverse events were pneumonitis (four patients [1%]), elevated gamma-glutamyltransferase (four [1%]), diarrhoea (three [1%]), infusion-related reaction (three [1%]), elevated aspartate aminotransferase (two [<1%]), elevated transaminases (two [<1%]), vomiting (two [<1%]), and fatigue (two [<1%]). Treatment-related serious adverse events occurred in 27 (6%) of 444 patients overall: five (5%) of 111 patients in cohort 1, 14 (5%) of 265 in cohort 2, and eight (12%) of 68 in cohort 3. The most common serious adverse events overall were pneumonitis (five patients [1%]), fatigue (three [1%]), and infusion-related reaction (three [1%]). Immune-mediated events were manageable with standard treatment guidelines.
Interpretation:
In patients with advanced and heavily pretreated NSCLC, the clinical activity and safety profile of durvalumab was consistent with that of other anti-PD-1 and anti-PD-L1 agents. Responses were recorded in all cohorts; the proportion of patients with EGFR-/ALK- NSCLC (cohorts 2 and 3) achieving a response was higher than the proportion with EGFR+/ALK+ NSCLC (cohort 1) achieving a response. The clinical activity of durvalumab in patients with EGFR+ NSCLC with ≥25% of tumour cells expressing PD-L1 was encouraging, and further investigation of durvalumab in patients with EGFR+/ALK+ NSCLC is warranted.
Funding:
AstraZeneca.
Insights
Durvalumab showed clinical activity in advanced non-small-cell lung cancer (NSCLC) patients, regardless of EGFR/ALK status. Responses were observed across all cohorts, with higher rates in EGFR-/ALK- NSCLC patients.
Area of Science:
- Oncology
- Immunotherapy
- Non-small-cell lung cancer (NSCLC) research
Background:
- Immune checkpoint inhibitors (ICIs) are standard for advanced NSCLC without EGFR/ALK aberrations.
- Clinical benefit of ICIs in EGFR-mutated or ALK-rearranged (EGFR+/ALK+) NSCLC remains uncertain.
- Durvalumab (anti-PD-L1) efficacy was assessed in NSCLC patients based on EGFR/ALK and PD-L1 status.
Purpose of the Study:
- To evaluate the efficacy and safety of durvalumab in patients with advanced NSCLC.
- To assess durvalumab's effect across different cohorts defined by EGFR/ALK genetic status and PD-L1 expression.
Main Methods:
- Phase 2, open-label, single-arm ATLANTIC trial (NCT02087423).
- Three patient cohorts: EGFR+/ALK+ NSCLC (Cohort 1) and EGFR-/ALK- NSCLC (Cohorts 2 & 3) with varying PD-L1 expression.
- Durvalumab (10 mg/kg IV every 2 weeks) administered for up to 12 months; primary endpoint: objective response rate (ORR).
Main Results:
- Objective response was observed in 12.2% (Cohort 1), 16.4% (Cohort 2), and 30.9% (Cohort 3) of patients with PD-L1 ≥25% or ≥90%.
- Grade 3/4 treatment-related adverse events (TRAEs) occurred in 9% of patients overall, with higher incidence in Cohort 3 (18%).
- Most common TRAEs included pneumonitis, elevated liver enzymes, diarrhea, and infusion reactions; immune-mediated events were manageable.
Conclusions:
- Durvalumab demonstrated consistent clinical activity and a manageable safety profile in heavily pretreated advanced NSCLC.
- Higher response rates were observed in EGFR-/ALK- NSCLC patients compared to EGFR+/ALK+ NSCLC patients.
- Encouraging activity in EGFR+ NSCLC with high PD-L1 expression warrants further investigation.
Related Concept Videos
 01:28
Inductance: Single-Phase And Three-Phase Line
Single-Phase Two-Wire Line:
A single-phase line consists of two solid cylindrical conductors, denoted as x and y. Each conductor carries phasor currents ix and iy, respectively. Given that the sum of these currents is...
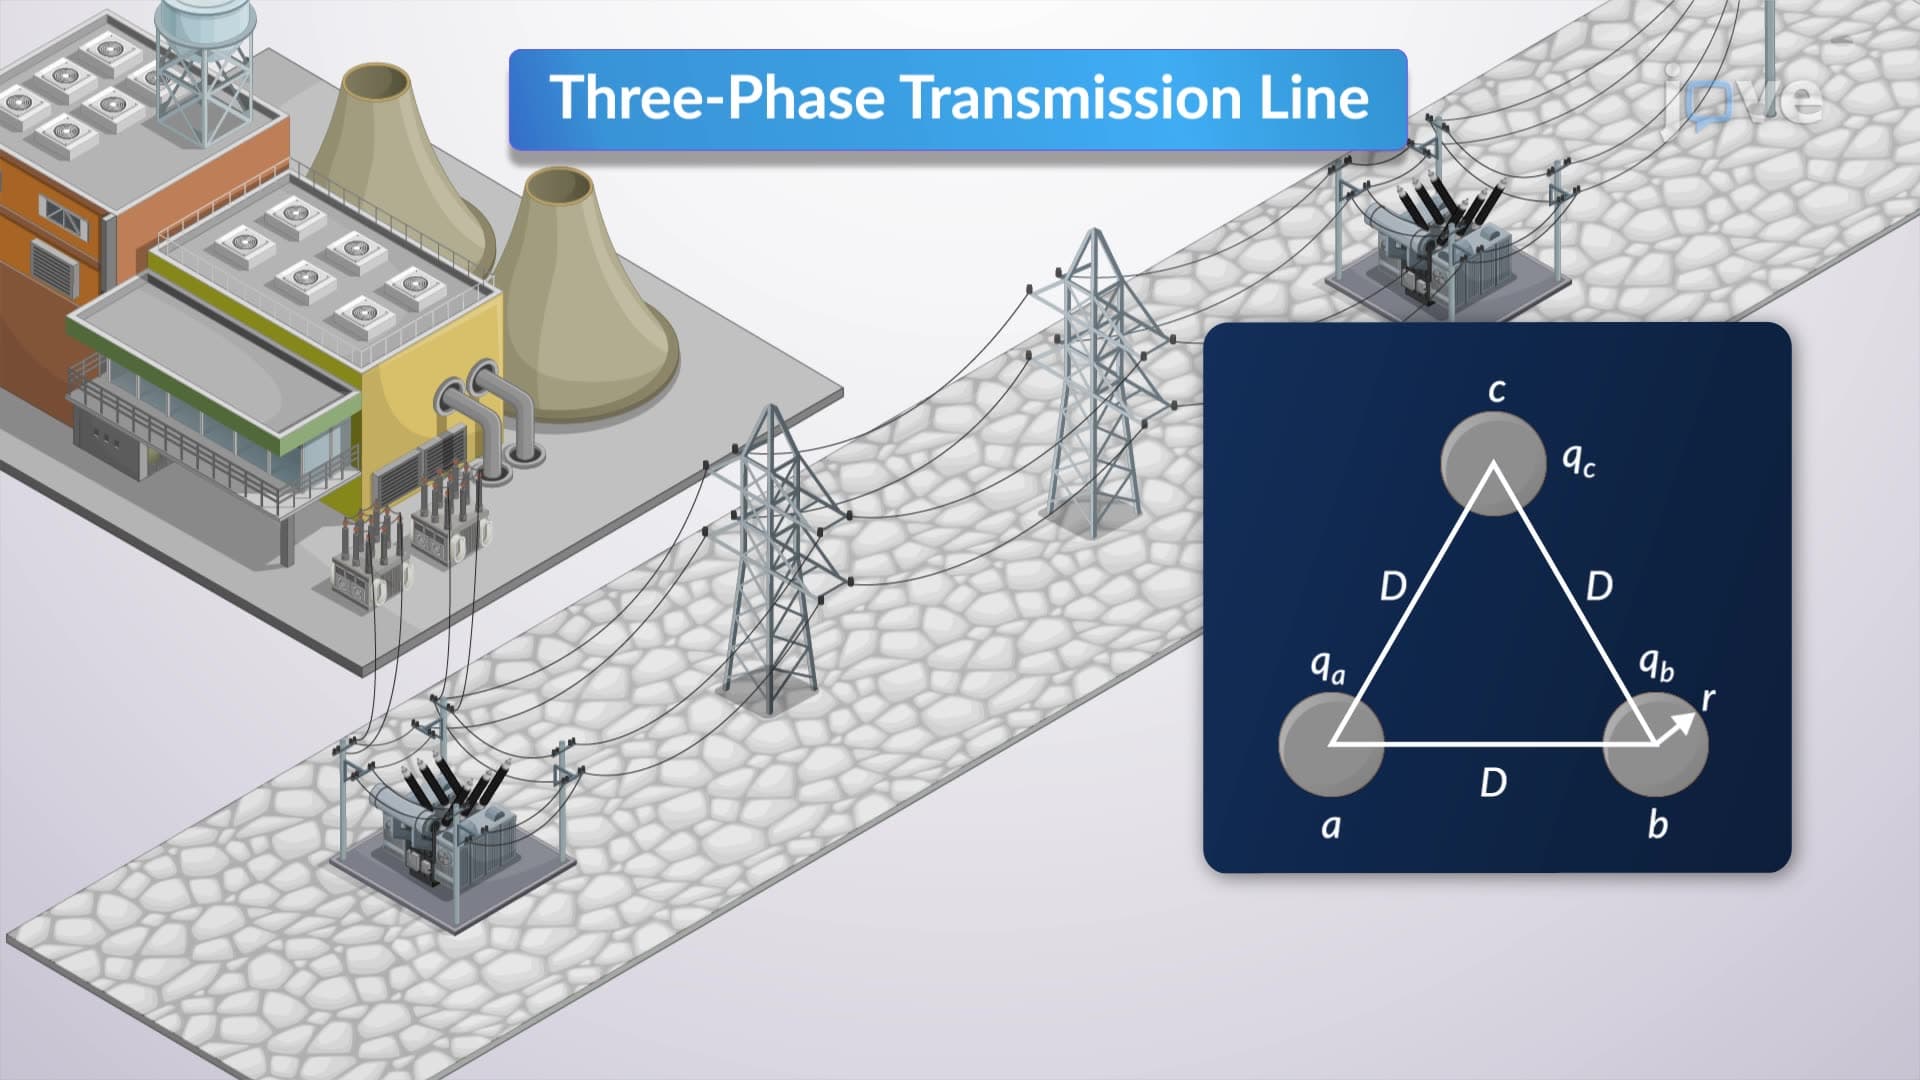 01:25
Capacitance: Single-Phase And Three-Phase Line
Single-Phase Lines
Consider a single-phase, two-wire transmission line with equal phase spacing energized by a voltage source. One conductor carries a uniform positive charge, while the other carries an equal negative charge. The capacitance C of the line can be derived from the voltage V between the conductors. For a one-meter section of the line, the capacitance is given...
 01:17
Power Distribution in Three-phase and Single Phase Circuits
Single-Phase Power Distribution:
Single-phase circuits are typical in household settings;...
 02:56
Treatment Resistant Cancers
 02:21
Cancers Originate from Somatic Mutations in a Single Cell
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...