Related Experiment Video
Updated: Feb 13, 2026

Heat-sensitive Moxibustion as a Traditional Chinese Medicine Therapy for Chronic Obstructive Pulmonary Disease Combined with Insomnia
Published on: May 30, 2025
Clinically Oriented Subtyping of Chronic Insomnia of Childhood
Oliviero Bruni1, Stefania Sette1, Marco Angriman2
1Department of Developmental and Social Psychology, Sapienza University of Rome, Rome, Italy.

Insights
Pediatric insomnia presents in three distinct phenotypes, identified through clinical, personal, and familial data. Recognizing these profiles can improve the assessment and treatment of sleep disturbances in children.
Area of Science:
- Pediatric Sleep Medicine
- Child Psychology
- Genetics
Background:
- Pediatric insomnia is a common issue, often resistant to standard treatments.
- Understanding distinct insomnia profiles is crucial for effective intervention.
Purpose of the Study:
- To identify and characterize different phenotypes of pediatric insomnia.
- To analyze the clinical presentations, personal, and familial factors associated with each phenotype.
Main Methods:
- Latent class analysis was employed on data from 338 children with insomnia.
- Structured parent interviews assessed insomnia characteristics and family sleep history.
- ANOVA and chi-squared tests compared differences between identified profiles.
Main Results:
- Three distinct pediatric insomnia phenotypes were identified.
- Class 1 (17%) exhibited difficulty falling asleep with restlessness.
- Class 2 (21%) presented with early morning awakenings and mood disorders in family history.
- Class 3 (62%) showed frequent nocturnal awakenings and difficulty falling asleep, with allergies/intolerances in family history.
Conclusions:
- The study confirms three distinct phenotypes of pediatric insomnia.
- Phenotype identification aids in optimizing assessment and treatment strategies.
- Personal and familial data are key in differentiating insomnia profiles.
Objectives:
To identify different profiles of pediatric insomnia, based on the most frequent clinical presentations (nocturnal awakenings, difficulty in falling asleep, nocturnal restlessness, early morning awakenings).
Study Design:
A structured parent interview was conducted in 338 children (mean age 21.29 months, SD 10.56) referred by pediatricians because of insomnia resistant to behavioral approaches and common drug treatments. The aim was to assess the characteristics of insomnia in children, together with family sleep-related history. A latent class analysis was run to identify profiles of insomnia. ANOVA and the χ2 test were used to examine differences between profiles.
Results:
A 3-class model was built by latent class analysis: 17% (n = 58) of children constituted the first class, characterized by difficulties in falling asleep, with restlessness, nocturnal restlessness, and awakenings during the night; the second class, characterized by early morning awakenings, comprised 21% (n = 71) of children; 62% (n = 209) of children fell within the third class because of their high frequency of nocturnal awakenings and difficulties in falling asleep. The first class reported longer sleep latency and the presence of restless legs syndrome and anemia in the family history; depression and/or mood disorders were more frequent in class 2 and allergies and/or food intolerance were more frequent in class 3.
Conclusions:
Our study suggests the existence of 3 different phenotypes of insomnia in children, based on clinical, personal, and familial data. The identification of these different phenotypes might help to optimize the assessment and treatment of insomnia in young children.
Related Concept Videos
 01:27
Insomnia
Multiple factors contribute...
 01:19
Management of Insomnia
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:13
Location and Orientation of the Heart
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:26
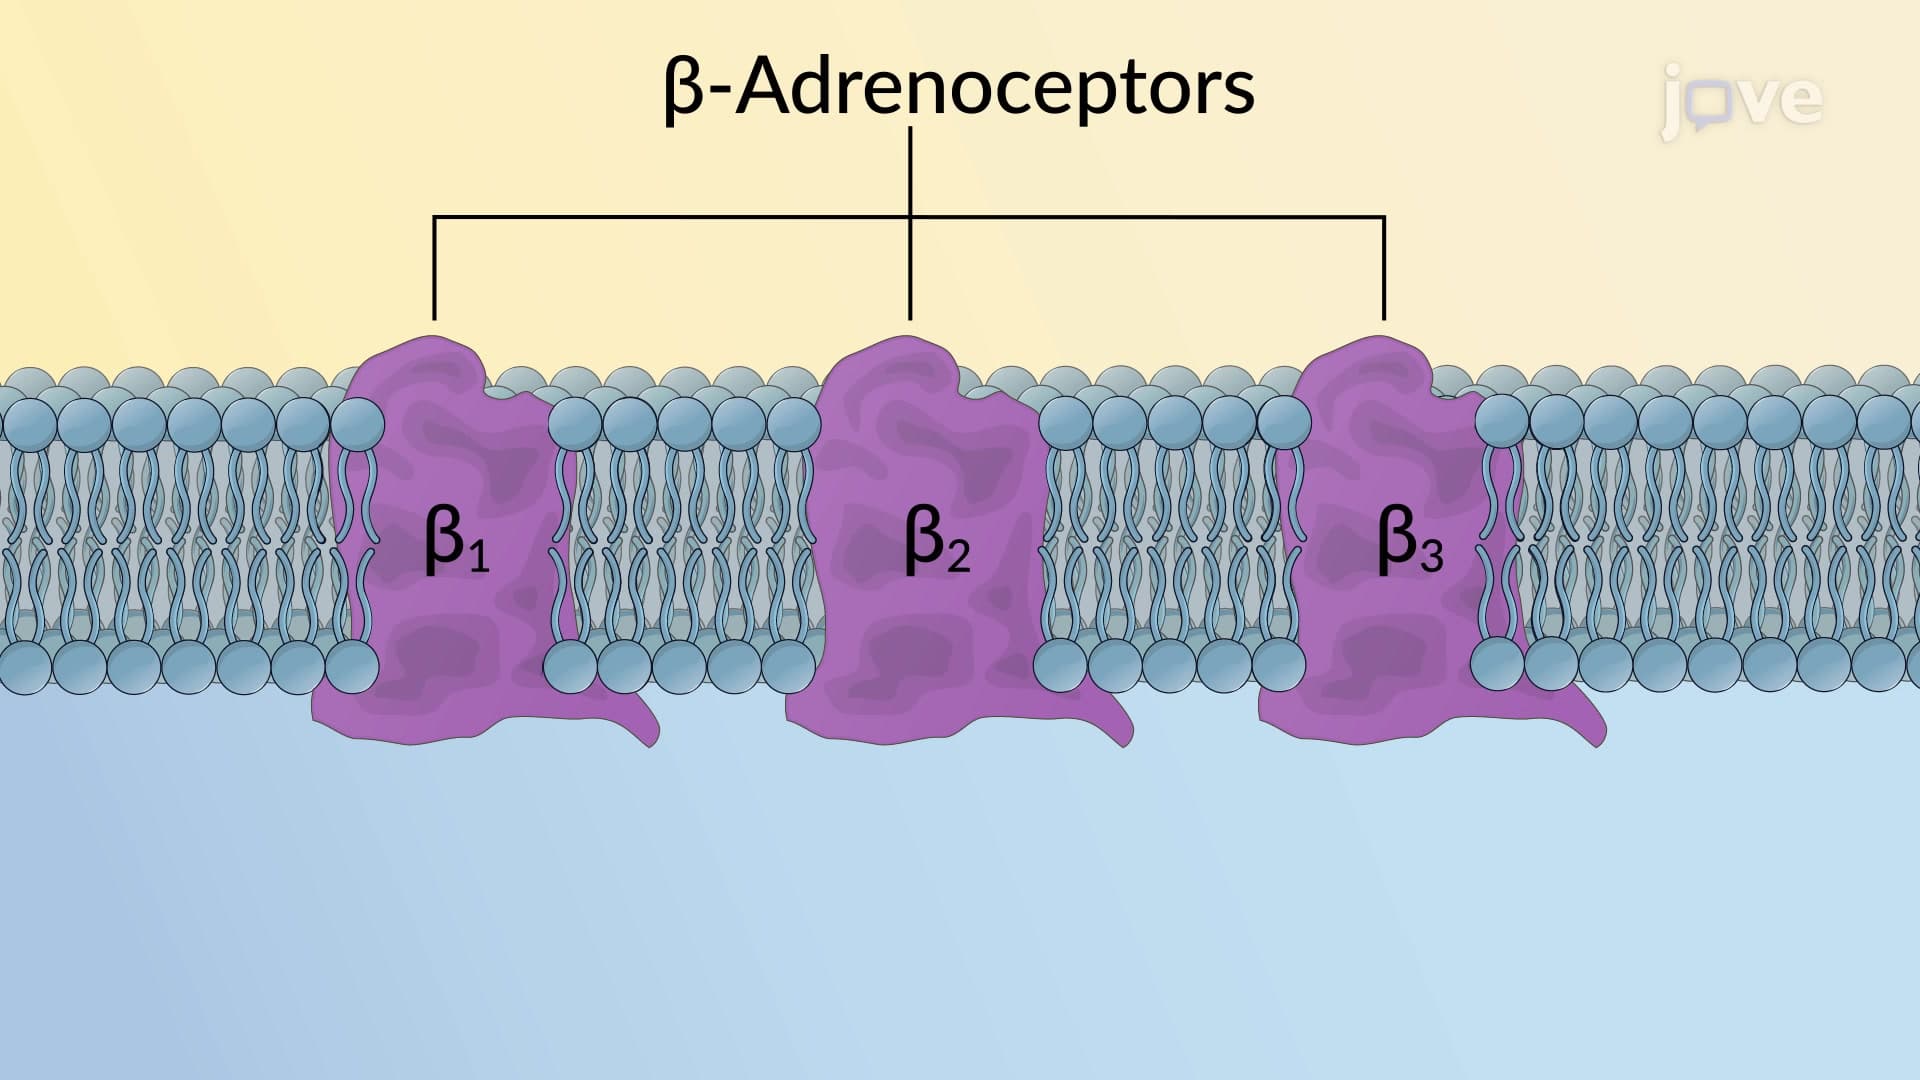
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...