Related Experiment Video
Updated: Feb 13, 2026

Application of Ultrasound and Shear Wave Elastography Imaging in a Rat Model of NAFLD/NASH
Published on: April 20, 2021
Myocardial Stiffness Evaluation Using Noninvasive Shear Wave Imaging in Healthy and Hypertrophic Cardiomyopathic
Olivier Villemain1, Mafalda Correia2, Elie Mousseaux3
1Institut Langevin, ESPCI, CNRS, Inserm U979, PSL Research University, Paris, France; Hôpital Européen Georges Pompidou, Université Paris Descartes, Cardio-Vascular Departement, UMR 970, Paris, France.

Objectives:
The goal of our study was to investigate the potential of myocardial shear wave imaging (SWI) to quantify the diastolic myocardial stiffness (MS) (kPa) noninvasively in adult healthy volunteers (HVs) and its physiological variation with age, and in hypertrophic cardiomyopathy (HCM) populations with heart failure and preserved ejection function (HFpEF).
Background:
MS is an important prognostic and diagnostic parameter of the diastolic function. MS is affected by physiological changes but also by pathological alterations of extracellular and cellular tissues. However, the clinical assessment of MS and the diastolic function remains challenging. SWI is a novel ultrasound-based technique that has the potential to provide intrinsic MS noninvasively.
Methods:
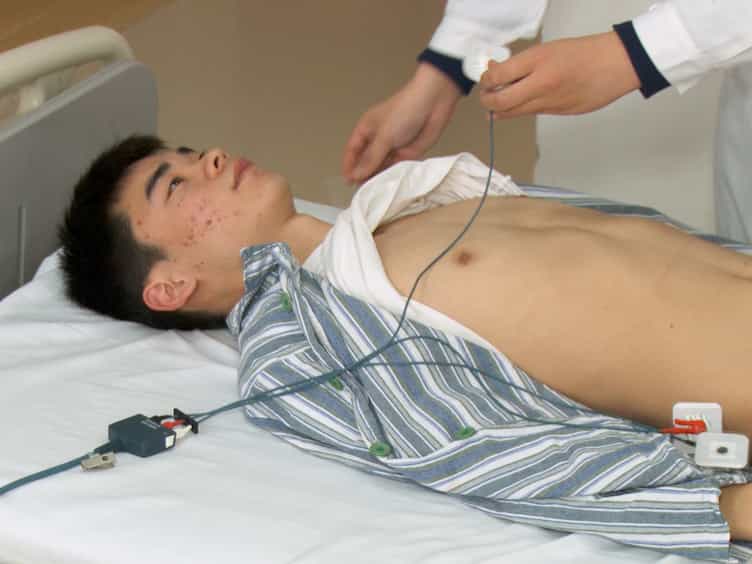
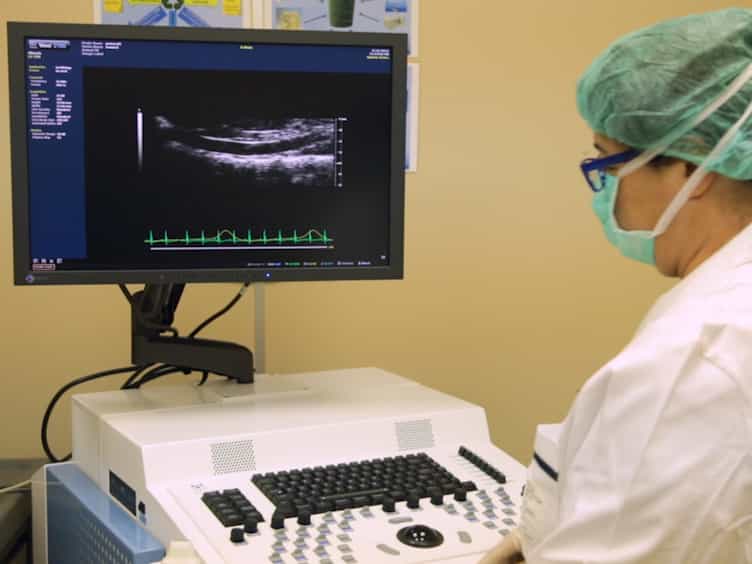
We prospectively included 80 adults: 60 HV (divided into 3 groups: 20- to 39-year old patients [n = 20]; 40- to 59-year-old patients [n = 20]; and 60- to 79-year-old patients [n = 20]) and 20 HCM-HFpEF patients. Echocardiography, cardiac magnetic resonance imaging and biological explorations were achieved. MS evaluation was performed using an ultrafast ultrasound scanner with cardiac phased array. The fractional anisotropy of MS was also estimated.
Results:
MS increased significantly with age in the HV group (the mean MS was 2.59 ± 0.58 kPa, 4.70 ± 0.88 kPa, and 6.08 ± 1.06 kPa for the 20- to 40-year-old, 40- to 60-year-old, and 60- to 80-year-old patient groups, respectively; p < 0.01 between each group). MS was significantly higher in HCM-HFpEF patients than in HV patients (mean MS = 12.68 ± 2.91 kPa vs. 4.47 ± 1.68 kPa, respectively; p < 0.01), with a cut-off at 8 kPa (area under the curve = 0.993; sensitivity = 95%, specificity = 100%). The fractional anisotropy was lower in HCM-HFpEF (mean = 0.133 ± 0.073) than in HV (0.238 ± 0.068) (p < 0.01). Positive correlations were found between MS and diastolic parameters in echocardiography (early diastolic peak/early diastolic mitral annular velocity, r = 0.783; early diastolic peak/transmitral flow propagation velocity, r = 0.616; left atrial volume index, r = 0.623) and with fibrosis markers in cardiac magnetic resonance (late gadolinium enhancement, r = 0.804; myocardial T1 pre-contrast, r = 0.711).
Conclusions:
MS was found to increase with age in healthy adults and was significantly higher in HCM-HFpEF patients. Myocardial SWI has the potential to become a clinical tool for the diagnostic of diastolic dysfunction. (Non-invasive Evaluation of Myocardial Stiffness by Elastography [Elasto-Cardio]; NCT02537041).
Related Concept Videos
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 02:12
The Wave Nature of Light
 01:27
Shear Diagram
First, a free-body diagram of the beam is drawn, representing all the external forces and internal reactions acting on the beam. One can calculate the reaction forces at each support by employing the equilibrium equations of force and moment. The vertical component...
 01:19
Shearing Stress
The average shearing stress can be calculated by dividing the shear by the area of the cross-section.
 01:20
Shearing Strain
 01:14
Normal and Shear Force