Related Experiment Video
Updated: Feb 13, 2026

Using Caco-2 Cells to Study Lipid Transport by the Intestine
Published on: August 20, 2015
Non-obese type 2 diabetes patients present intestinal B cell dysregulations associated with hyperactive intestinal
Jingjing Zhou1, Yiran Wang2, Yifei He1
1Department of Endocrinology, Changhai Hospital Affiliated to the Second Military Medical University, Shanghai, China.

Abstract:
Most current studies of type 2 diabetes (T2D) focus on obesity in the pathogenesis of the disease. However, many individuals develop T2D at non-obese body mass index (BMI) level. It is yet unclear whether certain etiological mechanisms discovered in these obese models can apply to non-obese T2D patients. In the present study, we focused on one aspect that was potentially involved in T2D development, the intestinal inflammation, and examined the difference between non-obese T2D patients and BMI-matched healthy controls. We found that non-obese T2D patients presented significantly higher levels of fecal IgG than BMI-matched controls. Compared to active Crohn's disease patients, both T2D and healthy controls presented lower levels of fecal IgG. In the mucosal biopsies, the B cells and plasmablasts from T2D patients presented a slight but significant increase in the frequencies of cells with surface IgG expression compared to those from healthy individuals. The potential mechanism resulting in increased IgG expression was then examined. The CD4+CXCR5+ T cells (Tfh) from non-obese T2D patients were highly enriched in IFN-γ-producing cells and depleted in IL-4- and IL-17-producing cells. Presence of mucosal CD4+CXCR5+ T cells significantly increased IgG production from mucosal samples. Interestingly, when stimulated with E. coli, a common intestinal microbe, the CD4+CXCR5+ T cells from T2D patients presented significantly higher IFN-γ expression than CD4+CXCR5+ T cells from BMI-matched controls Together, these results demonstrated that non-obese T2D patients presented a low-grade inflammation in the intestinal tract, possibly supported by bacteria-responding CD4+CXCR5+ T cells.


Related Concept Videos
 01:23
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...
 01:23
Renewal of Intestinal Stem Cells
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:15
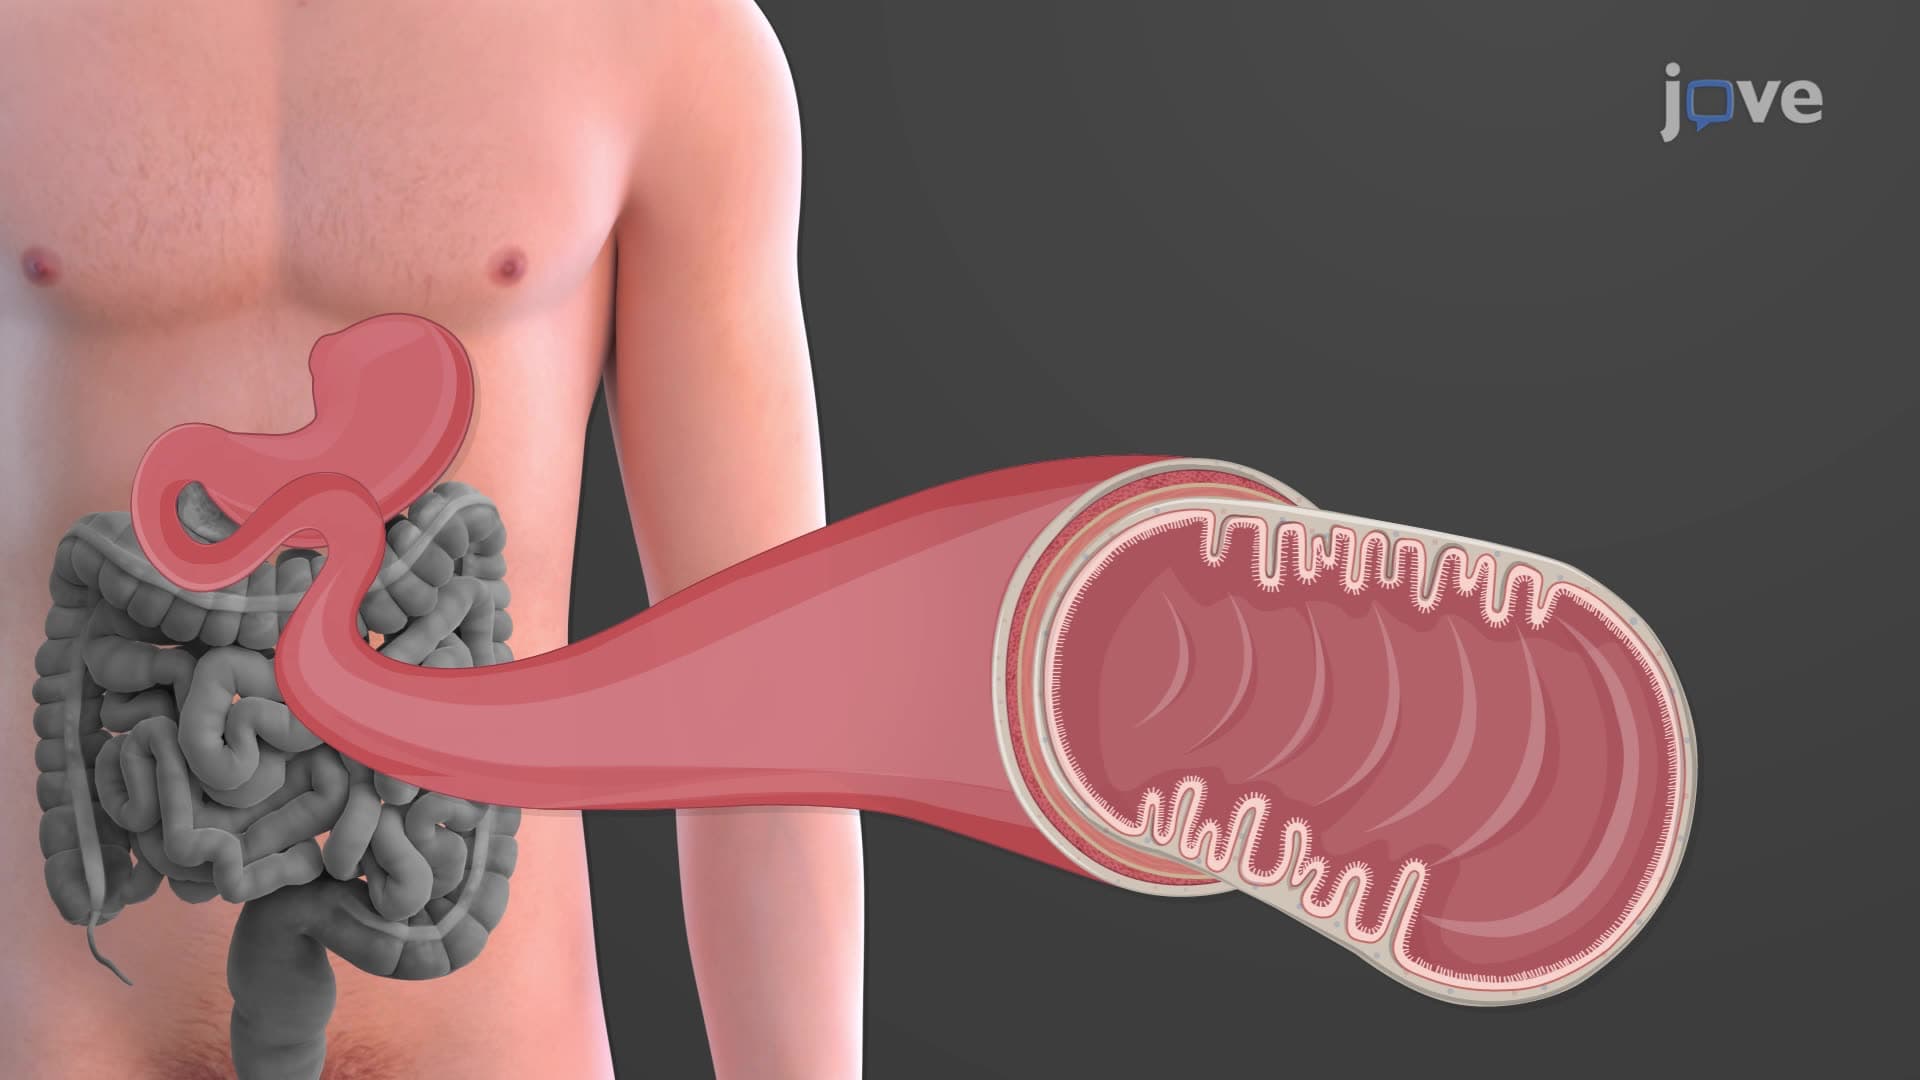
Small Intestine
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...
 01:09
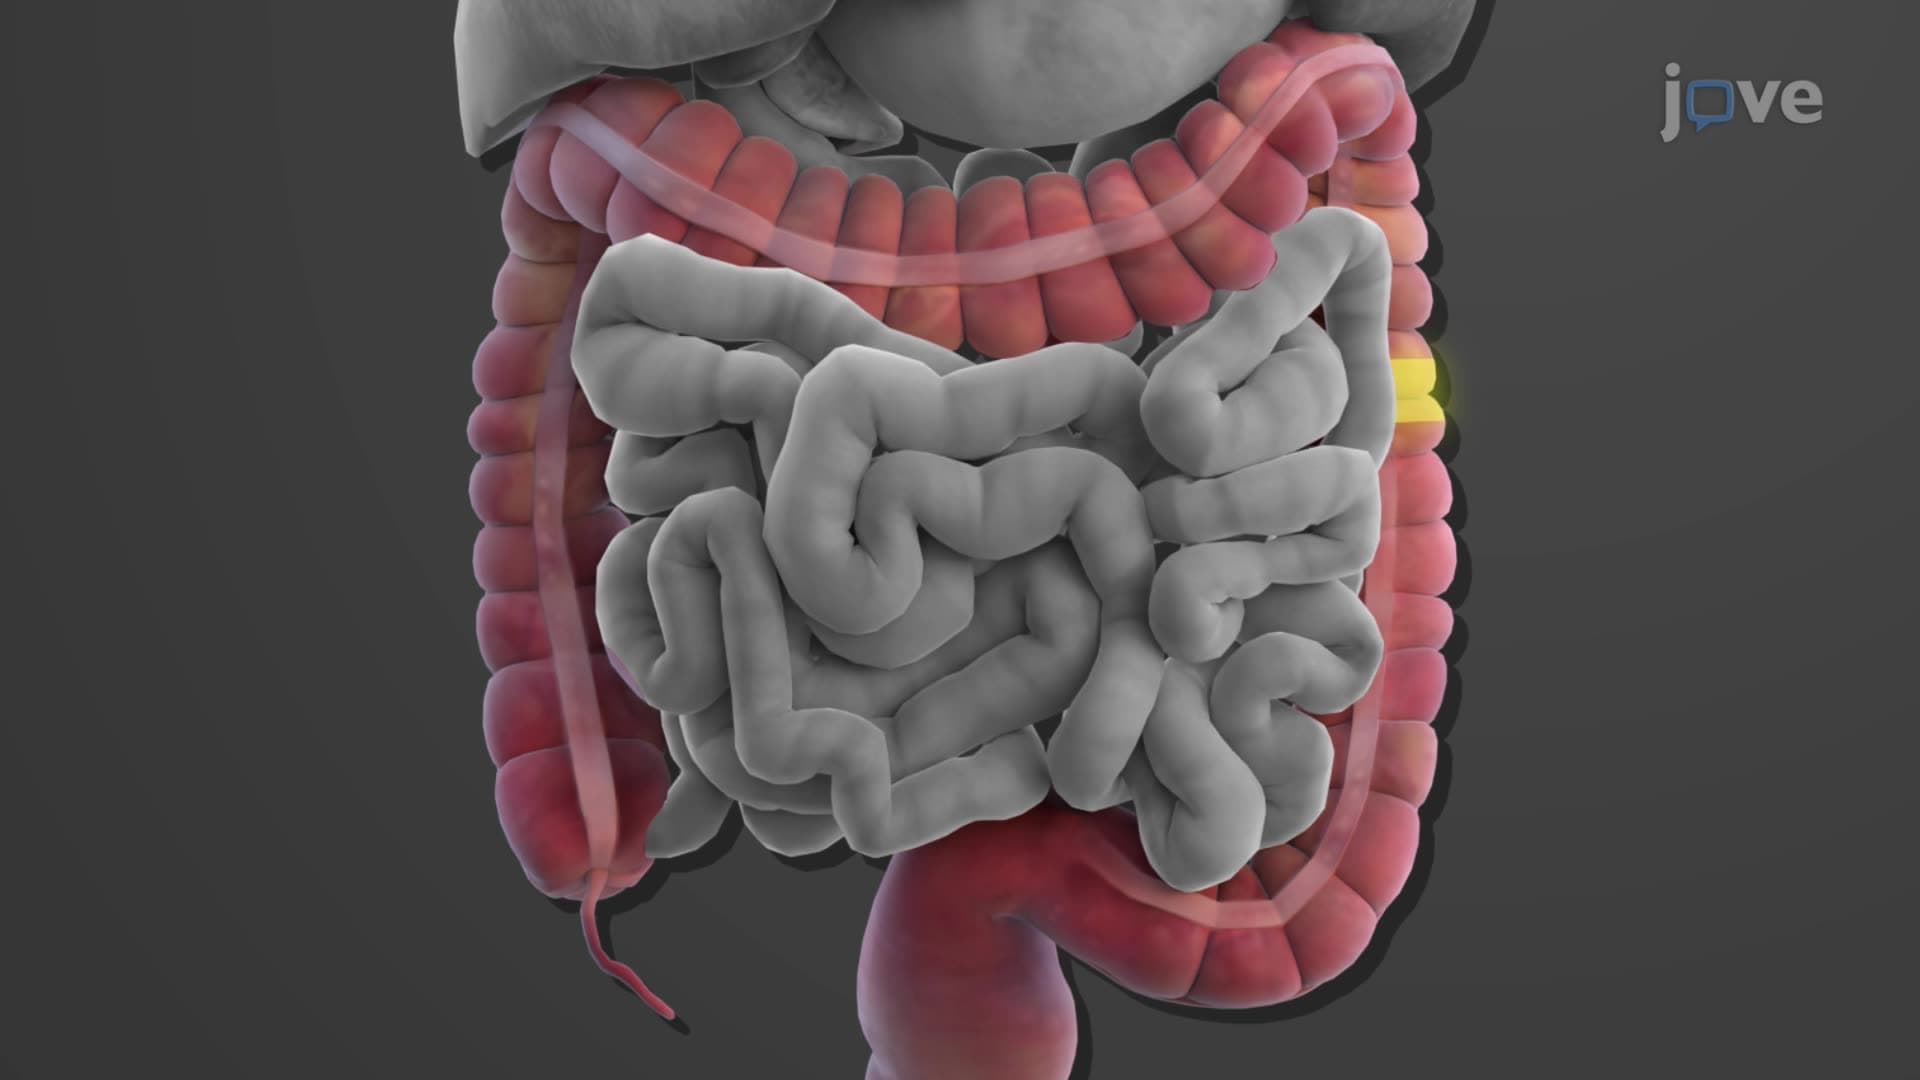
Large Intestine
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:26
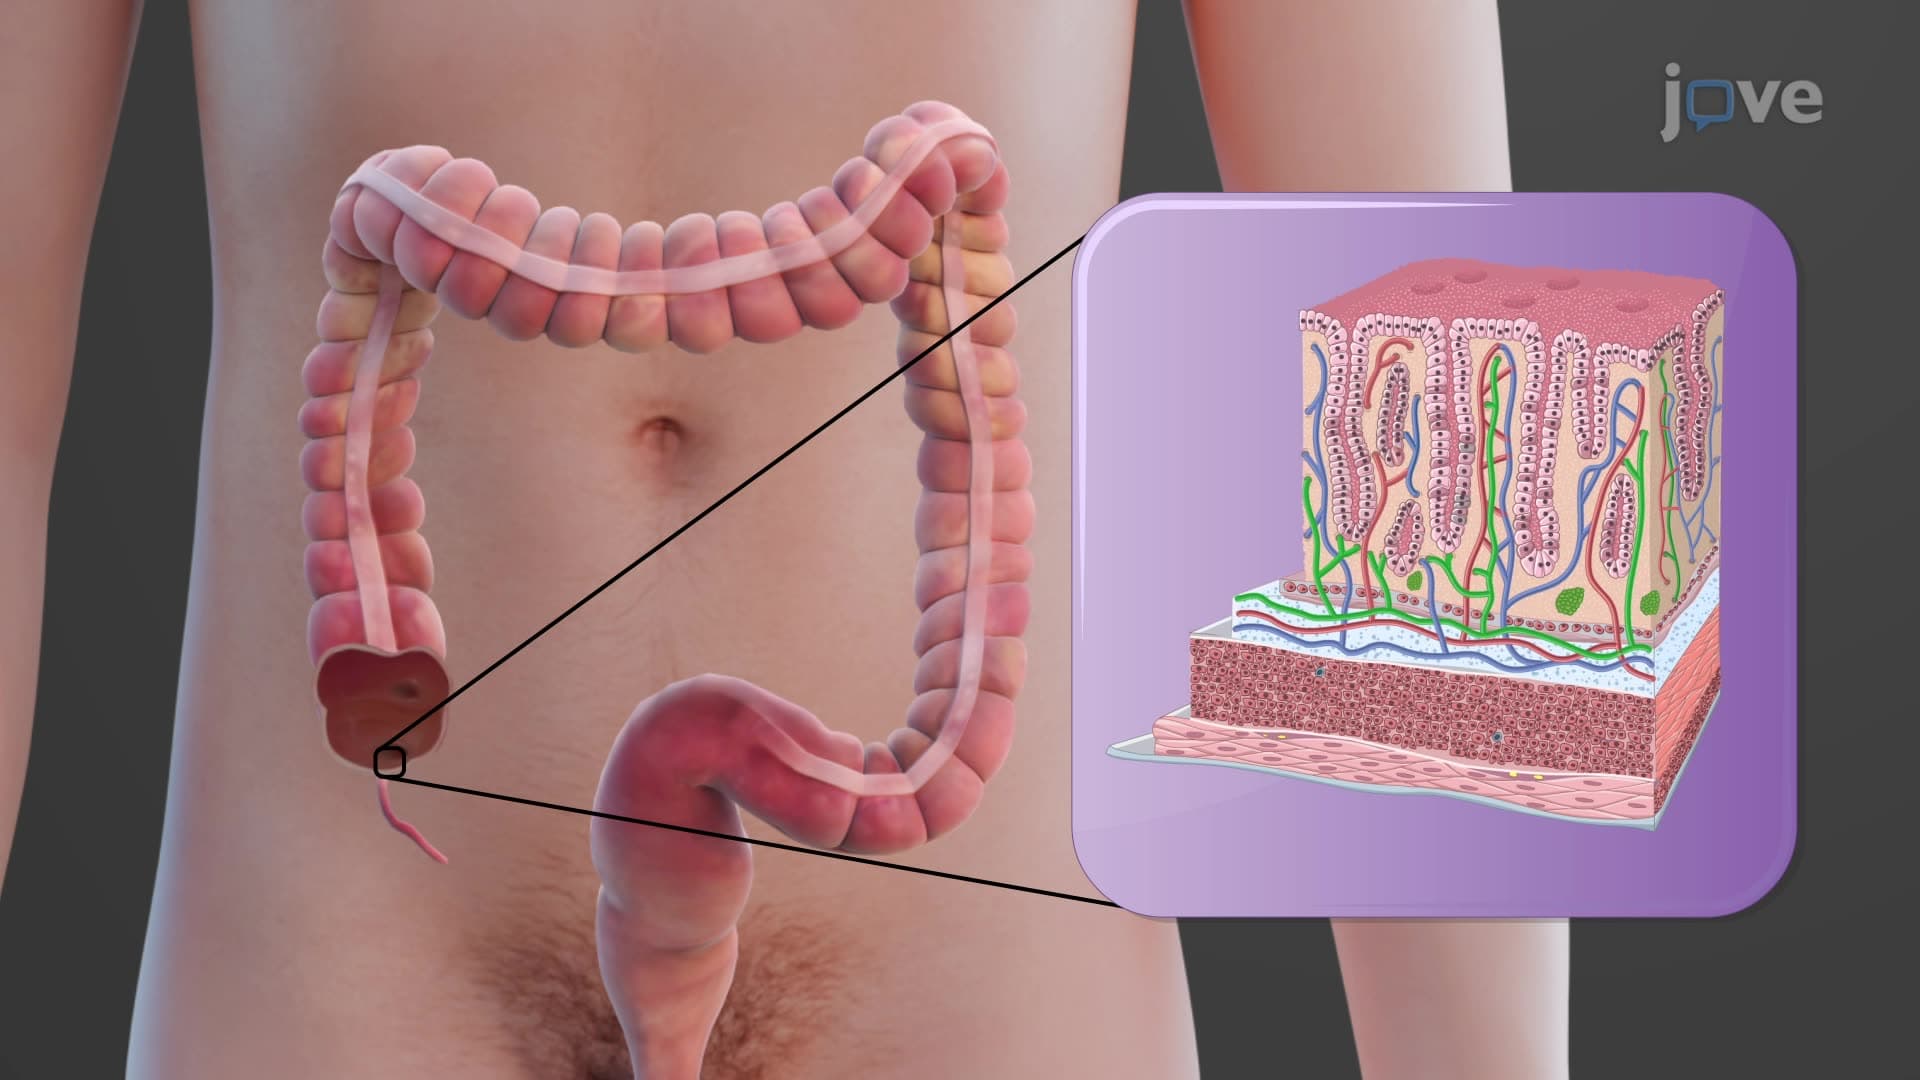
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...